Antibiotic Treatment Protocols for Lyme Disease
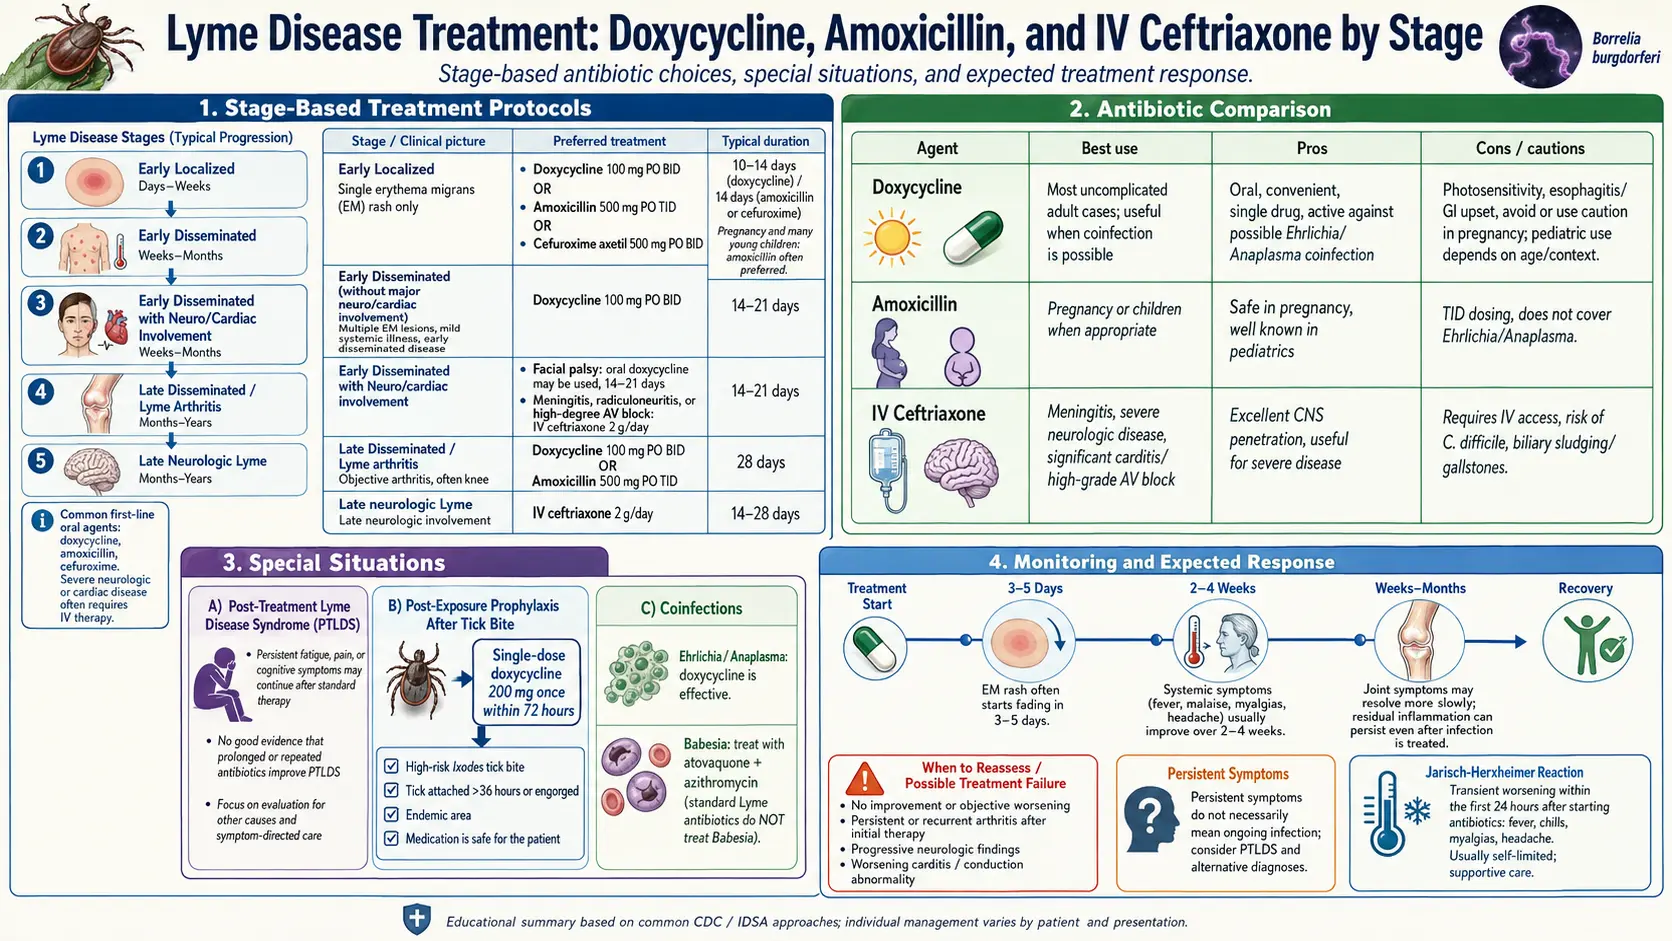
Table of Contents
- The Core Principle — Right Dose, Right Duration
- Early Localized Lyme (Single EM Rash)
- Early Disseminated Lyme (No Central Nervous System)
- Lyme Carditis
- Lyme Arthritis
- Lyme Neuroborreliosis
- Pediatric Dosing
- Pregnancy and Breastfeeding
- Jarisch-Herxheimer Reaction
- Intravenous vs. Oral — When Each Is Needed
- Why Longer Courses Don't Help
- Re-Treatment After a First Course
- Drug Interactions and Side Effects
- If Symptoms Persist After Treatment
- Key Research Papers
- Connections
- Featured Videos
The Core Principle — Right Dose, Right Duration
Lyme disease is caused by the spirochete bacterium Borrelia burgdorferi (plus a small number of related species in Europe and Asia). It is a bacterium, which means antibiotics work — reliably, measurably, and usually quickly. Roughly 90% of patients treated in the early localized stage are cured with a single oral course, and even late-stage manifestations like Lyme arthritis respond to standard regimens in the large majority of cases.
Two principles guide every protocol on this page:
- The right drug at the right dose for the right duration works. Underdosing (skipping doses, stopping early, using suboptimal drugs) leaves residual infection.
- Longer is not better. Four major randomized controlled trials have tested multi-month antibiotics against placebo in patients with persistent symptoms. None led its authors to support prolonged antibiotics, and the long intravenous courses carried harm — in one trial, adverse events from the drug or the IV line occurred in 6 of 23 treated patients versus 1 of 14 on placebo (all resolved) — while a 2016 trial of 12 weeks of oral antibiotics found adverse-event rates similar to placebo. Stretching a two-week course into six months does not kill more bacteria — it just accumulates complications.
Everything below follows the 2020 IDSA/AAN/ACR joint guidelines, the current U.S. standard of care. Where European practice differs (notably for neuroborreliosis), we note it.
Early Localized Lyme (Single EM Rash)
Early localized disease means a single erythema migrans (EM) rash, usually within 30 days of a tick bite, with or without mild constitutional symptoms (low-grade fever, fatigue, headache, mild myalgia). No neurologic, cardiac, or joint involvement. First-line oral options in adults:
- Doxycycline 100 mg PO twice daily × 10 days. The preferred agent in non-pregnant adults and children ≥8 years. It has the added advantage of covering Anaplasma phagocytophilum and Ehrlichia, the two most common tick-borne co-infections transmitted by the same Ixodes ticks. A 10-day course is the current IDSA 2020 recommendation — shortened from the older 14-to-21-day courses after randomized controlled trials (RCTs) showed equivalent efficacy.
- Amoxicillin 500 mg PO three times daily × 14 days. The default for pregnant or breastfeeding patients and children under 8 who cannot receive doxycycline. Slightly longer course because amoxicillin does not achieve the intracellular concentrations doxycycline does.
- Cefuroxime axetil 500 mg PO twice daily × 14 days. Reserved for patients who cannot tolerate doxycycline or amoxicillin (penicillin allergy short of anaphylaxis, doxycycline gastrointestinal (GI) intolerance).
- Azithromycin 500 mg PO once daily × 7 days. For patients unable to take both doxycycline and the beta-lactam antibiotics (amoxicillin, cefuroxime), the 2020 guideline names azithromycin the preferred second-line agent. It reports azithromycin as of comparable efficacy to the other drugs for erythema migrans in every clinical trial to date except one, a U.S. comparison with amoxicillin.
The EM rash typically fades within days of starting antibiotics. Fatigue and myalgia may take 2–4 weeks to resolve fully even after the bacteria are gone — normal post-infectious recovery, not treatment failure.
Early Disseminated Lyme (No Central Nervous System)
Early disseminated Lyme means the spirochetes have spread beyond the tick-bite site but without meningitis or encephalitis. Typical presentations:
- Multiple EM lesions (several secondary rashes elsewhere on the body).
- Cranial nerve palsy — most commonly isolated facial nerve (CN VII) palsy, unilateral or bilateral, without headache/stiff neck/meningeal signs.
- Lyme carditis without high-grade AV block (see the next section).
- Radiculoneuropathy — shooting pain in a dermatomal distribution.
Treatment is the same oral regimens as early localized disease, extended to 14–21 days. Doxycycline 100 mg BID, amoxicillin 500 mg TID, or cefuroxime axetil 500 mg BID. Isolated facial palsy in particular — which was once routinely treated with intravenous (IV) ceftriaxone — is now clearly an oral-antibiotic condition based on multiple European randomized controlled trials showing equivalent outcomes.
Lyme Carditis
Lyme carditis is uncommon (about 1% of untreated cases) but matters because it can cause sudden high-grade AV block, syncope, and — rarely — death. The cornerstone of management is the PR interval on electrocardiogram (ECG):
- First-degree AV block with PR < 300 ms, asymptomatic, hemodynamically stable: outpatient oral doxycycline 100 mg BID × 14–21 days. An electrocardiogram is repeated in 48–72 hours to confirm the interval is narrowing. No hospitalization is needed.
- PR ≥ 300 ms, or any second- or third-degree AV block, or symptomatic (syncope, dyspnea, chest pain): the 2020 guideline recommends hospital admission with continuous heart (ECG) monitoring. Treatment starts with intravenous ceftriaxone 2 g daily, switching to oral doxycycline once the block has resolved (usually 3–7 days) to complete a total 14–21-day course.
Temporary pacing may be required for high-grade block. Permanent pacemakers are almost never needed — Lyme carditis is reversible with antibiotics. If a patient receives a permanent pacemaker for what later turns out to be Lyme carditis, it was almost always an unnecessary procedure.
Lyme Arthritis
Lyme arthritis is typically a monoarthritis or oligoarthritis of large joints, most often one knee, appearing weeks to months after infection. The joint is swollen, warm, and stiff but often surprisingly less painful than you would expect from the size of the effusion.
Standard first course: doxycycline 100 mg PO twice daily × 28 days. Amoxicillin 500 mg TID × 28 days is an alternative.
About 80–90% of patients resolve completely with this single oral course. The remaining 10–20% have persistent synovitis at the 2-month mark. For them:
- Second course: for a partial response (mild leftover joint swelling) after the first oral course, the 2020 IDSA/AAN/ACR guideline makes no recommendation between a second course of antibiotics and watching, noting that a repeat oral course of up to a month may be a reasonable alternative. For no or minimal response (moderate to severe swelling that barely goes down), it suggests a 2–4 week course of intravenous ceftriaxone 2 g daily over a second oral course. Oral treatment is cheaper and avoids IV-line complications.
- Post-antibiotic Lyme arthritis. A subset of patients — often HLA-DR4-positive — have persistent synovitis even after two full courses. By that point, live bacteria are rarely recoverable from the joint; the inflammation is immune-driven, not infection-driven. Management shifts to a rheumatologist: for patients who have failed one oral and one intravenous course, the 2020 guideline suggests referral for disease-modifying antirheumatic drugs (DMARDs, e.g. methotrexate, hydroxychloroquine), biologic agents, steroid injections into the joint, or arthroscopic synovectomy, and notes that antibiotic therapy for longer than 8 weeks is not expected to add benefit once treatment has included one IV course.
Lyme Neuroborreliosis
Neuroborreliosis encompasses meningitis, encephalitis, encephalomyelitis, cranial neuropathies, and radiculoneuropathy. Diagnosis requires cerebrospinal fluid (CSF) analysis (pleocytosis, elevated protein, intrathecal antibody production).
- Encephalitis, myelitis or encephalomyelitis — involvement of the brain or spinal-cord tissue itself (central nervous system (CNS) parenchymal involvement): intravenous ceftriaxone 2 g daily × 14–21 days; for this group the 2020 guideline recommends IV over oral antibiotics. Penicillin G 18–24 million units daily intravenous and cefotaxime 2 g intravenous every 8 hours are acceptable alternatives.
- Meningitis, cranial neuropathy (e.g., facial palsy) or radiculoneuropathy, without brain or spinal-cord tissue involvement: the 2020 guideline recommends intravenous ceftriaxone, cefotaxime or penicillin G, or oral doxycycline 100 mg BID, for a preferred 14–21 days, with the choice based on individual factors such as side effects, ease of use and the ability to take pills. This is the major 2020 IDSA/AAN/ACR change: based on European randomized controlled trials (Ljostad et al. and others) showing oral doxycycline non-inferior to intravenous ceftriaxone for most neuroborreliosis, the guideline lists oral doxycycline alongside the IV drugs and recommends IV over oral only when the brain or spinal-cord tissue itself is involved.
Patients often ask whether intravenous is "stronger." It isn't. Doxycycline achieves excellent cerebrospinal fluid penetration; ceftriaxone's only real advantage is that you cannot miss a dose while an infusion is running.
Pediatric Dosing
The 2020 IDSA guidelines made an important change: they state that a growing consensus accepts the safety of doxycycline in young children for at least up to 14 days, though more safety data would be desirable, and that some clinicians reserve doxycycline for young children who cannot tolerate beta-lactam antibiotics (such as amoxicillin or cefuroxime). Older concerns about permanent tooth staining came from long-course tetracycline use in the 1960s and do not appear to apply to short doxycycline courses. U.S. Centers for Disease Control and Prevention (CDC) data specifically support this for Rocky Mountain spotted fever and, by extension, for tick-borne diseases generally.
- Doxycycline: 4.4 mg/kg/day PO divided twice daily, maximum 100 mg per dose. All ages.
- Amoxicillin: 50 mg/kg/day PO divided three times daily, maximum 500 mg per dose.
- Cefuroxime axetil: 30 mg/kg/day PO divided twice daily, maximum 500 mg per dose.
- Intravenous ceftriaxone (for carditis with high-grade block or central nervous system disease): 50–75 mg/kg once daily, maximum 2 g.
Pregnancy and Breastfeeding
Doxycycline is contraindicated in pregnancy (second and third trimester — risk of fetal tooth discoloration and bone growth inhibition) and avoided while breastfeeding, though brief exposure is likely low-risk. Preferred agents:
- Amoxicillin 500 mg PO three times daily × 14–21 days (first-line in pregnancy for any stage except central nervous system/high-grade carditis).
- Cefuroxime axetil 500 mg PO twice daily × 14–21 days if penicillin-allergic.
- Intravenous ceftriaxone 2 g daily for neuroborreliosis or high-grade carditis, same as non-pregnant adults.
Treated Lyme disease in pregnancy has an excellent fetal outcome record. Untreated Lyme in pregnancy has rare reports of adverse outcomes, which is why prompt treatment matters more than agent choice.
Jarisch-Herxheimer Reaction
In roughly 15% of patients, the first 24 hours of antibiotic treatment produce a transient worsening known as the Jarisch-Herxheimer reaction: fever, chills, headache, muscle aches, sometimes a rash flare. It is caused by a burst of bacterial lipoproteins released as the spirochetes die, triggering the innate immune system.
Key points for patients:
- It is not a drug allergy. The 2020 guideline describes it as an inflammatory response to bacterial material released after the first doses; in Lyme disease it is usually mild, self-limited and does not recur later in therapy, and symptoms that begin later in treatment are not counted as this reaction.
- It peaks within 24 hours and resolves within 48.
- Supportive care works: hydration, acetaminophen or ibuprofen for fever and aches, rest.
- True allergic reactions (hives, facial/lip swelling, wheezing, anaphylaxis) are different: they are the reactions for which the drug is stopped, and the doxycycline label lists them among its hypersensitivity reactions. Facial or lip swelling with wheezing can be signs of anaphylaxis, which hospitals treat as an emergency.
Intravenous vs. Oral — When Each Is Needed
There is widespread patient belief that intravenous antibiotics are categorically stronger than oral. For most of Lyme disease, this is wrong. Doxycycline, amoxicillin, and cefuroxime axetil all reach therapeutic tissue levels that kill Borrelia effectively. Intravenous therapy adds three things and three things only:
- Guaranteed adherence (an infusion pump cannot skip doses).
- Higher peak cerebrospinal fluid concentrations of some agents (useful in parenchymal central nervous system disease).
- Management of patients who cannot absorb oral drugs (severe vomiting, gut disease).
Intravenous is reserved for: involvement of the brain or spinal-cord tissue itself (parenchymal central nervous system disease), high-grade AV block (PR ≥300 ms or worse), Lyme arthritis with no or minimal response to a first oral course (where the guideline suggests 2–4 weeks of IV ceftriaxone), and patients who truly cannot take oral medication. Everything else can be treated with oral antibiotics. Indwelling central lines for months of intravenous antibiotics carry a risk of fatal line infection: a 2017 CDC report described a patient treated for “chronic Lyme disease” who died of septic shock from a central-line bloodstream infection. For persistent nonspecific symptoms without objective evidence of reinfection or treatment failure, the 2020 guideline recommends against additional antibiotics.
Why Longer Courses Don't Help
Four large randomized controlled trials have tested multi-month antibiotics against placebo in patients with persistent symptoms after standard treatment:
- Klempner et al. (2001, NEJM) — 30 days intravenous ceftriaxone followed by 60 days oral doxycycline vs. placebo. No benefit.
- Krupp et al. (2003) — 28 days intravenous ceftriaxone vs. placebo for post-Lyme fatigue. Disabling fatigue improved more than on placebo at the 6-month visit, five months after treatment ended; no benefit for cognitive function (mental speed). Because fatigue was the only outcome that improved and treatment was associated with adverse events, the authors concluded the study does not support this treatment.
- Fallon et al. (2008) — 10 weeks intravenous ceftriaxone vs. placebo for cognitive symptoms. Small initial cognitive gain that did not persist at 6 months.
- Berende et al. (2016, NEJM) — 12 weeks oral doxycycline, clarithromycin-hydroxychloroquine, or placebo after induction ceftriaxone. No benefit over placebo.
Against little or no lasting benefit, the treatment carried harm: in the 10-week IV trial, adverse events from the drug or the IV line occurred in 6 of 23 treated patients versus 1 of 14 on placebo (all resolved without permanent injury), and the 2016 trial recorded four serious drug-related adverse events during its 2-week IV ceftriaxone phase. Outside the trials, a 2017 CDC report described septic shock (including one death from a central-line bloodstream infection), bone infection, Clostridioides difficile colitis and abscess in people given long courses for “chronic Lyme disease”; the known side effects of long courses also include gallbladder disease from ceftriaxone, candidiasis, and drug rashes. This is why the 2020 guideline recommends against additional antibiotics for persistent nonspecific symptoms — not because the suffering is dismissed, but because the intervention has been studied and did not bring lasting benefit.
Re-Treatment After a First Course
If clear objective findings return or persist (recurrent EM, persistent arthritis, new carditis or neurologic signs), a single repeat course is reasonable:
- For persistent Lyme arthritis: after a partial response, watching or a repeat 28-day oral course (the guideline makes no recommendation between them); after no or minimal response, a 2–4 week intravenous ceftriaxone course (see Lyme Arthritis above).
- For recurrent EM: a fresh oral course (usually implies a new tick bite, not treatment failure).
- For persistent subjective symptoms (fatigue, cognitive complaints, myalgia) without objective findings: no additional antibiotics. See the section below.
Months of intravenous therapy have been tested in the placebo-controlled trials above: none led its authors to support it, and the IV courses brought complications — in one trial, adverse events in 6 of 23 treated patients versus 1 of 14 on placebo.
Drug Interactions and Side Effects
Doxycycline.
- Photosensitivity. The label describes an exaggerated sunburn reaction in some people taking tetracyclines and says treatment is stopped at the first sign of skin redness. Sunburn can happen even under a cloudy sky; broad-spectrum SPF 30+ sunscreen, long sleeves and a hat are the usual protection. This matters most in summer, which is exactly when most Lyme is treated.
- Esophagitis. The label reports rare cases of esophagitis and esophageal ulcers, mostly in people who took the pill immediately before going to bed, and recommends plenty of fluid with each dose to wash it down. A full 8-ounce glass of water and staying upright (standing or sitting) for at least 30 minutes afterward is the common practice.
- Chelation. The label states that antacids containing aluminum, calcium or magnesium, iron-containing preparations, and bismuth subsalicylate impair absorption, while the absorption of doxycycline is not markedly influenced by food or milk. Pharmacists commonly space doxycycline at least 2 hours apart from these products.
- Gastrointestinal upset. Common. The label recommends giving doxycycline with food or milk if stomach irritation occurs.
Amoxicillin.
- Generally well tolerated. Diarrhea and yeast overgrowth are the main issues.
- Classic maculopapular rash if co-infected with Epstein-Barr virus (EBV) (mononucleosis). This is a non-allergic drug-virus interaction, not a true penicillin allergy, though it still warrants stopping the drug in that episode.
Cefuroxime axetil.
- Gastrointestinal upset; diarrhea. Taking it with food improves absorption and can reduce nausea.
- Minor cross-reactivity risk in penicillin-allergic patients (<1% for non-anaphylactic allergies).
Ceftriaxone (intravenous).
- Biliary sludge and pseudolithiasis — can mimic gallstones; usually reversible on stopping the drug but occasionally causes cholecystitis.
- Line-related complications: bloodstream infection, thrombosis, mechanical failure.
- C. difficile colitis.
If Symptoms Persist After Treatment
About 10–20% of treated patients report lingering fatigue, cognitive complaints (brain fog, word-finding trouble), myalgia, or arthralgia for 6 months or longer after a completed antibiotic course. This is called Post-Treatment Lyme Disease Syndrome (PTLDS). The symptoms are real and often disabling.
What PTLDS is not: evidence of persistent live infection. Repeated large, well-designed studies have failed to culture viable Borrelia from these patients or to demonstrate benefit from extended antibiotics. The leading current hypotheses are immune dysregulation, persistent non-viable bacterial antigens, autoimmunity, small-fiber neuropathy, and microbiome disruption from the initial treatment itself.
Management is symptomatic and multimodal: graded exercise, sleep optimization, treatment of co-existing conditions (dysautonomia, mast cell activation syndrome (MCAS), co-infections, thyroid disease), cognitive rehabilitation, and mental-health support. See the dedicated PTLDS and Chronic Lyme article for a full treatment framework.
Key Research Papers
- Lantos PM, Rumbaugh J, Bockenstedt LK, et al. Clinical Practice Guidelines by the IDSA, AAN, and ACR: 2020 Guidelines for the Prevention, Diagnosis, and Treatment of Lyme Disease. Clin Infect Dis. 2021;72(1):e1–e48. — doi:10.1093/cid/ciaa1215
- Wormser GP, Dattwyler RJ, Shapiro ED, et al. The clinical assessment, treatment, and prevention of Lyme disease, human granulocytic anaplasmosis, and babesiosis: IDSA Guidelines. Clin Infect Dis. 2006;43(9):1089–1134. — doi:10.1086/508667
- Klempner MS, Hu LT, Evans J, et al. Two controlled trials of antibiotic treatment in patients with persistent symptoms and a history of Lyme disease. N Engl J Med. 2001;345(2):85–92. — doi:10.1056/nejm200107123450202
- Dattwyler RJ, Halperin JJ, Volkman DJ, Luft BJ. Treatment of late Lyme borreliosis — randomised comparison of ceftriaxone and penicillin. Lancet. 1988;1(8596):1191–1194. — PubMed PMID: 2897008
- Krupp LB, Hyman LG, Grimson R, et al. Study and treatment of post Lyme disease (STOP-LD): a randomized double masked clinical trial. Neurology. 2003;60(12):1923–1930. — PubMed PMID: 12821734
- Fallon BA, Keilp JG, Corbera KM, et al. A randomized, placebo-controlled trial of repeated IV antibiotic therapy for Lyme encephalopathy. Neurology. 2008;70(13):992–1003. — PubMed PMID: 17928580
- Berende A, ter Hofstede HJ, Vos FJ, et al. Randomized trial of longer-term therapy for symptoms attributed to Lyme disease. N Engl J Med. 2016;374(13):1209–1220. — PubMed PMID: 27028911
- Marzec NS, Nelson C, Waldron PR, et al. Serious bacterial infections acquired during treatment of patients given a diagnosis of chronic Lyme disease — United States. MMWR Morb Mortal Wkly Rep. 2017;66(23):607–609. — PubMed PMID: 28617768
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on Lyme antibiotic regimens, comparative trials, and adverse-event data:
- PubMed: Doxycycline Lyme disease treatment
- PubMed: Ceftriaxone and Lyme neuroborreliosis
- PubMed: Lyme arthritis antibiotic treatment
- PubMed: Amoxicillin for Lyme disease in children
- PubMed: Lyme carditis and AV block management
- PubMed: Jarisch-Herxheimer reaction in Lyme disease
- PubMed: Post-treatment Lyme disease syndrome and prolonged antibiotics
- PubMed: Oral vs. intravenous antibiotics for Lyme disease
Connections
- Infectious Disease
- PTLDS and Chronic Lyme
- Lyme Neuroborreliosis
- Lyme Disease Overview
- Erythema Migrans Rash
- Tick-Borne Co-Infections
- Prevention and Tick Removal
- Tick Bite First Aid
- Lyme Testing Explained
- Alpha-Gal Syndrome
- Arthritis
- Meningitis
- Fatigue
- Lyme Carditis
- Headache
- Cat's Claw
- Immune Boosting