Rett Syndrome
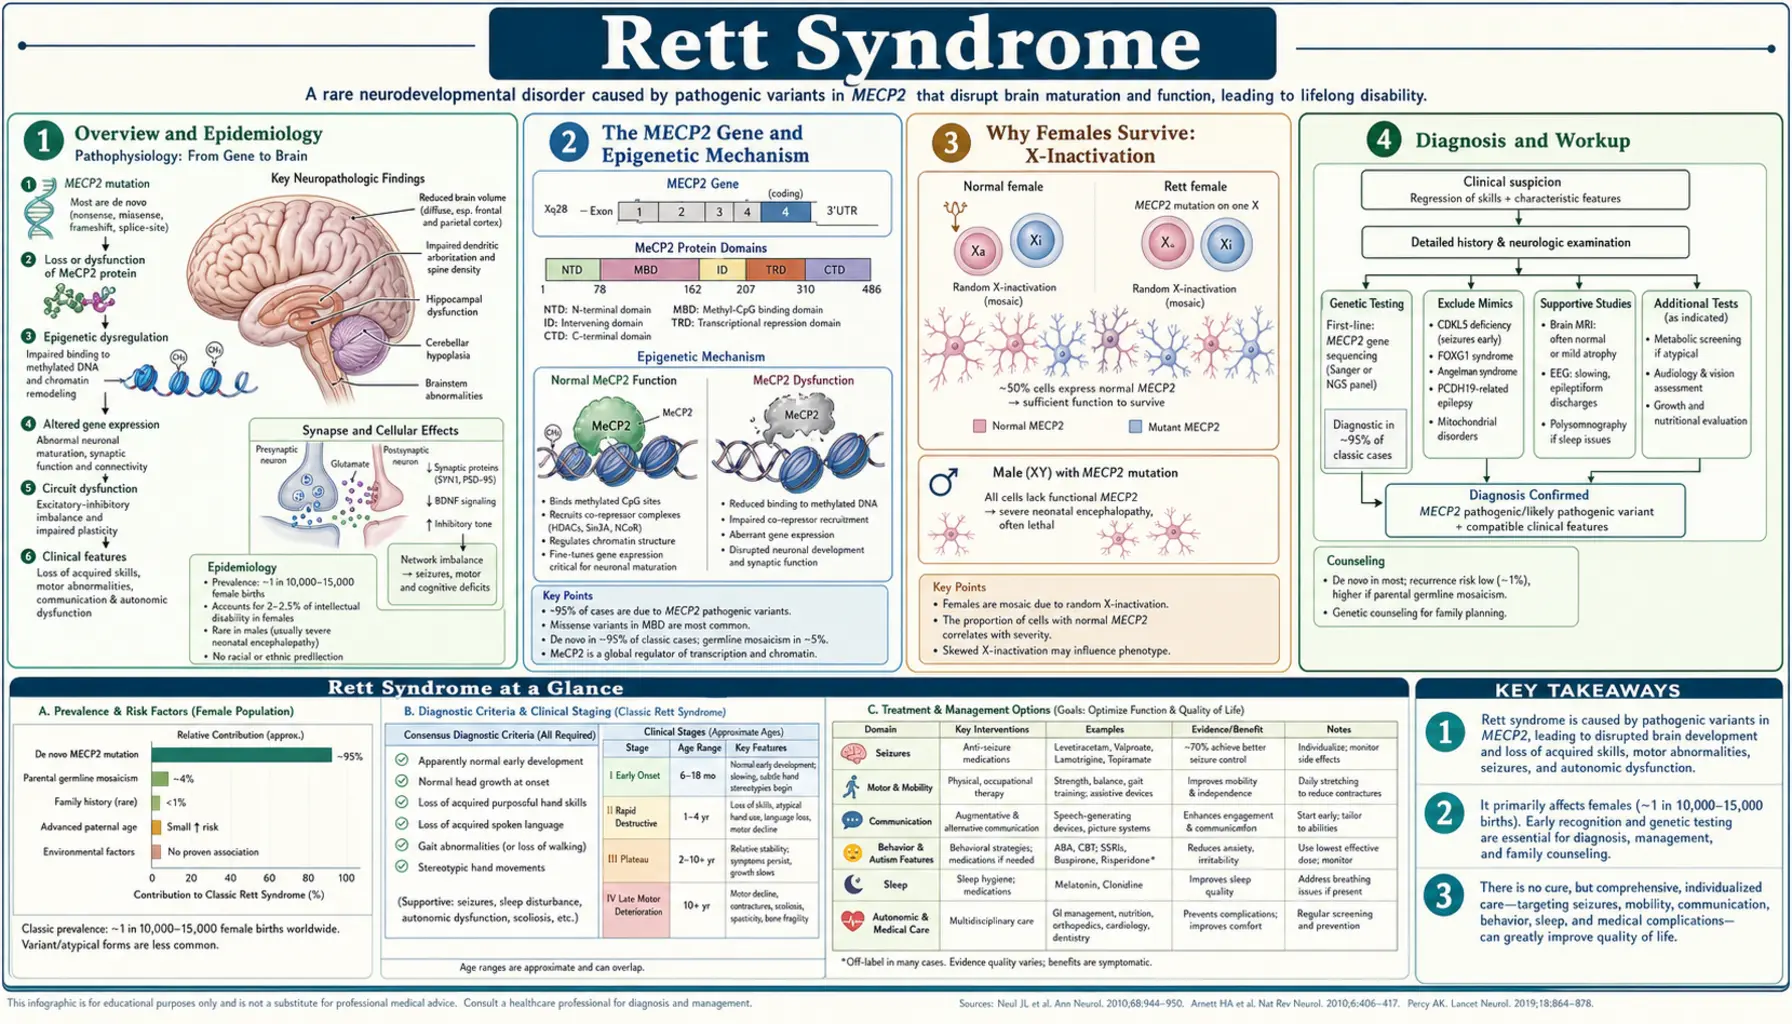
- Overview and Epidemiology
- The MECP2 Gene and Epigenetic Mechanism
- Why Females Survive: X-Inactivation
- Clinical Stages of Classic Rett Syndrome
- Diagnosis
- Seizures and Breathing Irregularities
- Cardiac Risks and Monitoring
- Management and Supportive Care
- Trofinetide — FDA-Approved 2023
- Gene Therapy and Future Directions
- Gene Therapies That Reached Children
- Key Research Papers
- Connections
Overview and Epidemiology
Rett syndrome (RTT) is a severe X-linked dominant neurodevelopmental disorder that affects almost exclusively females. It is one of the most common genetic causes of profound intellectual disability in girls worldwide. Unlike many genetic conditions that are apparent from birth, Rett syndrome has a deceptive early course — affected girls appear to develop normally for the first six to eighteen months of life, then enter a period of rapid and devastating regression that strips away the language, purposeful hand use, and social skills they had already gained.
The condition was first described in 1966 by Austrian pediatric neurologist Andreas Rett, who noticed a distinctive pattern of hand-wringing stereotypies and developmental regression in two girls sitting side by side in his waiting room. His original German-language reports were largely overlooked until 1983, when Swedish child neurologist Bengt Hagberg and colleagues published an English-language description of 35 cases in Annals of Neurology, bringing Rett syndrome to international attention.
The genetic cause — mutations in the MECP2 gene on the X chromosome — was identified in 1999 by Ruthie Amir and Huda Zoghbi at Baylor College of Medicine, transforming Rett syndrome from a clinical mystery into one of the best-understood epigenetic disorders in neuroscience.
How Common Rett Syndrome Is
Rett syndrome affects approximately 1 in 10,000 to 15,000 females. A 2023 pooled analysis of ten studies (9.57 million women, 673 cases) estimated 7.1 cases per 100,000 females (95% confidence interval 4.8 to 10.5), with all the estimates compatible with about 5 to 10 per 100,000. In the United States, this translates to roughly 6,000 to 9,000 affected individuals. Because it is an X-linked dominant condition and males with the typical mutation do not survive to birth or die in early infancy, essentially all patients are female. The condition occurs in all racial and ethnic groups at similar rates, with no geographic clustering, reflecting the fact that most cases arise from new (de novo) mutations rather than inherited ones. More than 99% of cases are sporadic — a daughter with Rett syndrome almost never has a mother with the condition.
The MECP2 Gene and Epigenetic Mechanism
The MECP2 gene sits at chromosome Xq28 — near the tip of the long arm of the X chromosome — and encodes methyl-CpG-binding protein 2 (MeCP2). Understanding what MeCP2 does at the molecular level is essential to understanding why its loss causes such widespread neurological damage.
What MeCP2 Does
MeCP2 is an epigenetic reader and interpreter. DNA methylation — the attachment of a methyl group to cytosine bases, especially at CpG dinucleotides — is one of the primary ways the genome marks genes for silencing. MeCP2 reads these methylation marks: it binds specifically to methylated CpG sites throughout the genome and recruits co-repressor complexes that lock those genes down. Think of DNA methylation as a "do not express" sticky note on a gene, and MeCP2 as the protein that reads that sticky note and calls in the silencing machinery.
In mature neurons, MeCP2 is expressed at exceptionally high levels — higher than in almost any other cell type. Neurons use MeCP2 constantly to suppress genes that should stay silent after the brain has finished its early development. When MeCP2 is lost or dysfunctional, those silencing signals are not enforced: genes that should remain quiet become inappropriately active in mature neurons, producing proteins that disrupt the finely tuned balance of neuronal circuits.
Brain Changes in Rett Syndrome
Post-mortem studies of Rett syndrome brains reveal several consistent findings: reduced brain weight (particularly in the frontal cortex and motor cortex), decreased synapse density, and abnormalities in dendritic branching. Neurons are smaller and more densely packed than normal — a pattern suggesting arrested maturation rather than cell death. The neurotransmitter systems most affected include dopamine, serotonin, and glutamate signaling pathways, which explains the broad clinical spectrum: movement abnormalities, mood dysregulation, seizures, and autonomic dysfunction all flow from disruptions in these interconnected systems.
Types of MECP2 Mutations
Over 200 distinct mutations in MECP2 have been associated with Rett syndrome, but eight recurring mutations account for approximately two-thirds of all cases. These are designated by the amino acid change they cause: R106W, R133C, T158M, R168X, R255X, R270X, R294X, and R306C. The letter-number combinations refer to the position in the protein and the amino acid substitution (e.g., R255X means the arginine at position 255 is replaced by a stop codon, truncating the protein).
Genotype-phenotype correlations — the relationship between which mutation a girl has and how severely she is affected — exist but are imperfect. In general, mutations that truncate the protein early (such as R168X) tend to produce more severe phenotypes, while mutations that preserve the methyl-binding domain (such as R294X or R306C) are sometimes associated with milder disease. However, the same mutation can produce substantially different severity in different girls, largely because of differences in X-inactivation patterns (see below).
The largest cohort studied, 1,052 participants assessed over 4,940 visits, found p.Arg133Cys (R133C), p.Arg294X (R294X) and p.Arg306Cys (R306C) relatively less severe, and p.Arg106Trp (R106W), p.Arg168X (R168X), p.Arg255X (R255X) and p.Arg270X (R270X) significantly more severe. For most mutation types, severity increased with age. Epilepsy followed a different pattern: in the Rett Natural History Study, specific MECP2 mutations were not significantly associated with how common or how severe seizures were.
Why Females Survive: X-Inactivation
One of the most fundamental questions about Rett syndrome is: why do girls survive when boys with the same mutation do not? The answer lies in a cellular process called X-inactivation (also called lyonization, after geneticist Mary Lyon who described it in 1961).
How X-Inactivation Works
Human females carry two X chromosomes — one from each parent. Early in embryonic development, each cell independently and randomly silences one of its two X chromosomes. From that point forward, every descendant of that cell carries the same silenced X. The result is that a normal adult female is a mosaic: roughly half her cells express genes from the maternal X chromosome, and the other half express genes from the paternal X chromosome. This mosaicism is permanent and is reflected in traits like the patchy coat color of calico cats.
Why Mosaicism Is Life-Saving in RTT
In a girl who carries an MECP2 mutation on one X chromosome, X-inactivation creates a cellular mosaic: approximately 50% of her neurons carry the mutant MECP2 allele on the active X (and therefore produce dysfunctional MeCP2), while the other 50% carry the normal allele on the active X (and produce functional MeCP2). This mixture of normal and abnormal neurons is what makes survival possible — the normal neurons provide enough MeCP2 function to sustain basic life, while the abnormal neurons cause the progressive neurological disorder.
Males, with only a single X chromosome, cannot have this mosaic rescue. A boy who inherits a classic RTT-causing MECP2 mutation has no cells producing normal MeCP2. The result is either fetal lethality (most affected male conceptuses do not survive to birth) or, in rare cases where the mutation is less severe, a devastating neonatal encephalopathy with hypotonia, respiratory failure, and early death. The only exceptions are males who are mosaic for the mutation (it arose post-fertilization, so some cells are unaffected) or males with Klinefelter syndrome (XXY) who, like females, have one X inactivated.
X-Inactivation Skewing
In some girls with Rett syndrome, X-inactivation is not 50:50 — it is "skewed," meaning a disproportionate fraction of cells may silence one X over the other. Favorable skewing (where the mutant X is preferentially silenced in more cells) can result in a milder phenotype; unfavorable skewing (where the normal X is more often silenced) can worsen outcomes. This is why two girls with identical MECP2 mutations can have significantly different clinical courses. Researchers are actively exploring whether X-inactivation skewing can be therapeutically manipulated.
Clinical Stages of Classic Rett Syndrome
Classic Rett syndrome unfolds across four recognizable clinical stages. Knowing these stages is crucial for parents, because the transition from Stage 1 to Stage 2 — the terrifying period of rapid regression — is often misinterpreted as autism, cerebral palsy, or a parenting problem before the correct diagnosis is made.
Stage 1: Early Onset Stagnation (Ages 6–18 Months)
For about the first six to eighteen months of life (7 to 18 months in the 1983 description, 6 to 18 months in the 1999 gene paper), girls with Rett syndrome appear to develop normally — they smile, babble, show social interest, and reach early motor milestones. Then, subtly at first, development stalls. The infant may seem less engaged, make less eye contact, or show decreased interest in toys. Head growth decelerates, leading to acquired microcephaly — a head circumference that was normal at birth but falls below the normal range over time as the brain fails to grow at the expected rate.
These early changes are easily missed or attributed to temperament. Parents often describe a vague sense that something is "different" but are reassured at well-child visits because no clear regression has yet occurred. Stage 1 may last from a few months to a year, and in retrospect it is often recognized only after the more dramatic Stage 2 begins.
Stage 2: Rapid Destructive Phase (Ages 1–4 Years)
Stage 2 is the defining period of Rett syndrome, and for families it is the most devastating. Over weeks to months, previously acquired skills disappear:
- Loss of purposeful hand use: The ability to reach for objects, pick up food, or hold a toy — skills the child had genuinely mastered — vanish. This is a true regression, not a developmental delay. Parents describe their daughter putting something down one day and never picking it up again.
- Hand stereotypies: As purposeful hand function disappears, repetitive, involuntary hand movements emerge and become constant. The classic movement is a hand-wringing or hand-washing motion — the hands clasp together at the midline and move in a continuous washing, squeezing, or wringing pattern. These stereotypies are pathognomonic of Rett syndrome (present in essentially all cases) and persist throughout the child's life. The hands may also be brought to the mouth repeatedly.
- Language loss: First words, then babbling, then any intentional vocalization disappear. Girls who had said "mama" or "dada" lose these words. Some lose language so rapidly that parents describe it as happening "overnight."
- Autistic features: Social withdrawal, reduced eye contact, and apparent disengagement emerge during this period, frequently leading to an initial diagnosis of autism. However, unlike classic autism, these social features partially improve in Stage 3.
- Seizures: Epilepsy often begins during Stage 2, usually between ages 2 and 5; in the Rett Natural History Study the estimated lifetime prevalence of epilepsy approached 90%. Seizure types vary: generalized tonic-clonic, myoclonic, and absence seizures are all seen.
- Abnormal breathing patterns: Waking-state breathing irregularities are a hallmark of Rett syndrome. Girls alternate between episodes of hyperventilation (rapid, deep breathing) and breath-holding (apnea), sometimes turning blue during the apneic episodes. The Rett Natural History Study describes this disturbance as occurring exclusively during wakefulness, which distinguishes it from sleep apnea. Breathing during sleep is not always normal, however: obstructive sleep apnea is a separate problem, described in the Seizures and Breathing section.
Stage 3: Plateau or Pseudo-Stationary Phase (Ages 2–10 Years)
After the turmoil of Stage 2, many girls enter a prolonged period of relative stability. Motor skills plateau rather than continuing to decline. Seizures often become somewhat better controlled with medication. Perhaps most movingly, girls in Stage 3 frequently show improvements in social engagement — they make better eye contact, seem more present, and may show flickers of improved communication. Many families describe Stage 3 as a period when they "get their daughter back" in some meaningful way, even though speech does not return. Hand stereotypies persist but may be less intense. Stage 3 is often the longest phase, lasting years to decades.
Stage 4: Late Motor Deterioration (Adult)
Stage 4 is characterized by progressive motor decline in older girls and women. Key features include:
- Scoliosis: Spinal curvature develops in the majority of patients and can be severe and rapidly progressive. Many require surgical spinal fusion. Managing scoliosis in RTT is complicated by the heightened anesthetic risk these patients carry (see Cardiac section).
- Parkinsonism-like features: Muscular rigidity and slow, effortful movement (bradykinesia) develop in many adults with RTT, resembling Parkinson disease features.
- Loss of ambulation: Some women who could walk in Stage 3 lose the ability to do so in Stage 4, though many retain ambulation into adulthood with consistent physical therapy.
- Cachexia: Progressive weight loss despite seemingly adequate caloric intake is a feature of Stage 4. The mechanism is not fully understood but involves autonomic dysfunction, increased energy expenditure from constant movement, and possible gastrointestinal dysmotility.
Women with Rett syndrome can live into their 50s and 60s. In the Rett Natural History Study (1,189 participants, 51 deaths at ages 3.9 to 66.6 years), survival for classic and atypical Rett syndrome was greater than 70% at 45 years, and most deaths were due to heart and breathing problems. Quality of life and longevity are significantly influenced by the quality of supportive care, scoliosis management, and seizure control.
Diagnosis
Rett syndrome is primarily a clinical diagnosis — a physician who recognizes the characteristic pattern of normal early development followed by regression, loss of hand use, and emergence of hand stereotypies in a girl can diagnose RTT on clinical grounds alone. Genetic confirmation is then sought to solidify the diagnosis and exclude differential diagnoses.
Diagnostic Criteria
The revised diagnostic criteria published in 2010 in Annals of Neurology define two forms:
Classic (typical) Rett syndrome requires a period of regression followed by recovery or stabilization, none of the exclusion criteria (brain injury from trauma, neurometabolic disease or severe infection; grossly abnormal development in the first six months of life), and all four main criteria:
- Partial or complete loss of purposeful hand skills
- Partial or complete loss of spoken language
- Gait abnormalities: impaired walking or no ability to walk
- Stereotypic hand movements such as wringing, squeezing, clapping, tapping, mouthing or washing motions
Atypical (variant) Rett syndrome requires a period of regression followed by recovery or stabilization, at least two of the four main criteria, and five of eleven supportive criteria: breathing disturbances when awake, tooth grinding (bruxism) when awake, impaired sleep pattern, abnormal muscle tone, circulation (peripheral vasomotor) disturbances, scoliosis or kyphosis, growth retardation, small cold hands and feet, inappropriate laughing or screaming spells, diminished response to pain, and intense eye communication. Atypical forms may have earlier or later onset, preserve some hand use, or have milder language loss.
Genetic Testing
MECP2 sequencing detects mutations in more than 95% of classic RTT cases. The eight most common mutations account for the majority of positive results. When sequencing is negative but clinical suspicion is high, deletion/duplication analysis is the next test described, as large deletions or duplications in MECP2 can cause RTT and are missed by sequencing alone.
It is important not to confuse classic RTT-causing mutations with MECP2 duplication syndrome, a completely separate condition. Males who carry an extra copy (duplication) of the entire MECP2 region develop a severe progressive encephalopathy with spastic quadriplegia, recurrent respiratory infections, and early death — a phenotype entirely distinct from classic Rett syndrome.
Variant Forms: CDKL5 and FOXG1
Two genes cause RTT-like phenotypes that were previously classified as atypical Rett syndrome but are now recognized as distinct conditions:
- CDKL5 deficiency disorder: Mutations in CDKL5 (cyclin-dependent kinase-like 5) cause seizures that begin in the first weeks of life, followed by RTT-like features including hand stereotypies and intellectual disability. The very early seizure onset (before age 5 months in most cases) distinguishes CDKL5 from classic RTT.
- FOXG1 syndrome (congenital variant): Mutations in the FOXG1 transcription factor gene cause a congenital form with profound intellectual disability, dyskinesia, and minimal or absent developmental milestone achievement from birth. These children never have a period of normal development, distinguishing them from classic RTT.
Differential Diagnosis
Before the characteristic hand stereotypies emerge and regression becomes obvious, Rett syndrome is most commonly mistaken for autism spectrum disorder (particularly in Stage 2 when autistic features are prominent) and cerebral palsy (due to motor difficulties). Angelman syndrome and other chromosomal disorders are sometimes considered in the differential. The combination of purposeful hand loss with emergence of midline hand-wringing movements in a previously developing girl is highly specific for RTT and is the usual reason for genetic testing.
Seizures and Breathing Irregularities
Epilepsy and breathing dysregulation are among the most challenging and frightening features of Rett syndrome for families. Understanding what is — and is not — dangerous is crucial for day-to-day management.
Epilepsy in RTT
In the Rett Natural History Study (922 people with classic Rett syndrome), the estimated lifetime prevalence of epilepsy approached 90%, while active seizures at any one time ranged from 30% to 44%; older reports gave lower lifetime figures (60 to 70 percent in a 2007 paper). Onset is most commonly during Stage 2. Of those with a history of epilepsy, only 74 (12%) were free of seizures and off anti-seizure medication at last contact. Seizures can take many forms: generalized tonic-clonic (the classic "grand mal"), myoclonic jerks, absence spells, and partial seizures with secondary generalization are all seen. Electroencephalogram typically shows generalized spike-wave discharges, often with a characteristic slow background rhythm.
Seizure control is variable. Some girls respond well to antiepileptic medications and achieve good seizure control; others have refractory epilepsy that is difficult to manage. The most commonly used medications include:
- Lamotrigine: Often the first-line agent; generally well tolerated and effective for both tonic-clonic and absence seizures in RTT.
- Levetiracetam: Broad-spectrum agent with minimal drug interactions; may worsen behavioral irritability in some girls.
- Valproate: Effective for multiple seizure types; requires monitoring for hepatotoxicity and thrombocytopenia, and carries weight gain risk that complicates nutritional management in RTT.
- Carbamazepine: Sometimes used, particularly when breathing irregularities overlap with seizure activity.
Importantly, seizure frequency often decreases naturally in Stage 3, even without medication changes. What families and caregivers sometimes label as "seizures" in older girls may actually be non-epileptic events — movement stereotypies, autonomic episodes, or startle reactions — and distinguishing these from true ictal events requires video-EEG monitoring.
Breathing Irregularities: What They Are and Why They Happen
The breathing pattern abnormalities in Rett syndrome are one of the most distinctive and alarming features for caregivers. Girls alternate between episodes of hyperventilation (rapid, deep over-breathing), irregular breathing, and complete breath-holding (apnea) that can last seconds to over a minute. During apneic episodes, girls may turn blue (cyanotic), stiffen, or appear to lose consciousness briefly.
These hyperventilation and breath-holding episodes occur while awake. The Rett Natural History Study (1,185 participants analyzed) describes the disturbance as occurring exclusively during wakefulness, with nearly 100% of people with classic Rett syndrome affected over the lifespan. The awake pattern is attributed to dysfunction in the brain stem circuits that regulate voluntary breathing, not to a structural airway problem or central respiratory failure. Stopping in sleep applies to this awake pattern only; other breathing problems do occur during sleep (see below), and the studies cited here do not report how many deaths in Rett syndrome happen during sleep.
The breath-holding episodes are frightening to witness and can cause short drops in blood oxygen. The brain's automatic breathing reflex is described as eventually overriding the breath-hold so that breathing resumes. The same study reports that the disturbance is distressing and can even prompt emergency resuscitation, and that it is associated with function, quality of life and risk for cardiac dysrhythmia; prolonged corrected QT interval on the electrocardiogram was one of the factors linked to severe breathing dysfunction. Remission was common, lasting 1 year on average. There is currently no consistently effective pharmacologic treatment for the breathing irregularities in RTT, though carbamazepine has been tried with variable results. Management is described as primarily reassurance, education, and caregivers remaining calm during episodes; the 2020 consensus guideline states that there are currently no medications or treatments for these daytime episodes.
Sleep Apnea Is a Separate Problem
Obstructive sleep apnea, in which the airway is blocked during sleep, is different from awake breath-holding. Among 13 children with Rett syndrome referred to one sleep clinic, 9 (69.2%) had it and 4 of those had severe obstructive sleep apnea; one child also had central sleep apnea. The mean lowest blood oxygen during the sleep study was 88.52%. Snoring (77%) and witnessed apnea (53.8%) were the most common complaints, and treatment included adenotonsillectomy, the removal of tonsils and adenoids (23.1%), and positive airway pressure (15%). In a second study of 66 females with typical Rett syndrome who had apneas, obstructive apneas with an apnea-hypopnea index above 15 were present in 69.7%. Both groups were selected (referred for sleep concerns, or already known to have apneas), so these figures do not describe all girls with Rett syndrome. The 2020 consensus guideline lists a check of the tonsils and consideration of a full sleep study when night-time apneas are present.
Cardiac Risks and Monitoring
Heart involvement in Rett syndrome is one of the most medically serious and underappreciated aspects of the condition. Women and girls with RTT have a substantially elevated risk of sudden unexpected death — and a major contributor to this risk is cardiac arrhythmia driven by prolonged QT interval.
Prolonged QT Interval in RTT
The QT interval on an electrocardiogram (ECG) represents the time it takes for the heart's ventricles to electrically recover after each heartbeat. When this interval is prolonged, the heart is vulnerable to a dangerous arrhythmia called torsades de pointes — a rapid, disorganized rhythm that can degenerate into ventricular fibrillation and sudden cardiac death.
Electrocardiograms of 379 people with Rett syndrome showed prolongation of the corrected QT interval in 18.5%, a higher prevalence than in the general population. The same 2011 paper tested the cause in mice: deleting MeCP2 in the nervous system alone caused long QT and ventricular tachycardia, and heart cells from mice lacking MeCP2 showed increased persistent sodium current. The authors concluded that the heart problems are secondary to abnormal nervous system control. In those male mice, beta-blockers did not prevent ventricular tachycardia, and the sodium channel-blocking drug phenytoin reduced it; these are animal results. A 2022 study in female Rett-model mice also found delayed heart cell recovery (repolarization), which a late sodium current blocker reduced in isolated heart cells.
Clinical Implications
The cardiac implications for RTT management are practical and important. The checks and precautions below are those described in the 2020 consensus guideline and in RTT care more generally:
- Annual electrocardiogram screening: the 2020 consensus guideline lists a yearly electrocardiogram to check for a prolonged QTc interval, which can develop at any time, with referral to a cardiologist if it is abnormal.
- QT-prolonging medications: the 2020 consensus guideline states to avoid prescribing medications that can prolong the QTc interval, naming fluoxetine as an example. Many commonly used drugs — including certain antiepileptics, antipsychotics, antibiotics (azithromycin, clarithromycin, fluoroquinolones), and antihistamines — prolong the QT interval and can trigger fatal arrhythmias in susceptible individuals. A new medication's effect on the heart is therefore a known concern in RTT before it is started.
- Anesthesia requires cardiac monitoring. The combination of QT prolongation and autonomic dysregulation makes general anesthesia significantly higher risk in RTT than in the general pediatric population. Scoliosis surgery — often necessary in RTT — therefore requires experienced cardiac monitoring and anesthesia teams familiar with the RTT cardiac phenotype. The 2020 consensus guideline recommends a current electrocardiogram before anesthesia.
- Sudden unexplained death in RTT (SUDEP-equivalent): A British survey put overall mortality in Rett syndrome at 1.2% per year, and 26% of those deaths were sudden and unexpected. Sudden death is described as substantially more common than in age-matched peers. Arrhythmia is thought to be a leading mechanism, though autonomic dysregulation contributing to respiratory arrest during an autonomous event may also play a role.
Teaching families about cardiac risk, a medication safety card listing QT-prolonging drugs, and cardiologists familiar with RTT on the multidisciplinary care team are all described as part of care for affected individuals.
Management and Supportive Care
There is currently no cure for Rett syndrome. Management is multidisciplinary, supportive, and symptom-directed. Despite the severity of the condition, quality of life can be substantially improved with comprehensive care, and many women with RTT live meaningful lives with strong family and community support.
Seizure Management
Antiepileptic drug selection is guided by seizure type, electroencephalogram findings, and the critical constraint of cardiac safety (avoiding QT-prolonging agents). Polypharmacy is common in refractory cases. The ketogenic diet has been used with some success in RTT-associated epilepsy when medications fail, and its high-fat composition may also benefit the nutritional challenges of Stage 4. Video-EEG monitoring helps distinguish true seizures from non-epileptic events, preventing unnecessary medication escalation.
Communication and Augmentative Technology
Perhaps the most important rehabilitation insight in RTT is that language comprehension is substantially preserved even when expressive language is completely absent. Girls with RTT understand far more than they can express. Eye-gaze communication technology — devices that track eye movements to select letters, words, or symbols on a screen — has been transformative for many families, allowing affected individuals to express preferences, answer questions, and participate in decisions about their own care. Low-tech options (picture boards, eye-pointing to choices) provide access when electronic devices are unavailable. Speech-language pathologists specializing in augmentative and alternative communication (AAC) are essential members of the RTT care team.
Physical and Occupational Therapy
Physical therapy focuses on maintaining mobility, weight-bearing, and muscle tone. Walking ability in Stage 3 is associated with better long-term motor outcomes, and structured PT programs help preserve ambulation. Aquatic therapy is particularly well-tolerated in RTT and may improve tone regulation, balance, and mood. Occupational therapy addresses hand use, adaptive equipment, and daily living skills, working around the involuntary hand stereotypies.
Scoliosis Management
Scoliosis develops in the majority of RTT patients and requires active monitoring with spine radiographs at regular intervals. Mild curvature may be managed with positioning and supportive seating. Progressive curvature is initially approached with bracing, though bracing is less effective in RTT than in idiopathic adolescent scoliosis. Severe curvature (generally greater than 40–50 degrees) typically requires surgical spinal fusion. Surgical planning takes account of the elevated cardiac and anesthetic risks described above, and surgical teams experienced with neurologically complex patients are the usual referral.
Nutritional Support
Weight management in RTT is complicated by two opposing forces: the increased caloric expenditure from constant movement and stereotypies, and the progressive dysphagia and chewing difficulties that reduce intake in Stage 4. High-calorie dietary supplementation is frequently needed. Gastrostomy tube (G-tube) placement provides reliable nutritional access for patients with severe dysphagia or weight loss, and many families report improved quality of life after G-tube placement because mealtimes become less stressful and nutrition becomes more reliable.
Autonomic and Sleep Dysfunction
Autonomic nervous system dysregulation underlies many RTT symptoms beyond breathing: constipation, cold hands and feet, irregular heart rate variability, and temperature regulation problems are common. Sleep disturbances — difficulty falling asleep, frequent night waking, and daytime sleepiness — affect the majority of RTT patients and significantly impact family functioning. Melatonin is the most commonly used sleep aid, with reasonable safety data in this population. Environmental modifications (consistent schedules, darkening, white noise) are complementary.
Trofinetide — FDA-Approved 2023
In March 2023, the U.S. Food and Drug Administration approved trofinetide for the treatment of Rett syndrome in patients aged 2 years and older — making it the first drug ever specifically approved for RTT. This approval marked a historic milestone after decades in which management was entirely symptomatic and no drug had demonstrated efficacy in rigorous clinical trials.
What Trofinetide Is
Trofinetide is a synthetic analog of glycine-proline-glutamate (GPE), a naturally occurring tripeptide derived from insulin-like growth factor 1 (IGF-1). The FDA label states that the mechanism by which it works in Rett syndrome is unknown. Two mechanisms have been proposed: modulating insulin-like growth factor 1 receptor signaling, which supports neuronal survival and synaptic plasticity, and reducing neuroinflammation by suppressing microglial activation. Both pathways are implicated in the synaptic deficits observed in RTT brains.
The LAVENDER Trial
The approval was based largely on the Phase 3 LAVENDER trial, published in Nature Medicine in 2023. This randomized, double-blind, placebo-controlled 12-week trial enrolled 187 females with RTT aged 5 to 20 years. Patients receiving trofinetide showed statistically significant improvements compared to placebo on the caregiver-completed Rett Syndrome Behaviour Questionnaire (RSBQ; change of −4.9 versus −1.7, P = 0.0175) and the clinician-rated Clinical Global Impression-Improvement scale (CGI-I; 3.5 versus 3.8, P = 0.0030). A communication score, the key secondary measure, changed by −0.1 versus −1.1 (P = 0.0064). Hand use and breathing are among the areas the clinician-rated scale covers, according to the trial's design paper; the trial abstract does not report them as separate results. The authors concluded that the results suggest benefit for the core symptoms of RTT.
What to Expect from Trofinetide
Trofinetide is not a cure, and it does not reverse the underlying genetic defect. The improvements seen in trials, while statistically significant and clinically meaningful to affected individuals, are modest in absolute terms: in LAVENDER, effect sizes (Cohen's d) were 0.37 on the caregiver questionnaire, 0.47 on the clinician scale and 0.43 on the communication score. Not every patient responds, and the degree of benefit varies. However, for a disease with no prior pharmacologic treatment, even modest gains in communication or reduction in distressing behaviors represent a meaningful advance.
Trofinetide is administered orally or through a gastrostomy tube as a liquid solution or a powder dissolved in liquid, dosed by weight twice daily. The most common side effects are gastrointestinal: diarrhea occurs in approximately 80% of patients and weight loss in a substantial proportion. In LAVENDER, 17.2% of those on trofinetide withdrew because of side effects, versus 2.1% on placebo, and 12.9% withdrew because of diarrhea; 75% of those on trofinetide finished the 12 weeks. A diarrhea plan was introduced partway through the trial: adjusting or stopping laxatives, adding fiber supplements and antidiarrheal medication, and lowering or pausing the dose. Dose reduction and supportive management (anti-diarrheal agents, dietary adjustments) can help manage gastrointestinal (GI) effects. The drug is expensive, and insurance coverage requires prior authorization with documentation of RTT diagnosis.
Earlier Trials
Two smaller Phase 2 double-blind randomized trials came first: one in 56 adolescent and adult females, published in Pediatric Neurology in 2017, and one in 82 girls aged 5 to 15, published in Neurology in 2019. They demonstrated trofinetide's safety profile and provided preliminary efficacy signals that supported the larger LAVENDER trial design. The progression from the 2019 Phase 2 result to U.S. Food and Drug Administration (FDA) approval took approximately four years, an exceptionally rapid timeline for a rare pediatric neurological condition.
Later Trofinetide Studies
Two later studies had no placebo group. In LILAC, a 40-week open-label extension of LAVENDER (154 participants aged 5 to 21), diarrhea occurred in 74.7% and vomiting in 28.6%, and diarrhea was the most common reason for leaving treatment (21.4%). In DAFFODIL, an open-label study of 15 girls aged 2 to 4, diarrhea occurred in 80.0% and vomiting in 53.3%, all mild or moderate.
What the FDA Label Lists
- Diarrhea: across the main trial and long-term studies, 85% had diarrhea and 49% had it persist or return despite dose changes or antidiarrheal medicine; it was mild or moderate in 96% of cases. The FDA label advises stopping laxatives before starting trofinetide and lists dehydration and severe diarrhea as reasons to pause, lower or stop the dose.
- Weight loss: 12% lost more than 7% of body weight, versus 4% on placebo.
- Vomiting: 29% versus 12% on placebo. People with Rett syndrome are at risk of breathing food or fluid into the lungs (aspiration), and aspiration and aspiration pneumonia have been reported after vomiting on trofinetide.
- Heart rhythm: at the maximum recommended dose in healthy adults, trofinetide does not prolong the QT interval to any clinically relevant extent. That testing was in healthy adults, not in people with Rett syndrome.
Gene Therapy and Future Directions
The identification of a single causative gene — MECP2 — made Rett syndrome an early and natural target for gene therapy approaches. The proof-of-concept was established in a landmark 2007 Science paper by Jacky Guy and Adrian Bird at the University of Edinburgh, who showed that reactivating MeCP2 expression in adult mice with established RTT-like neurological symptoms reversed those symptoms. This experiment demonstrated that RTT is not simply a developmental catastrophe — mature neurons retain the capacity to recover if MeCP2 function is restored. This finding fundamentally changed the research landscape and launched a wave of gene therapy development.
The Challenge: MeCP2 Dosage Is Critical
Gene therapy for RTT faces a fundamental and unusual challenge: MeCP2 expression must be precisely calibrated. Too little MeCP2 causes RTT; too much MeCP2 is equally toxic. Males who carry a duplication of the MECP2 gene — producing about twice the normal amount of MeCP2 protein — develop a severe progressive encephalopathy called MECP2 duplication syndrome. This means gene therapy cannot simply deliver as much MeCP2 as possible; it must deliver the right amount to each neuron. Achieving this precision in vivo, across billions of neurons in a human brain, is a formidable technical problem.
Current Clinical Trials
Several gene therapy approaches have been explored, in clinical trials or at earlier stages; the two most advanced are described in the next section:
- AAV-MECP2 intrathecal delivery: Adeno-associated viral vectors carrying a functional MECP2 gene are injected into the spinal fluid (intrathecal space), allowing widespread distribution to neurons throughout the brain and spinal cord. Regulatory elements in the vector's promoter region are designed to limit MeCP2 expression to levels that mirror natural expression, preventing over-expression toxicity.
- Self-complementary AAV approaches: Modifications to standard AAV vectors designed to improve transduction efficiency in neurons without increasing dosing.
- RNA-based strategies: Antisense oligonucleotides and other RNA-targeting approaches aimed at modulating MeCP2 expression levels rather than replacing the gene outright.
Early results from Phase 1 trials were reported with initial safety data appearing acceptable, before the fatal reaction described in the next section. Efficacy signals are being evaluated carefully, with the caveat that Phase 1 trials are primarily designed to establish safe dosing, not to demonstrate efficacy.
Other Therapeutic Targets
Beyond gene therapy, several other biological targets are under investigation:
- Insulin-like growth factor 1 and related pathways: Recombinant insulin-like growth factor 1 (mecasermin) has been studied in RTT; a 2018 placebo-controlled crossover trial in 30 girls found no significant improvement, some measures worsened, and a secondary analysis found improvements on one measure of stereotypic behavior and one of social communication. The pathway remains a therapeutic target, which is part of the rationale for trofinetide.
- Brain-derived neurotrophic factor (BDNF) enhancement: Brain-derived neurotrophic factor is reduced in RTT brains; strategies to increase brain-derived neurotrophic factor signaling are under investigation.
- Serotonergic agents: Given the serotonin pathway disruption in RTT, agents modulating serotonin signaling (including dextromethorphan and others) have been explored with limited results to date. Dextromethorphan was tested in RTT as a blocker of the NMDA receptor rather than as a serotonin drug: in a randomized open-label trial of 35 girls, statistically significant dose-dependent improvements were seen in seizures, receptive language and hyperactivity, with no significant change in overall severity.
- X-inactivation manipulation: Targeted efforts to preferentially silence the mutant X chromosome in more cells — effectively increasing the proportion of neurons producing normal MeCP2 — represent an elegant conceptual approach, though implementation in differentiated neurons remains technically challenging.
The RTT research community has been energized by the success of trofinetide's approval and by the promise of gene therapy trials. For a condition that had no disease-modifying treatments for decades, the current pipeline represents unprecedented momentum.
Gene Therapies That Reached Children
A 2026 review for neurologists describes two gene replacement therapies as the most advanced in clinical trials. Both trials are open-label, with results compared to what is known of the natural course of the disease rather than to a placebo group.
- TSHA-102: a shortened (mini) MECP2 gene with a built-in microRNA brake on how much protein is made, given once into the spinal fluid by lumbar puncture. In the first part of the REVEAL studies, all six participants gained or regained at least one developmental milestone considered highly unlikely without treatment (under 6.7% milestone gain in girls aged 6 or older in natural-history data). The pivotal part of the program plans to enroll 15 females aged 6 to under 22; as of May 2025, 12 participants had been treated.
- NGN-401: a full-length MECP2 gene with a synthetic feedback circuit, delivered into the fluid spaces of the brain (intracerebroventricular). The EMBOLDEN trial began as a Phase 1/2 dose-escalation study and has moved to a pivotal open-label, single-arm trial. The first four girls treated at the low dose gained 23 developmental skills between them.
The same review describes a death. One participant given the high dose of NGN-401 developed a whole-body hyperinflammatory syndrome several days after dosing, with fever, low blood counts and multi-organ dysfunction, and died despite treatment. Two other participants had received the same dose without this reaction. High-dose treatment was stopped immediately and the maximum dose was capped.
Key Research Papers
- Amir RE, Van den Veyver IB, Wan M, et al. Rett syndrome is caused by mutations in X-linked MECP2, encoding methyl-CpG-binding protein 2. Nat Genet. 1999;23(2):185–188. — The landmark paper identifying MECP2 mutations as the cause of Rett syndrome. — PubMed PMID: 10508514
- Hagberg B, Aicardi J, Dias K, Ramos O. A progressive syndrome of autism, dementia, ataxia, and loss of purposeful hand use in girls: Rett's syndrome: report of 35 cases. Ann Neurol. 1983;14(4):471–479. — The first major English-language clinical description that established RTT as a recognized syndrome. — PubMed PMID: 6638958
- Guy J, Hendrich B, Holmes M, Martin JE, Bird A. A mouse Mecp2-null mutation causes neurological symptoms that mimic Rett syndrome. Nat Genet. 2001;27(3):322–326. — Established the Mecp2-null mouse as the definitive animal model for RTT research. — PubMed PMID: 11242117
- Guy J, Gan J, Selfridge J, Cobb S, Bird A. Reversal of neurological defects in a mouse model of Rett syndrome. Science. 2007;315(5815):1143–1147. — Demonstrated that restoring MeCP2 expression in adult symptomatic mice reversed RTT-like symptoms, opening the door to gene therapy. — PubMed PMID: 17289941
- Neul JL, Kaufmann WE, Glaze DG, et al. Rett syndrome: revised diagnostic criteria and nomenclature. Ann Neurol. 2010;68(6):944–950. — The current consensus diagnostic criteria used clinically worldwide. — PubMed PMID: 21154482
- Cuddapah VA, Pillai RB, Shekar KV, et al. Methyl-CpG-binding protein 2 (MECP2) mutation type is associated with disease severity in Rett syndrome. J Med Genet. 2014;51(3):152–158. — Genotype-phenotype analysis characterizing which mutations associate with milder versus more severe clinical outcomes. — PubMed PMID: 24399845
- Glaze DG, Neul JL, Percy A, et al. A double-blind, randomized, placebo-controlled clinical study of trofinetide in the treatment of Rett syndrome. Pediatr Neurol. 2017;76:37–46. — Phase 2 clinical trial in 56 adolescent and adult females establishing trofinetide's safety profile and preliminary efficacy signals. — PubMed PMID: 28964591
- Glaze DG, Neul JL, Kaufmann WE, et al. Double-blind, randomized, placebo-controlled study of trofinetide in pediatric Rett syndrome. Neurology. 2019;92(16):e1912–e1925. — Phase 2 clinical trial in 82 girls aged 5 to 15. — PubMed PMID: 30918097
- Neul JL, Percy AK, Benke TA, et al. Design and outcome measures of LAVENDER, a phase 3 study of trofinetide for Rett syndrome. Contemp Clin Trials. 2022;114:106704. — Lists the areas the clinician-rated scale covers, including hand use and breathing. — PubMed PMID: 35149233
- Neul JL, Percy AK, Benke TA, et al. Trofinetide for the treatment of Rett syndrome: a randomized phase 3 study. Nat Med. 2023;29(6):1468–1475. — The pivotal Phase 3 trial (LAVENDER) supporting FDA approval of trofinetide in 2023. — PubMed PMID: 37291210
- Weaving LS, Ellaway CJ, Gécz J, Christodoulou J. Rett syndrome: clinical review and genetic update. J Med Genet. 2005;42(1):1–7. — Comprehensive clinical review covering molecular genetics, phenotypic spectrum, and differential diagnosis. — PubMed PMID: 15635068
- Moser SJ, Weber P, Lütschg J. Rett syndrome: clinical and electrophysiologic aspects. Pediatr Neurol. 2007;36(2):95–100. — Compares electroencephalogram stages with clinical stages in 11 patients; 60 to 70 percent of patients develop epilepsy, and some typical symptoms are hard to tell from seizures. — PubMed PMID: 17275660
- Katz DM, Bird A, Coenraads M, et al. Rett syndrome: crossing the threshold to clinical translation. Trends Neurosci. 2016;39(2):100–113. — Reviews the translational pipeline from mouse models to clinical trials and identifies key remaining hurdles. — PubMed PMID: 26830113
- Ip JPK, Mellios N, Sur M. Rett syndrome: insights into genetic, molecular and circuit mechanisms. Nat Rev Neurosci. 2018;19(6):368–382. — State-of-the-art review of MeCP2 biology, circuit-level dysfunction, and therapeutic targets. — PubMed PMID: 29740174
- Sarber KM, Howard JJM, Dye TJ, Pascoe JE, Simakajornboon N. Sleep-disordered breathing in pediatric patients with Rett syndrome. J Clin Sleep Med. 2019;15(10):1451–1457. — Sleep studies in 13 referred children; 69.2% had obstructive sleep apnea. — PubMed PMID: 31596210
- Leoncini S, Signorini C, Boasiako L, et al. Breathing abnormalities during sleep and wakefulness in Rett syndrome: clinical relevance and paradoxical relationship with circulating pro-oxidant markers. Front Neurol. 2022;13:833239. — Breathing monitored awake and asleep in 66 females with typical Rett syndrome and apneas. — PubMed PMID: 35422749
- Tarquinio DC, Hou W, Neul JL, et al. The course of awake breathing disturbances across the lifespan in Rett syndrome. Brain Dev. 2018;40(7):515–529. — Rett Natural History Study of awake breathing dysfunction, 1,185 participants analyzed. — PubMed PMID: 29657083
- Kerr AM, Armstrong DD, Prescott RJ, Doyle D, Kearney DL. Rett syndrome: analysis of deaths in the British survey. Eur Child Adolesc Psychiatry. 1997;6 Suppl 1:71–74. — Mortality of 1.2% per year, 26% of deaths sudden and unexpected. — PubMed PMID: 9452925
- McCauley MD, Wang T, Mike E, et al. Pathogenesis of lethal cardiac arrhythmias in Mecp2 mutant mice: implication for therapy in Rett syndrome. Sci Transl Med. 2011;3(113):113ra125. — Electrocardiograms of 379 people, with mouse studies of the cause. — PubMed PMID: 22174313
- Cheng H, Charles I, James AF, Abdala AP, Hancox JC. QTc interval and ventricular action potential prolongation in the Mecp2Null/+ murine model of Rett syndrome. Physiol Rep. 2022;10(19):e15437. — Study in female mice and their heart cells. — PubMed PMID: 36200140
- Tarquinio DC, Hou W, Berg A, et al. Longitudinal course of epilepsy in Rett syndrome and related disorders. Brain. 2017;140(2):306–318. — Lifetime prevalence of epilepsy approaching 90%. — PubMed PMID: 28007990
- Tarquinio DC, Hou W, Neul JL, et al. The changing face of survival in Rett syndrome and MECP2-related disorders. Pediatr Neurol. 2015;53(5):402–411. — Survival greater than 70% at 45 years in 1,189 participants. — PubMed PMID: 26278631
- Petriti U, Dudman DC, Scosyrev E, Lopez-Leon S. Global prevalence of Rett syndrome: systematic review and meta-analysis. Syst Rev. 2023;12(1):5. — Pooled prevalence of 7.1 per 100,000 females. — PubMed PMID: 36642718
- Fu C, Armstrong D, Marsh E, et al. Consensus guidelines on managing Rett syndrome across the lifespan. BMJ Paediatr Open. 2020;4(1):e000717. — Consensus checklist of care, including yearly electrocardiograms. — PubMed PMID: 32984552
- O'Leary HM, Kaufmann WE, Barnes KV, et al. Placebo-controlled crossover assessment of mecasermin for the treatment of Rett syndrome. Ann Clin Transl Neurol. 2018;5(3):323–332. — Crossover trial in 30 girls. — PubMed PMID: 29560377
- Smith-Hicks CL, Gupta S, Ewen JB, et al. Randomized open-label trial of dextromethorphan in Rett syndrome. Neurology. 2017;89(16):1684–1690. — Open-label trial in 35 girls. — PubMed PMID: 28931647
- Percy AK, Neul JL, Benke TA, et al. Trofinetide for the treatment of Rett syndrome: results from the open-label extension LILAC study. Med. 2024;5(9):1178–1189.e3. — 40-week open-label extension of LAVENDER, 154 participants. — PubMed PMID: 38917793
- Percy AK, Ryther R, Marsh ED, et al. Results from the phase 2/3 DAFFODIL study of trofinetide in girls aged 2-4 years with Rett syndrome. Med. 2025;6(6):100608. — Open-label study of 15 girls. — PubMed PMID: 40043705
- Samanta D. Disease-modifying therapies for Rett syndrome: a review for neurologists. Front Neurol. 2026;17:1766679. — Reviews TSHA-102 and NGN-401, including a fatal hyperinflammatory adverse event. — PubMed PMID: 41641323
PubMed Topic Searches
Connections
- Genetics
- Angelman Syndrome — the closest differential diagnosis: another neurodevelopmental disorder with absent speech, seizures, and stereotyped hand movements.
- Autism Spectrum Disorder (ASD) — the autistic features of Stage 2 regression frequently lead to an initial autism diagnosis before RTT is recognized.
- Epilepsy — the estimated lifetime prevalence of epilepsy in Rett syndrome approached 90% in the Rett Natural History Study, with onset often during the Stage 2 regression period.
- Long QT Syndrome — QT prolongation was found in 18.5% of 379 people with RTT and is linked to the elevated sudden-death and anesthetic risk.
- Scoliosis — spinal curvature develops in the majority of RTT patients and often requires bracing or surgical fusion.
- Neurology