Laryngopharyngeal Reflux (LPR)
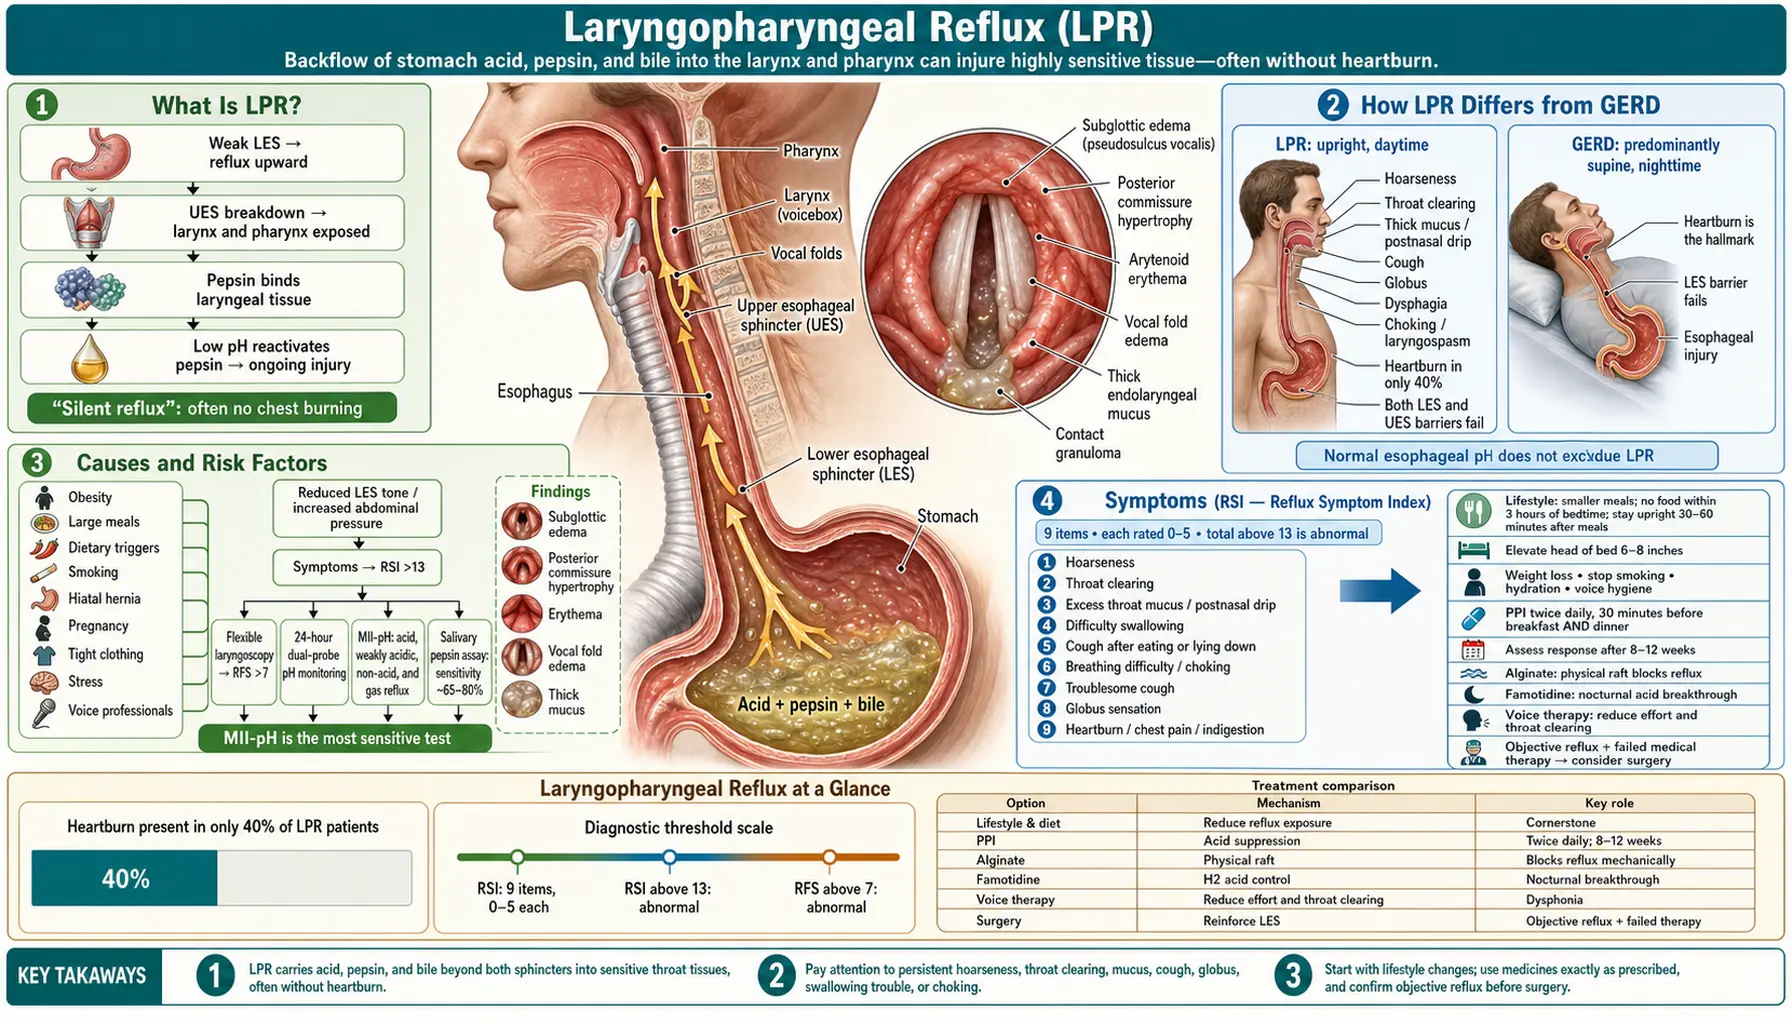
Table of Contents
- What Is LPR?
- How LPR Differs from Gastroesophageal Reflux Disease
- Causes and Risk Factors
- Symptoms (RSI — Reflux Symptom Index)
- Laryngoscopy Findings (Reflux Finding Score)
- Diagnosis
- Dietary and Lifestyle Changes
- Medications (Proton Pump Inhibitors and Beyond)
- When Surgery Is Needed
- Key Research Papers
- Connections
- Featured Videos
What Is LPR?
LPR (laryngopharyngeal reflux) is the backflow of gastric contents — stomach acid, pepsin, and bile — past the upper esophageal sphincter into the larynx and pharynx. Unlike typical heartburn (GERD), LPR often occurs without any burning sensation in the chest. Gastroenterologists and ENT specialists call it "silent reflux" because patients frequently have no classic reflux symptoms, yet the laryngeal tissues suffer significant chemical injury with every reflux event.
The larynx (voicebox) is exquisitely sensitive to stomach acid and especially to pepsin. While the esophagus can tolerate some acid exposure, a single drop of pepsin-containing fluid on the vocal cords can trigger hours of irritation, mucus production, and swelling. This extreme sensitivity is the defining feature of LPR.
How LPR Differs from Gastroesophageal Reflux Disease
Gastroesophageal reflux disease (GERD) and LPR share the same underlying mechanism — a weakened lower esophageal sphincter allowing gastric fluid to reflux upward — but they differ in important ways:
- Timing: gastroesophageal reflux disease is predominantly supine (nighttime); LPR often occurs upright, during the day
- Symptoms: Heartburn is the hallmark of gastroesophageal reflux disease; only 40% of LPR patients have heartburn
- Damage threshold: The esophagus tolerates many acid episodes before showing injury; the larynx is damaged by a single event
- Upper barrier: LPR requires breakdown of both the lower esophageal sphincter AND the upper esophageal sphincter (UES)
- pH probe findings: Many LPR patients have normal esophageal pH monitoring because reflux reaches only the larynx, not the esophagus
The pepsin protein plays a central and underappreciated role. Pepsin (a digestive enzyme) remains bound to laryngeal tissues even after acid is neutralized and becomes reactivated at low pH, causing ongoing damage long after reflux events end. Salivary pepsin assays are now being studied as diagnostic biomarkers.
Causes and Risk Factors
The primary cause is dysfunction of the upper and lower esophageal sphincters, allowing gastric contents to reach the throat. Contributing factors include:
- Obesity: Increases intra-abdominal pressure, forcing gastric contents upward
- Dietary triggers: Fatty foods, chocolate, caffeine, alcohol, carbonated beverages, citrus, tomato products, spicy foods, and peppermint — all reduce lower esophageal sphincter (LES) pressure
- Large meals: Eating 2–3 hours before lying down, overeating
- Smoking: Reduces LES tone and saliva production (saliva neutralizes acid)
- Hiatal hernia: Allows stomach to shift above the diaphragm, disrupting the anti-reflux barrier
- Pregnancy: Increased intra-abdominal pressure plus progesterone-mediated LES relaxation
- Tight clothing: External abdominal compression
- Stress: Increases gastric acid secretion and esophageal hypersensitivity
- Voice professionals: Singers and teachers who use their voice heavily create intrathoracic pressure changes that promote reflux
Symptoms (RSI — Reflux Symptom Index)
The Reflux Symptom Index (RSI), developed by Belafsky et al. in 2002, is a validated 9-item questionnaire for diagnosing LPR. Each symptom is rated 0–5 (0 = no problem, 5 = severe); a total score above 13 is considered abnormal and suggests LPR.
The nine RSI symptoms:
- Hoarseness or a problem with your voice — intermittent dysphonia, often worst in the morning after overnight recumbency
- Clearing your throat — one of the most characteristic complaints; habitual, involuntary clearing from laryngeal irritation and mucus accumulation
- Excess throat mucus or postnasal drip — thick, sticky mucus coating the posterior pharynx
- Difficulty swallowing food, liquids, or pills — mild dysphagia from laryngeal edema
- Coughing after eating or after lying down — pepsin stimulates cough receptors in the larynx
- Breathing difficulties or choking episodes — laryngospasm can occur in severe LPR
- Troublesome or annoying cough — persistent dry cough, often misdiagnosed as post-viral or ACE-inhibitor cough
- Sensations of something sticking in your throat or a lump in your throat — globus sensation; distinct from dysphagia; food passes normally but the feeling of a lump persists
- Heartburn, chest pain, indigestion, or stomach acid coming up — present in only 40% of LPR patients; its absence does NOT rule out LPR
Laryngoscopy Findings (Reflux Finding Score)
The Reflux Finding Score (RFS), also developed by Belafsky et al., uses laryngoscopic findings to grade LPR severity. An RFS above 7 is considered abnormal. Key findings:
- Subglottic edema (pseudosulcus vocalis): A thick band of edema extending below the true vocal cords — suggestive of LPR: in a 2002 study it was seen in 70% of patients with pH-confirmed LPR and in 30% of people without it (sensitivity 70%, specificity 77%)
- Posterior commissure hypertrophy: Cobblestone thickening of the posterior laryngeal wall from chronic mucosal inflammation
- Erythema and hyperemia: Redness of the arytenoid cartilage region, posterior commissure, and vocal folds from chemical irritation
- Vocal fold edema: Swelling of the true vocal cords that causes voice changes
- Diffuse laryngeal edema: In severe or longstanding LPR, the entire supraglottic larynx may appear edematous
- Ventricular obliteration: Blurring of the laryngeal ventricles (spaces between true and false vocal cords) from edema
- Contact granuloma: Benign inflammatory mass at the arytenoid vocal process; a classic LPR complication; may require surgical excision in refractory cases
- Thick endolaryngeal mucus: Sticky mucus coating laryngeal surfaces
Diagnosis
LPR diagnosis relies on a combination of symptom assessment, laryngoscopy, and selected testing:
Clinical assessment: RSI score >13 combined with RFS >7 on laryngoscopy has good diagnostic sensitivity in patients with typical presentations. Many ENT specialists begin empirical treatment based on clinical findings alone.
24-hour ambulatory pH monitoring: The traditional gold standard. A dual-probe pH catheter measures acid exposure at the esophagus and pharynx simultaneously. The DeMeester score quantifies esophageal acid burden. Limitations: a normal study does not exclude LPR because pepsin and bile (non-acid components) can damage the larynx without lowering pH.
Multichannel intraluminal impedance-pH (MII-pH) monitoring: Superior to pH alone; detects acid, weakly acidic, and non-acid reflux events as well as gas reflux. This is the most sensitive test for LPR, especially in patients on proton pump inhibitor (PPI) therapy.
Flexible laryngoscopy: Allows direct visualization of LPR signs. RFS scoring provides an objective baseline and allows treatment monitoring.
Empirical proton pump inhibitor trial: In uncomplicated presentations with RSI >13, many clinicians give a twice-daily proton pump inhibitor trial for 8–12 weeks and assess symptomatic response. This approach is cost-effective, but in clinical practice it does not take the place of laryngoscopy for people with persistent hoarseness, suspected malignancy, or risk factors for laryngeal cancer.
Salivary pepsin assay: A point-of-care lateral flow test detecting pepsin in saliva. Increasingly used in clinical practice, particularly in the UK. A 2026 meta-analysis of 11 studies (928 samples) found a sensitivity of 33–63% with a single saliva sample at the 16 ng/mL cut-off, rising to 82% when several samples were collected, and noted the test's limited negative predictive value: a negative result does not rule LPR out. A positive result with compatible symptoms supports LPR diagnosis.
Dietary and Lifestyle Changes
Behavioral modification is the cornerstone of LPR treatment — often as effective as proton pump inhibitors (PPIs) in mild-moderate cases, with no side effects:
Diet (what LPR diets commonly describe):
- Foods and drinks restricted or strictly limited: alcohol, caffeine (coffee, tea, energy drinks), carbonated beverages, citrus fruits and juices, tomato products, chocolate, mint/peppermint, fatty and fried foods, spicy foods
- Smaller meals — a distended stomach increases reflux risk
- Eating slowly and chewing thoroughly
- A gap of 3 hours between the last meal and bedtime
- Staying upright for at least 30–60 minutes after meals
Lifestyle:
- Head of the bed raised 6–8 inches (with a wedge pillow or a raised headboard; extra pillows are described as not working and as worsening neck alignment)
- Weight loss: Even 10% body weight reduction significantly reduces LPR symptoms
- Loose clothing around the waist and abdomen (tight clothing compresses the abdomen)
- Quitting smoking: Nicotine relaxes the LES and dramatically reduces saliva production
- Hydration: Adequate water intake keeps throat membranes moist and helps wash pepsin off mucosal surfaces
- Voice hygiene: Throat clearing traumatizes the vocal cords and paradoxically worsens mucus production; sipping water is the substitute commonly described
The alkaline water debate: Some clinicians recommend alkaline water (pH 8.8) because it denatures pepsin irreversibly in vitro. Clinical evidence is limited, but alkaline water is harmless and may provide modest benefit.
Medications (Proton Pump Inhibitors and Beyond)
Proton pump inhibitors:
Proton pump inhibitors are the standard pharmacological treatment for LPR. Key points:
- LPR requires higher doses than gastroesophageal reflux disease: twice-daily dosing (30 minutes before breakfast AND 30 minutes before dinner) is the regimen commonly used — not once daily
- Duration: commonly given for at least 8–12 weeks before response is judged; the larynx heals slowly
- Common proton pump inhibitors: omeprazole, esomeprazole, pantoprazole, lansoprazole, rabeprazole
- Response rates: approximately 60–70% with strict proton pump inhibitor therapy plus lifestyle changes; lower without lifestyle modification
- Placebo-controlled trials differ: in a 2008 trial of 62 patients, esomeprazole 20 mg twice daily for three months improved symptom and laryngoscopy scores more than placebo, while in a 2006 multicenter trial of patients with suspected reflux laryngitis, esomeprazole 40 mg twice daily for 16 weeks was no better than placebo (the main symptom resolved in 14.7% vs 16.0%)
- Long-term risks: Chronic proton pump inhibitor use is associated with hypomagnesemia, vitamin B12 malabsorption, increased risk of Clostridioides difficile colitis, potential kidney effects, and possible fracture risk. The usual practice described is stepping down to the lowest effective dose, or to dietary management, when possible.
H2 receptor antagonists (H2RAs):
Ranitidine has been withdrawn; famotidine is the preferred H2RA. Less potent than proton pump inhibitors but may help nocturnal acid breakthrough when added to proton pump inhibitor therapy at bedtime.
Alginate-based agents:
A sodium alginate raft-forming liquid forms a physical raft on top of the gastric contents, blocking reflux mechanically. It is described as an option for pepsin-mediated LPR and for people who cannot tolerate proton pump inhibitors. The trial evidence is limited: a 2009 open-label UK pilot study randomized 49 patients to the liquid four times daily or to no treatment, found lower symptom scores at 2 and 6 months and lower laryngoscopy scores at 6 months with the alginate, and concluded that further evaluation is warranted.
Prokinetics:
Metoclopramide or domperidone increase LES pressure and accelerate gastric emptying, reducing reflux volume. Used as adjuncts in refractory cases. Metoclopramide carries an FDA boxed warning: it can cause tardive dyskinesia, a potentially irreversible serious movement disorder; the risk rises with the length of treatment and the total dose; and for documented gastroesophageal reflux the label sets a maximum treatment length of 12 weeks. Domperidone is not a legally marketed drug in the U.S. and is not approved for sale there; the FDA lists its serious risks as heart rhythm disturbances (cardiac arrhythmias), cardiac arrest, and sudden death.
Voice therapy:
Counterintuitively, voice therapy with a speech-language pathologist is often used for LPR patients with significant dysphonia. Techniques to reduce effortful vocal behavior, eliminate throat clearing habits, and optimize vocal hygiene complement medical therapy.
When Surgery Is Needed
Surgical fundoplication is reserved for carefully selected patients who:
- Have documented reflux on objective testing (pH or MII-pH study)
- Demonstrate LPR symptoms consistent with the reflux events on the pH study
- Have failed adequate medical therapy (proper dose, proper duration, lifestyle compliance)
- Are not candidates for or refuse indefinite proton pump inhibitor therapy
Laparoscopic Nissen fundoplication: The LES is reinforced by wrapping the gastric fundus completely around the lower esophagus. Success rate for eliminating reflux exceeds 90% in properly selected patients. However, LPR symptoms (vs classic gastroesophageal reflux disease) may have a lower surgical success rate, possibly because some "LPR" presentations involve extra-esophageal hypersensitivity rather than true reflux.
Laparoscopic Toupet fundoplication: A partial (270°) wrap; lower risk of post-operative dysphagia compared to Nissen, with similar reflux control.
Magnetic sphincter augmentation device: A ring of magnetic beads implanted around the LES to augment sphincter pressure; U.S. Food and Drug Administration-approved; reversible; growing evidence for gastroesophageal reflux disease, more limited data for LPR specifically.
Voice therapy and diet changes usually continue even after successful surgery.
Key Research Papers
- Belafsky PC et al. "Validity and reliability of the reflux symptom index (RSI)." J Voice. 2002 Jun;16(2):274-7. — PubMed PMID: 12150380
- Belafsky PC et al. "The validity and reliability of the reflux finding score (RFS)." Laryngoscope. 2001 Aug;111(8):1313-7. — PubMed PMID: 11568561
- Belafsky PC et al. "The association between laryngeal pseudosulcus and laryngopharyngeal reflux." Otolaryngol Head Neck Surg. 2002 Jun;126(6):649-52. — PubMed PMID: 12087332
- Koufman JA. "The otolaryngologic manifestations of gastroesophageal reflux disease (GERD): a clinical investigation of 225 patients using ambulatory 24-hour pH monitoring and an experimental investigation of the role of acid and pepsin in the development of laryngeal injury." Laryngoscope. 1991 Apr;101(4 Pt 2 Suppl 53):1-78. — PubMed PMID: 1895864
- Johnston N et al. "Activity/stability of human pepsin: implications for reflux attributed laryngeal disease." Laryngoscope. 2007 Jun;117(6):1036-9. — PubMed PMID: 17417109
- Martinucci I et al. "Optimal treatment of laryngopharyngeal reflux disease." Ther Adv Chronic Dis. 2013 Nov;4(6):287-301. — PubMed PMID: 24179671
- Reichel O et al. "Double-blind, placebo-controlled trial with esomeprazole for symptoms and signs associated with laryngopharyngeal reflux." Otolaryngol Head Neck Surg. 2008 Aug;139(3):414-20. — PubMed PMID: 18722223
- Vaezi MF et al. "Treatment of chronic posterior laryngitis with esomeprazole." Laryngoscope. 2006 Feb;116(2):254-60. — PubMed PMID: 16467715
- Roman S et al. "Ambulatory reflux monitoring for diagnosis of gastro-esophageal reflux disease: Update of the Porto consensus and recommendations from an international consensus group." Neurogastroenterol Motil. 2017 Oct;29(10):1-15. — PubMed PMID: 28370768