Syphilis Diagnosis: RPR, VDRL, FTA-ABS, and TPPA
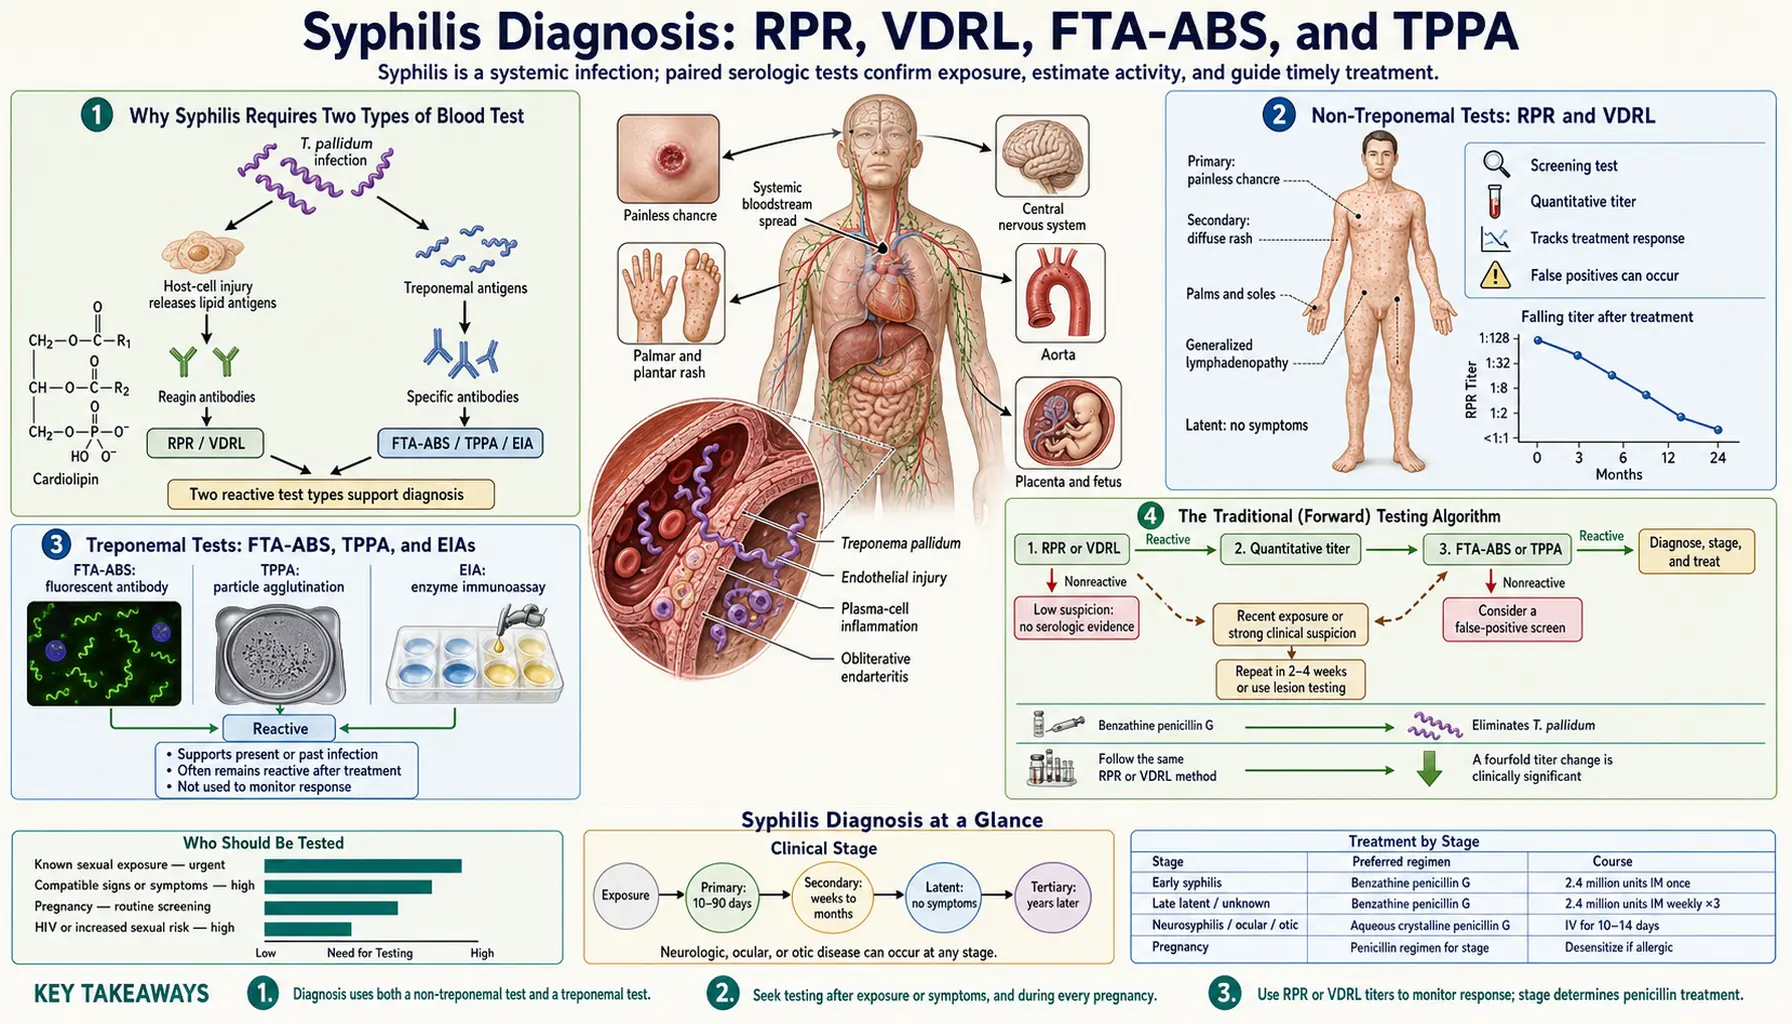
Syphilis cannot be diagnosed from symptoms alone — too many conditions look similar. Diagnosis depends on blood tests, and the testing system is a two-step process using two entirely different types of antibody. Understanding what each test measures, why both are needed, and what the results actually mean helps you make sense of your lab report and have an informed conversation with your doctor.
Table of Contents
- Why Syphilis Requires Two Types of Blood Test
- Non-Treponemal Tests: RPR and VDRL
- Treponemal Tests: FTA-ABS, TPPA, and EIAs
- The Traditional (Forward) Testing Algorithm
- The Reverse Sequence Screening Algorithm
- The Prozone Phenomenon: When a Positive Looks Negative
- Dark-Field Microscopy for Active Chancres
- Cerebrospinal Fluid Analysis for Neurosyphilis
- False Positives and Their Causes
- Rapid Point-of-Care Tests
- Key Research Papers
- Featured Videos
1. Why Syphilis Requires Two Types of Blood Test
For more than a century Treponema pallidum could not be kept growing in the laboratory — it was one of the few major bacterial pathogens that had not been cultured long-term in a test tube. In 2018 a research team in Houston (Edmondson, Hu and Norris) finally achieved long-term growth, using a special medium (TpCM-2) together with rabbit skin cells, transferring the cultures every 6 to 7 days; the bacteria kept multiplying for more than 6 months and stayed fully viable. This is a research method, not a diagnostic test, so the workhorse of infectious disease diagnosis (isolating the organism from a patient and confirming it) is still not used for syphilis. All diagnosis depends on detecting the immune response to the infection.
The immune response to syphilis generates two distinct types of antibodies, each detected by a different class of test:
- Non-treponemal antibodies are not actually directed at the spirochete itself. They are directed at cardiolipin, a lipid released from damaged cells (both syphilitic lesions and inflamed host cells) during infection. These antibodies fluctuate with disease activity and decrease after treatment — making them ideal for monitoring treatment response. But because cardiolipin damage occurs in other conditions too, these tests generate false positives.
- Treponemal antibodies are directed specifically at T. pallidum proteins. They are highly specific for true syphilis infection but remain positive for life even after successful treatment. So they cannot monitor treatment response, but they confirm true infection.
The two-test algorithm combines these strengths: a non-treponemal test (RPR or VDRL) screens and monitors; a treponemal test (FTA-ABS, TPPA, or EIA) confirms.
2. Non-Treponemal Tests: RPR and VDRL
The two non-treponemal tests in common use are the RPR (Rapid Plasma Reagin) and the VDRL (Venereal Disease Research Laboratory) test. Both detect antibodies to a cardiolipin-cholesterol-lecithin antigen. The tests differ slightly in methodology (RPR uses a carbon particle antigen visible to the naked eye; VDRL is read under a microscope) but are clinically equivalent.
Key features of RPR/VDRL:
- Quantitative: Results are reported as a titer — a dilution factor indicating the concentration of antibody. Common titers: 1:1, 1:2, 1:4, 1:8, 1:16, 1:32, 1:64, 1:128. High titers (1:32 or above) indicate active, untreated infection. Very high titers sometimes indicate secondary syphilis.
- Monitors treatment response: A successful treatment response is defined as a fourfold (two-dilution) drop in titer within 6 to 12 months. For example, a titer falling from 1:32 to 1:8 confirms adequate therapy. The CDC's 2021 guidelines state that failure to fall fourfold within 12 months after treatment of primary or secondary syphilis might indicate treatment failure — but that 10% to 20% of people treated with the recommended therapy do not reach the fourfold drop within 12 months. Titers below 1:8 are less likely to fall fourfold than higher titers, and titers in older patients might be less likely to fall as well.
- Sensitive but not specific: Both tests are highly sensitive for secondary and early latent syphilis (close to 100%). Sensitivity is lower for primary syphilis (approximately 70–85%) in the very early days after chancre appearance, and lower for late latent and tertiary syphilis (70–80%).
- False positives: Occur in autoimmune diseases, pregnancy, other infections (human immunodeficiency virus (HIV), malaria, tuberculosis, Epstein-Barr virus (EBV)), intravenous drug use, and aging. This is why a positive RPR always requires treponemal confirmation.
3. Treponemal Tests: FTA-ABS, TPPA, and EIAs
The confirmatory treponemal tests detect antibodies specifically targeting proteins of T. pallidum. Several tests are available:
FTA-ABS (Fluorescent Treponemal Antibody Absorbed): The historical gold standard. The patient's serum is first "absorbed" with non-pathogenic treponemal antigens to remove cross-reactive antibodies, then applied to a slide containing fixed T. pallidum organisms, followed by a fluorescent-labeled anti-human antibody. A positive result shows fluorescent spirochetes under the microscope. Labor-intensive and requires fluorescence microscopy.
TPPA (T. pallidum Particle Agglutination) and TP-PA: A simpler agglutination test in which gelatin particles coated with treponemal antigens visibly clump in the presence of positive serum. Easier to perform than FTA-ABS and widely used.
Treponemal EIAs (enzyme immunoassays) and chemiluminescence immunoassays (CIAs): Automated platforms that have largely replaced FTA-ABS and TPPA in high-volume laboratories because they can process hundreds of samples per hour. These are now the most common treponemal tests in US clinical labs and are the basis of the reverse sequence algorithm.
Key features of all treponemal tests:
- Remain positive for life. Once a person has been infected with syphilis and tests positive on a treponemal test, this test remains positive indefinitely — even decades after successful treatment and cure. This is the most important limitation: treponemal tests cannot distinguish past treated infection from current active infection.
- Qualitative results only. Unlike RPR/VDRL, treponemal tests report positive or negative, not a titer. They cannot be used to monitor treatment.
- High sensitivity and specificity. True false positives are rare but occur in Lyme disease, some autoimmune conditions, and occasionally other spirochetal infections.
4. The Traditional (Forward) Testing Algorithm
The traditional (and still widely used) approach to syphilis testing is:
- Screen with non-treponemal test (RPR or VDRL)
- If positive, confirm with treponemal test (FTA-ABS, TPPA, or EIA)
- If both positive, diagnose syphilis and determine stage from clinical history
- If non-treponemal positive but treponemal negative, consider biological false positive; no treatment indicated
This algorithm works well in most settings. Its main limitation is slightly lower sensitivity for very early primary syphilis, when RPR can be negative in the first one to two weeks after chancre appearance (antibodies have not yet developed to detectable levels). In a person with a classic chancre and a negative RPR, the blood test may simply have been taken too early: the CDC's 2024 laboratory recommendations note that people with very recently appearing lesions are more likely to be positive by dark-field microscopy and still seronegative, and that molecular tests (NAATs) on the lesion might give a more timely diagnosis of primary syphilis than blood tests.
5. The Reverse Sequence Screening Algorithm
High-volume laboratories increasingly use a reversed algorithm:
- Screen with automated treponemal EIA or CIA (high throughput, no technician interpretation needed)
- If treponemal EIA positive, test with non-treponemal RPR or VDRL
- Interpret results: if both positive → current syphilis; if treponemal positive + non-treponemal negative → ambiguous (past treated syphilis vs. false-positive treponemal vs. very early primary)
- For treponemal+/non-treponemal- cases: add second treponemal test (TP-PA) for resolution
This algorithm is more sensitive for very early primary syphilis (treponemal tests can be positive before RPR becomes positive). But it generates more cases of diagnostic uncertainty: a person treated for syphilis 10 years ago has a positive treponemal EIA and a negative RPR, which can confuse both clinicians and patients. The second treponemal test (TP-PA) helps confirm true seropositivity, but clinical history remains essential.
In February 2024 the CDC published its first-ever laboratory recommendations for syphilis testing (Papp and colleagues, MMWR Recommendations and Reports). They state that non-treponemal and treponemal tests must be used together to help tell an untreated infection from a past infection that was successfully treated, and that the newer automated treponemal tests must be used within a testing algorithm, which can also include the older manual tests.
6. The Prozone Phenomenon: When a Positive Looks Negative
The prozone phenomenon is an important diagnostic pitfall in syphilis testing. In secondary syphilis, antibody concentrations can be so high that the non-treponemal test is paradoxically reported as negative at the standard test dilution — because an excess of antibody saturates the antigen and prevents agglutination.
Think of it like trying to make a handshake happen in a crowd: if there are too many people trying to shake hands at once, no hands actually connect. The antibody is present and real, but the assay reads negative.
The prozone phenomenon comes into question when a patient has classic secondary syphilis symptoms (the rash, palms and soles involvement) and a negative RPR. The CDC's 2024 laboratory recommendations state that a prozone can be avoided if the serum sample is diluted before testing, and that prozone false negatives have been reported for non-treponemal tests but not for agglutination-based treponemal tests — so a treponemal test is the other route. At higher dilutions, the antibody excess resolves and the test becomes positive. The prozone effect has been reported in up to 2% of secondary syphilis cases; in two large studies of specimens referred for syphilis testing cited by the CDC, false-negative RPRs caused by a prozone were rare (under 0.85%).
7. Dark-Field Microscopy for Active Chancres
When a primary chancre or secondary-stage lesion is present, dark-field microscopy of material collected directly from the lesion can confirm the diagnosis immediately, without waiting for blood tests to become positive.
The procedure: a small amount of fluid from the base of the chancre (or from a condyloma lata) is placed on a glass slide and examined under a dark-field microscope. This specialized microscope illuminates the specimen from the side, making the thin, moving spirochetes visible against a dark background as bright, corkscrew-shaped organisms with characteristic motility (a gentle bending and rotating motion).
Dark-field microscopy and molecular tests such as PCR are the direct-detection methods: they find the organism itself rather than waiting for antibodies to develop. The CDC's 2021 guidelines call dark-field examination and molecular tests on lesion fluid or tissue the definitive methods for diagnosing early syphilis and congenital syphilis, and the CDC's 2024 laboratory recommendations describe direct detection moving from the microscope toward molecular detection. Direct detection is valuable in the very early days of primary syphilis when RPR may still be negative. However, it requires a skilled microscopist, immediate examination (spirochetes die quickly on the slide), and has largely been replaced by polymerase chain reaction (PCR) in modern laboratories.
Important exception: The CDC's 2024 laboratory recommendations do not recommend dark-field microscopy on oral lesions, because the mouth contains harmless (commensal) treponemes that are easily confused with T. pallidum under the microscope, leading to false-positive results. For moist lesions, including mouth lesions (mucous patches), the same recommendations allow laboratory-developed molecular tests (NAATs such as polymerase chain reaction) in patients whose blood tests are still negative.
8. Cerebrospinal Fluid Analysis for Neurosyphilis
Lumbar puncture (spinal tap) to analyze cerebrospinal fluid is needed when neurosyphilis is suspected. The CSF-VDRL is the specific syphilis test performed on cerebrospinal fluid (CSF):
- Sensitivity: Low (~30–70%). A negative CSF-VDRL does not exclude neurosyphilis.
- Specificity: Very high. When positive, it is near-diagnostic for neurosyphilis (contamination with blood from a traumatic tap is a rare confound).
- Supporting findings: cerebrospinal fluid protein elevation (>45 mg/dL) and pleocytosis (>5 white blood cells/μL) indicate meningeal inflammation consistent with neurosyphilis.
- CSF-FTA-ABS: More sensitive than CSF-VDRL but less specific; a negative result can help rule out neurosyphilis.
The CDC's 2021 treatment guidelines describe when cerebrospinal fluid is examined:
- Signs of neurosyphilis: CSF evaluation is warranted for people with clinical signs of neurosyphilis, such as cranial nerve dysfunction, meningitis, stroke, acute or chronic altered mental status, or loss of vibration sense.
- Tertiary syphilis: everyone with tertiary syphilis receives a CSF examination before treatment begins.
- Possible treatment failure: a CSF examination is recommended for people with neurologic findings, or with no reported sexual exposure in the previous 3 to 6 months, when treatment failure might be possible.
- Eye symptoms only: everyone with eye symptoms and a reactive syphilis test gets a full eye examination including the cranial nerves. With isolated eye symptoms (no cranial nerve or other neurologic abnormality) and eye findings confirmed on examination, a CSF examination is unnecessary before treatment.
- Hearing symptoms only: with isolated hearing symptoms and a normal neurologic examination, CSF examination is likely to be normal and is not recommended before treatment.
- Human immunodeficiency virus and latent syphilis: everyone in this group gets a thorough neurologic, eye and ear examination; those with neurologic symptoms or signs undergo immediate CSF examination. Without such symptoms or signs, CSF examination has not been linked to better outcomes and is not recommended.
9. False Positives and Their Causes
A positive non-treponemal test (RPR or VDRL) that is not confirmed by a treponemal test is called a biological false positive (BFP). BFPs occur because the cardiolipin antigen used in these tests is a normal cell membrane component released by damaged or inflamed cells of any kind, not only those damaged by syphilis. Common causes of BFPs include:
- Pregnancy: Low-titer BFPs occur, though the CDC's 2024 laboratory recommendations put false positives among pregnant people at 0.6%; they state that every initially reactive non-treponemal test is followed by a confirmatory treponemal test
- Autoimmune diseases: Particularly systemic lupus erythematosus (SLE) and antiphospholipid syndrome; the antiphospholipid antibodies cross-react with cardiolipin
- Other infections: human immunodeficiency virus, tuberculosis, malaria, Epstein-Barr virus (mononucleosis), mycoplasma pneumonia
- Intravenous drug use: Mechanism unclear, possibly chronic immune activation
- Advanced age: Low-titer BFPs become more common after age 70
- Recent immunization: Short-lived BFPs after some vaccines
The titer is a useful guide: true syphilis infection typically generates titers of 1:8 or higher during active infection. A BFP is usually at a low titer (1:1 to 1:4). However, this is a rule of thumb, not an absolute — lupus can generate high titers, and primary syphilis may have low titers early. Treponemal confirmation is always required.
10. Rapid Point-of-Care Tests
Point-of-care (POC) rapid syphilis tests are approved by the WHO and used globally, particularly in low-resource settings and antenatal clinics where laboratory infrastructure is limited. They require only a finger-stick blood sample and return a result in 15 to 20 minutes without laboratory equipment.
Rapid tests detect treponemal antibodies (making them specific for T. pallidum and resistant to the common causes of BFP). Their key characteristics:
- Sensitivity: Comparable to laboratory treponemal EIA in most studies (>85%). A 2013 meta-analysis of 33 studies (Jafari and colleagues) found serum sensitivities of about 74% to 90% for four widely used rapid tests, with specificities of about 94% to 99%, and judged them comparable to laboratory-based treponemal tests.
- Specificity: High (>95% in most evaluations).
- Results positive for life: Like all treponemal tests, they remain positive after successful treatment. They cannot determine whether infection is current or past.
- Value in pregnancy: The ability to test and treat a pregnant woman in a single visit dramatically reduces congenital syphilis when used in antenatal care settings.
Dual rapid tests (detecting both syphilis and human immunodeficiency virus from a single finger-stick) are now available and are being deployed in high-burden settings.
In August 2024 the U.S. Food and Drug Administration authorized the first at-home, over-the-counter syphilis antibody test, a finger-stick blood test that gives a result in about 15 minutes without a prescription. The FDA states that a result from this type of test alone is not enough to diagnose syphilis and is followed by laboratory testing to confirm it, and that the test is positive in people who had syphilis before, even after successful treatment. The FDA cites CDC data that reported U.S. syphilis cases rose 80% between 2018 and 2022 (from 115,000 to more than 207,000).
Key Research Papers
- Workowski KA, Bachmann LH, Chan PA, et al. Sexually transmitted infections treatment guidelines, 2021. MMWR Recomm Rep. 2021;70(4):1–187. — PubMed PMID: 34292926
- Ratnam S. The laboratory diagnosis of syphilis. Can J Infect Dis Med Microbiol. 2005;16(1):45–51. — PubMed PMID: 18159528
- Binnicker MJ, Jespersen DJ, Rollins LO. Treponema-specific tests for serodiagnosis of syphilis: comparative evaluation of seven assays. J Clin Microbiol. 2011;49(4):1313–1317. — PubMed PMID: 21346050
- Marra CM, Maxwell CL, Smith SL, et al. Cerebrospinal fluid abnormalities in patients with syphilis: association with clinical and laboratory features. J Infect Dis. 2004;189(3):369–376. — PubMed PMID: 14745693
- Jafari Y, Peeling RW, Shivkumar S, Claessens C, Joseph L, Pai NP. Are Treponema pallidum specific rapid and point-of-care tests for syphilis accurate enough for screening in resource limited settings? Evidence from a meta-analysis. PLoS One. 2013;8(2):e54695. — PubMed PMID: 23468842
- Peeling RW, Mabey D. Point-of-care tests for diagnosing infections in the developing world. Clin Microbiol Infect. 2010;16(8):1062–1069. — PubMed PMID: 20670288
- Park IU, Chow JM, Bolan G, Stanley M, Shieh J, Schapiro JM. Screening for syphilis with the treponemal immunoassay: analysis of discordant serology results and implications for clinical management. J Infect Dis. 2011;204(9):1297–1304. — PubMed PMID: 21930610
- Mishra S, Walmsley SL, Loutfy MR, et al. Otosyphilis in HIV-coinfected individuals: a case series from Toronto, Canada. AIDS Patient Care STDS. 2008;22(3):213–219. — PubMed PMID: 18290755
- Larsen SA, Steiner BM, Rudolph AH. Laboratory diagnosis and interpretation of tests for syphilis. Clin Microbiol Rev. 1995;8(1):1–21. — PubMed PMID: 7704889
- Golden MR, Marra CM, Holmes KK. Update on syphilis: resurgence of an old problem. JAMA. 2003;290(11):1510–1514. — PubMed PMID: 13129993
- Edmondson DG, Hu B, Norris SJ. Long-Term In Vitro Culture of the Syphilis Spirochete Treponema pallidum subsp. pallidum. mBio. 2018;9(3):e01153-18. — PubMed PMID: 29946052
- Papp JR, Park IU, Fakile Y, Pereira L, Pillay A, Bolan GA. CDC Laboratory Recommendations for Syphilis Testing, United States, 2024. MMWR Recomm Rep. 2024;73(1):1–32. — PubMed PMID: 38319847
Connections
- All Bacteria
- Treponema pallidum (Syphilis) Hub
- Syphilis Symptoms & Stages Overview
- Primary & Secondary Syphilis
- Neurosyphilis & Tertiary Syphilis
- Syphilis Treatment & Prevention
- Penicillin G Treatment
- Lab Tests
- All Conditions
- Syphilis — overview of the infection these blood tests detect.
- Congenital Syphilis
- Syphilis Resurgence