Thiamine (Vitamin B1) Toxicity: What the Evidence Shows
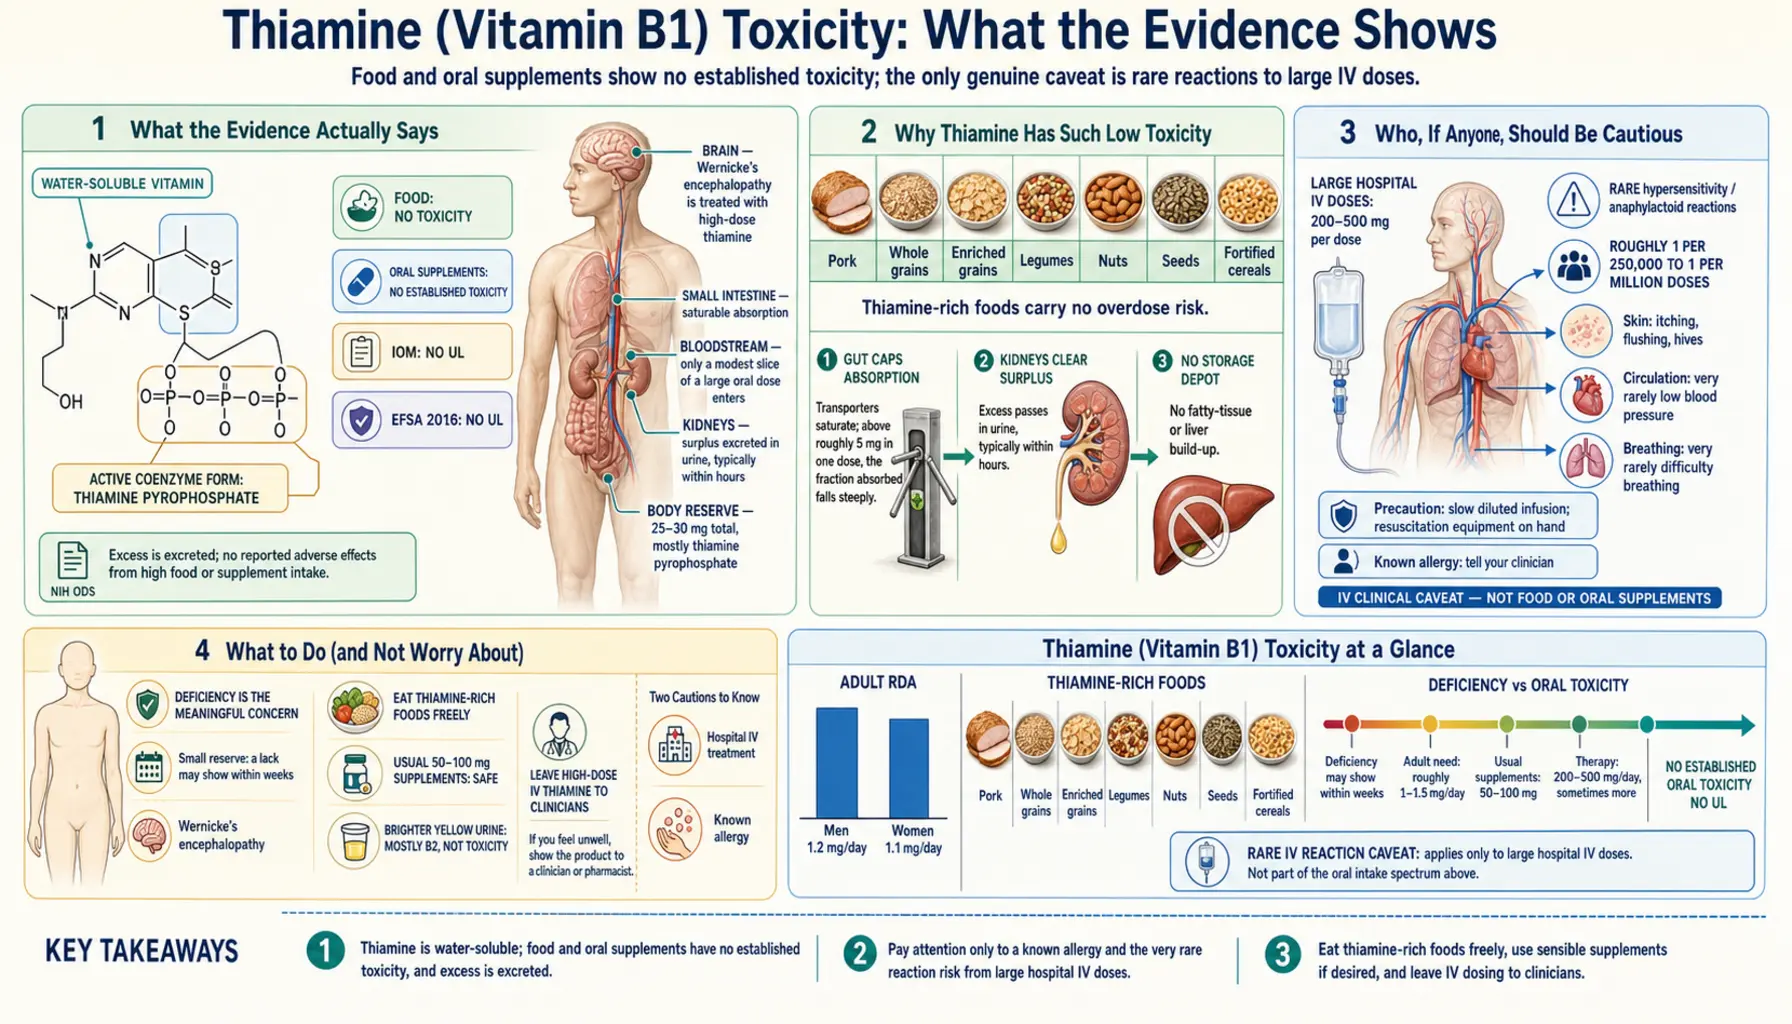
Here is the honest bottom line, stated up front: thiamine (vitamin B1) is not toxic from food, and it is essentially not toxic from oral supplements either. It is a water-soluble vitamin, which means your body does not stockpile a dangerous surplus — whatever you absorb beyond your needs, the kidneys simply filter out and pass in the urine. Because of this, no recognized "thiamine toxicity syndrome" exists, and the two bodies that set nutrient safety limits — the U.S. Institute of Medicine and the European Food Safety Authority — have not established a Tolerable Upper Intake Level for thiamine, specifically because the evidence for harm from high oral intake is too thin to support one. People have taken hundreds of milligrams a day — far above the roughly 1–1.5 mg an adult needs — in clinical trials without meaningful ill effects. The only genuine caveat is a narrow clinical one: rare hypersensitivity or anaphylactoid reactions to large intravenous doses given in a hospital, which is a procedural issue for clinicians, not something that happens from eating pork, whole grains, or taking a B-complex pill. This page explains what the evidence actually says, why thiamine behaves this way in the body, the few edge cases worth knowing, and a low-key, practical takeaway. This is not a common clinical problem, and the page is deliberately short because there is not a toxicity to describe.
Table of Contents
What the Evidence Actually Says
It is worth being clear and direct, because health writing often hedges where it does not need to: there is no established toxicity from oral thiamine, and none at all from thiamine in food. This is not an oversight or a gap waiting to be filled — it reflects decades of use and study. Thiamine is one of the safest vitamins known.
The clearest sign of this is what the expert bodies decided not to do. When scientists set nutrient guidelines, they publish two kinds of numbers: how much you need (the Recommended Dietary Allowance (RDA) or recommended intake) and, where the evidence justifies it, a ceiling above which harm becomes likely — the Tolerable Upper Intake Level (UL). For thiamine:
- The U.S. Institute of Medicine (IOM, now the National Academies) set a Recommended Dietary Allowance of about 1.2 mg/day for adult men and 1.1 mg/day for adult women, but pointedly did not set a Tolerable Upper Intake Level. Its reasoning was straightforward: there were no well-documented reports of harm from high oral thiamine intake on which to base a limit.
- The European Food Safety Authority (EFSA), in its 2016 review of dietary reference values for thiamin, likewise did not establish a Tolerable Upper Intake Level, concluding that the available data did not show adverse effects from high oral intakes.
- The U.S. National Institutes of Health (NIH) Office of Dietary Supplements (ODS) states plainly in its thiamin fact sheet that the body excretes excess thiamine in the urine and that there are no reports of adverse effects from consuming high amounts from food or supplements.
To put the numbers in perspective: an adult needs on the order of 1 to 1.5 mg of thiamine a day. Yet many B-complex and "stress" supplements contain 50 mg, 100 mg, or more — doses 50 to 100 times the requirement — and these are sold over the counter. The Institute of Medicine noted that supplements with up to 50 mg a day are widely available without prescription, but that possible adverse effects at this level or more appear not to have been studied systematically. In medicine, thiamine is given in still larger amounts: 200 to 500 mg a day, and sometimes more, is used to treat or prevent Wernicke's encephalopathy and has been tested in critical-care trials, generally without significant toxicity. One short 2018 opinion article by Italian neurologists who treat Parkinson’s disease with high-dose thiamine did describe overdose symptoms — a general feeling of discomfort, restlessness, a worsening of the original symptoms and, in some, a moderate migraine. They estimated these affected about 1% of their patients on 200–300 mg of thiamine a week (or the corresponding oral doses), and most of a later group of patients of Anglo-Saxon and African origin; the symptoms faded after the thiamine was paused and restarted at half the dose. Apart from that report, the picture across food, supplements, and high-dose therapy is consistent: no harmful build-up from thiamine taken by mouth has been documented.
This is the opposite of the situation with the fat-soluble vitamins (A, D, E, and K), which the body stores in fat and the liver and which therefore can accumulate to toxic levels — vitamin A and vitamin D in particular have well-defined toxicity syndromes and firm upper limits. Thiamine, being water-soluble, behaves nothing like that. If you have arrived at this page worried that a supplement or a thiamine-rich diet might "overdose" you, the honest answer is that this is not a realistic concern.
Why Thiamine Has Such Low Toxicity
The reason thiamine is so hard to overdose comes down to two pieces of basic biology: how small a share of a large dose the body absorbs at once, and how efficiently the kidneys clear the rest. Together these act like a pressure-release valve that prevents a dangerous build-up.
Absorption becomes less efficient at high doses. In the small intestine, thiamine is taken up by specific transporter proteins at ordinary dietary amounts and by passive diffusion at higher amounts, and the Institute of Medicine notes that only a small percentage of a high dose is absorbed. The transporters have a maximum throughput, so when a large dose arrives all at once the fraction absorbed falls; above roughly 5 mg in a single dose it falls off steeply, and much of the excess passes through. The gut does not cap the dose, though: in a 2012 study of healthy volunteers given single oral doses of 100, 500 and 1,500 mg, blood thiamine levels kept rising with each larger dose (less than in proportion), and the authors concluded that thiamine is absorbed by both an active and a non-saturable passive process. (Some high-potency products use synthetic thiamine derivatives such as benfotiamine, which a 2008 study found strongly raises thiamine levels in the blood; that study also found it is not truly fat-soluble but is absorbed after the gut removes its phosphate group. Even then, the surplus is still excreted.)
Think of it like a stadium entrance with a turnstile and a narrow side door: the turnstile lets people through at a steady pace, and the side door lets a slower trickle through when the crowd is large. A bigger crowd gets more people in, but a smaller share of the crowd.
The kidneys clear the surplus. Whatever thiamine does get into the blood beyond what the body can immediately use or hold in its small functional pool is filtered by the kidneys and excreted in the urine, typically within hours. The body keeps only a small working reserve (on the order of 25–30 mg total, mostly in the form thiamine pyrophosphate, the active coenzyme), and it does not pad that reserve with a hazardous excess. There is no fatty tissue or liver depot quietly accumulating thiamine the way there is for vitamins A or D.
This combination — a gut that absorbs a shrinking share of a large dose and kidneys that promptly flush what does get through — is exactly why the safety authorities could find no basis for an upper limit. The biology makes oral overdose self-correcting. (The flip side, covered on the Deficiency hub, is that because the body holds so little thiamine in reserve, a lack of it shows up within weeks — thiamine's water-solubility cuts both ways.)
Who, If Anyone, the Research Raises Concerns For
If oral thiamine is essentially non-toxic, is there any real caveat? Yes — but it is narrow, clinical, and almost entirely about the intravenous (IV) route given in a hospital, not about diet or pills. It is worth understanding precisely so it is not over-interpreted.
- Rare hypersensitivity / anaphylactoid reactions to large intravenous doses. This is the one genuine, documented risk. When thiamine is injected directly into a vein — as is done to treat Wernicke's encephalopathy in hospital, often at 200–500 mg per dose — a small number of people have had allergic-type reactions, ranging from itching, flushing, or hives up to, very rarely, a severe anaphylactoid reaction with low blood pressure and difficulty breathing. The Institute of Medicine also notes occasional reports of serious and even fatal reactions to injected thiamine, with shock sometimes progressing to death. Crucially, the most rigorous review of this question (Thomson, Guerrini & Marshall, Alcohol and Alcoholism, 2019, PubMed 31565743) found these reactions to be very uncommon. Its actual figure is worth quoting precisely rather than converting into a tidy per-dose rate: 10 anaphylactic reactions across roughly 5.4–6.7 million patient-days of treatment with a UK high-dose injectable B-vitamin product — about 14,900 to 16,100 patient-years. The authors are explicit that a true per-dose incidence could not be calculated, because the number of doses actually given is unknown and sales figures only approximate it. Their conclusion is that the risk of anaphylaxis is low, lower than for many other drugs, and that the risk–benefit balance clearly favours treating Wernicke's encephalopathy given how severe the untreated brain damage is. The practical response in medicine is sensible precaution, not avoidance: giving intravenous thiamine as a slow infusion diluted in fluid rather than a rapid push, and having resuscitation equipment on hand — standard practice for many injectable drugs. This is a clinician's procedural concern, not something that can happen from food or an oral supplement.
- People with a known allergy to thiamine or to a product's other ingredients. As with virtually any substance, a true allergy is possible, though genuine thiamine allergy is rare. Someone who has reacted to a thiamine injection or supplement before is known to be sensitive to it.
- A note on lab tests — thiamine is not the B vitamin that interferes with bloodwork. You may have heard that a B vitamin can throw off laboratory results; that is biotin (vitamin B7), not thiamine. High-dose biotin can distort certain immunoassays (for example, some thyroid and troponin tests). Thiamine does not have this effect. We mention it only to clear up a common mix-up — see Biotin (Vitamin B7).
Notably absent from this list is anything about high oral doses causing organ damage, nerve problems, or a build-up syndrome — because the evidence does not support such claims. Unlike vitamin B6 (pyridoxine), where chronically very high oral doses can cause nerve damage and therefore does have an upper limit, thiamine carries no comparable oral toxicity.
What This Means in Everyday Life
The practical guidance here is refreshingly simple, precisely because there is so little to manage.
- No overdose from food has been reported. Thiamine-rich foods — pork, whole and enriched grains, legumes, nuts, seeds, and fortified cereals — carry no known overdose risk. For where thiamine comes from, see Vitamin B1 Food Sources.
- No harm has been reported from over-the-counter B1 and B-complex supplements at usual doses. The 50–100 mg amounts common in these products are far above the requirement; the Institute of Medicine found no reports of adverse effects from thiamine in food or supplements, though it noted that 50 mg a day or more has not been studied systematically for side effects. The surplus is excreted. (As always with supplements, more is not the same as better; taking far more than you need mostly produces expensive urine, not extra benefit.)
- One harmless, expected effect: large oral doses of B vitamins, including thiamine in a B-complex, can give urine a brighter yellow tint (this is mostly riboflavin, vitamin B2) and can lend supplements a faint sulfur-like smell. Neither is a sign of toxicity — the color is simply the vitamins being excreted.
- High-dose intravenous thiamine is a hospital treatment. The therapeutic high doses used for Wernicke's encephalopathy or in critical care are given and monitored by medical professionals who manage the rare injection-reaction risk; the reported serious reactions come from injections, not from food or tablets.
- Feeling unwell after a supplement. Because thiamine itself so rarely causes problems, a symptom that appears after taking a B-complex is more often due to another ingredient (listed on the label), an unrelated cause, or coincidence. In the 2018 report of thiamine overdose symptoms during high-dose treatment, the symptoms faded after the thiamine was paused.
In short: no harm has been reported from thiamine in food or from usual supplement doses, and the documented (and small) risk belongs to the hospital intravenous setting. The water-solubility that makes thiamine deficiency develop quickly is the very same property that makes its toxicity, for all practical purposes, a non-issue.
Related Topics
Because thiamine toxicity is not a real clinical entity, the more useful reading is about thiamine's actual roles and the conditions tied to its deficiency, where the meaningful health stakes lie:
- Thiamine (Vitamin B1) Deficiency — the side of the ledger that genuinely matters: who runs low, the warning signs, and how it is corrected.
- Thiamine and Beriberi — the classic deficiency disease, wet and dry forms, and its history.
- Thiamine and Brain Health — why the brain is so dependent on thiamine and what Wernicke-Korsakoff syndrome is.
- Vitamin B1 (Thiamine) overview — the full picture of what thiamine does in the body.
Key Research Papers
- EFSA Panel on Dietetic Products, Nutrition and Allergies (NDA) (2016). Dietary reference values for thiamin. EFSA Journal;14(12):4653. — DOI: 10.2903/j.efsa.2016.4653 (The European review that explicitly did not set a Tolerable Upper Intake Level for thiamin.) — doi:10.2903/j.efsa.2016.4653
- Thomson A, Guerrini I, Marshall EJ (2019). Incidence of Adverse Reactions to Parenteral Thiamine in the Treatment of Wernicke's Encephalopathy, and Recommendations. Alcohol and Alcoholism;54(6):609-614. — DOI: 10.1093/alcalc/agy091 (Quantifies the rare IV-thiamine reaction risk and concludes the benefit far outweighs it.) — doi:10.1093/alcalc/agy091
- Donnino MW, Andersen LW, Chase M, et al. (2015). Thiamine as a metabolic resuscitator in septic shock: a randomized, double-blind, placebo-controlled, pilot trial. Critical Care;19(Suppl 1). — DOI: 10.1186/cc14472 (High-dose intravenous thiamine administered in a controlled trial without significant toxicity.) — doi:10.1186/cc14472
- Costantini A, Fancellu R (2018). Effects of Overdose of High-Dose Thiamine Treatment. Gerontology & Geriatrics Studies;4(2). — DOI: 10.31031/ggs.2018.04.000583 (An opinion article, in a journal not indexed in PubMed or MEDLINE, by neurologists who treat Parkinson’s disease with high-dose thiamine. It reports overdose symptoms — discomfort, restlessness, worsening of the original symptoms, migraine — in about 1% of their patients on 200–300 mg a week, fading after a pause and a halved dose.) — doi:10.31031/ggs.2018.04.000583
- Jackson R (2004). Oral or intravenous thiamine in the emergency department. Emergency Medicine Journal;21(4):501-502. — DOI: 10.1136/emj.2004.016550. — doi:10.1136/emj.2004.016550
- Whitfield KC, Bourassa MW, Adamolekun B, et al. (2018). Thiamine deficiency disorders: diagnosis, prevalence, and a roadmap for global control programs. Annals of the New York Academy of Sciences;1430(1):3-43. — DOI: 10.1111/nyas.13919 (Comprehensive review of thiamine biology and status; deficiency, not excess, is the clinical concern.) — doi:10.1111/nyas.13919
- Institute of Medicine (1998). Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline; Chapter 4, Thiamin. Washington, DC: National Academies Press. — DOI: 10.17226/6015 (Found no reports of adverse effects from thiamin in food or supplements and judged the data inadequate to set a Tolerable Upper Intake Level; noted that supplements of 50 mg/day or more have not been studied systematically, and described occasional serious and even fatal reactions to injected thiamin.) — National Academies Press: Thiamin chapter
PubMed Topic Searches
- PubMed: Thiamine safety, adverse effects, and upper intake
- PubMed: Parenteral thiamine: anaphylaxis and hypersensitivity
- PubMed: High-dose thiamine clinical trials and tolerability
- PubMed: Thiamine intestinal absorption and saturable transport
- PubMed: Water-soluble vitamins, toxicity, and renal excretion