Ketogenic Diet
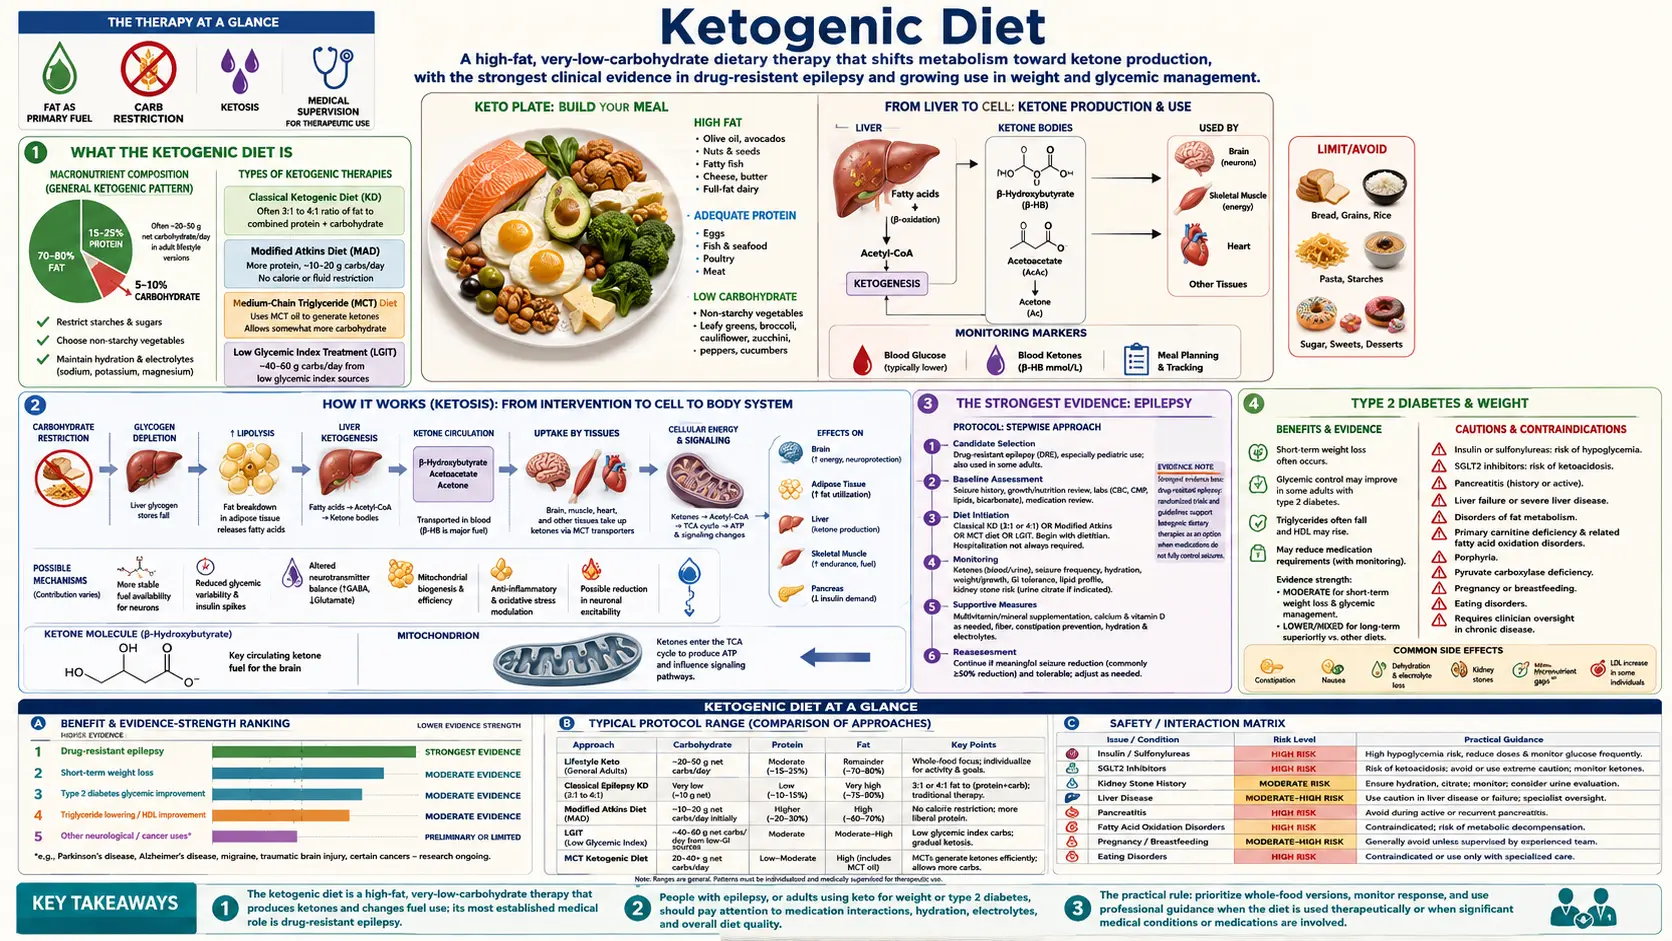
The ketogenic ("keto") diet is a very-low-carbohydrate, high-fat way of eating that forces the body to run on fat instead of sugar. It began as a medical treatment for epilepsy in the 1920s and remains a proven therapy for hard-to-control childhood seizures today. More recently it has drawn intense interest for type 2 diabetes and weight loss, where the evidence is promising but more limited. Many other popular claims — that keto boosts energy, prevents disease, or extends lifespan — are not well supported. This page lays out, honestly, where the science is strong, where it is still emerging, and where it simply isn't there yet.
Table of Contents
What the Ketogenic Diet Is
A ketogenic diet is built around three ideas: very few carbohydrates, plenty of fat, and a moderate amount of protein. Most versions keep total carbohydrates under about 50 grams a day — and stricter medical versions go lower, around 20-30 grams. To put that in perspective, a single bagel or a cup of rice can use up an entire day's carb budget.
When carbohydrates are cut this far, the body can no longer rely on its usual fuel — glucose (blood sugar) from carbs. Instead, the liver starts breaking down fat into compounds called ketone bodies, which most of the body and brain can burn for energy. This shift is called nutritional ketosis, and it is the whole point of the diet.
One important safety note up front: nutritional ketosis is not the same as diabetic ketoacidosis (DKA). DKA is a dangerous, sometimes life-threatening emergency in which ketones and blood sugar both climb to extreme levels, mostly in people with type 1 diabetes or, less often, type 2. In nutritional ketosis the body keeps ketones in a low, controlled range while blood sugar stays normal. The US drug label of empagliflozin, a diabetes drug of the SGLT2-inhibitor type (sodium-glucose co-transporter 2 inhibitors), describes an important exception for people taking these drugs: it lists a ketogenic diet and eating fewer calories among the triggers of ketoacidosis, warns that this ketoacidosis can happen with blood sugar below 250 mg/dL (even normal blood sugar), and reports deaths from it in people with type 2 diabetes on SGLT2 inhibitors. The warning signs the label lists are nausea, vomiting, stomach pain, tiredness and laboured breathing. Outside that exception, the two share a word but are completely different situations — one is a chosen dietary state, the other is a medical crisis.
How It Works (Ketosis)
Normally your body prefers glucose. Eat a meal with bread, fruit, or pasta and your blood sugar rises, your body burns what it needs, and it stores the rest. When carbohydrates stay very low for a day or two, those glucose stores run down and the body needs another fuel source.
That is where the liver steps in. It converts fatty acids — both from the food you eat and from your own body fat — into ketone bodies. Ketones travel through the bloodstream to tissues that need energy, and crucially they can cross into the brain, which cannot burn fat directly. In effect, ketones become a "backup fuel" the brain can use when sugar is scarce.
Reaching ketosis usually takes two to four days of strict carbohydrate restriction. Becoming fully "fat-adapted" — feeling steady energy and physical performance on this fuel — can take several more weeks. The early transition is when many people feel worst (see Risks), because the body is still switching over.
The Strongest Evidence: Epilepsy
The clearest, best-established use of the ketogenic diet has nothing to do with weight loss. It is epilepsy. Doctors at the Mayo Clinic developed the diet in the 1920s specifically to reduce seizures, and after nearly a century it is still a recognized, evidence-based therapy — especially for children whose seizures are not controlled by medication (so-called drug-resistant or refractory epilepsy).
This is not a fringe or alternative claim. In a landmark randomized controlled trial of 145 children whose seizures had not responded to at least two epilepsy drugs (Neal 2008), after three months the children on the ketogenic diet were having on average 62.0% of their starting number of seizures, while the comparison group on usual care rose to 136.9% of theirs — reported by the trial as a 75% decrease. 38% of the children on the diet had their seizures cut by more than half, against 6% of the comparison group. A 2020 Cochrane systematic review — among the most rigorous types of evidence in medicine — pooled 13 studies (932 participants) and concluded that ketogenic diets could be effective in children with drug-resistant epilepsy, while the evidence in adults remains uncertain; it rated all of the evidence as low to very low certainty, because the studies were small and not blinded.
The critical point for readers: medical ketogenic diets for epilepsy are prescribed and closely supervised by a specialist team, usually a neurologist and a dietitian, often starting in a hospital. They are far stricter than a casual "keto" eating plan and require careful monitoring. In the Neal 2008 trial, the most common side effects at three months were constipation, vomiting, lack of energy and hunger. The 2018 recommendations of the International Ketogenic Diet Study Group name several inherited disorders in which the diet is not used at all (listed under Risks), and children are screened for them before starting when there is a clinical concern.
Type 2 Diabetes & Weight
Outside epilepsy, the most promising research is in type 2 diabetes. Because the diet keeps carbohydrate — and therefore blood sugar — low, it can directly lower glucose. Several studies show that low-carbohydrate and ketogenic approaches can reduce hemoglobin A1c (HbA1c) (a three-month average of blood sugar), aid short-term weight loss, and let some people cut back on diabetes medications. A two-year study of a closely supported ketogenic program reported about a 1-point drop in hemoglobin A1c, roughly 10% weight loss, and large reductions in insulin and other drugs — though, importantly, it was not a randomized trial, so it can't fully separate the diet from the intensive coaching that came with it. A 2021 systematic review of randomized trials (Goldenberg, BMJ) found that at six months 57% of people on low-carbohydrate diets were in diabetes remission, against 31% on comparison diets — but it counted remission as hemoglobin A1c below 6.5% with or without diabetes medication. When remission meant below 6.5% without medication, the effects were smaller and not statistically significant, and remission was markedly lower in studies that included people using insulin.
That is genuinely encouraging — but it comes with honest caveats:
- Adherence is hard. Many people struggle to stay this strict long-term, and benefits fade if the diet is abandoned. In that same review, the data on remission at twelve months were sparse, ranging from a small benefit to a trivial increase in the risk of diabetes.
- The weight-loss edge shrinks over time. Low-carb diets often win in the first few months, but head-to-head meta-analyses find that the difference versus other diets is small and narrows over a year or two — on the order of about one kilogram. The best diet for weight loss is largely the one a person can actually stick with.
- Long-term and heart outcomes are less certain. Short-term metabolic markers improve, but we have less high-quality evidence on hard long-term outcomes like heart attacks or lifespan.
One safety point matters enormously here for anyone taking diabetes or blood-pressure medication. As blood sugar and blood pressure fall, existing doses can become too strong, causing dangerously low blood sugar (hypoglycemia) or low blood pressure. In the two-year supervised ketogenic programme described above (Athinarayanan 2019), insulin use fell by 62% and use of sulfonylurea diabetes pills by 100%. For people taking an SGLT2-inhibitor diabetes drug, the empagliflozin label lists the ketogenic diet as a trigger of ketoacidosis that can occur with near-normal blood sugar (see above).
Other Claims — What's Proven and What Isn't
The ketogenic diet has been attached to a long list of health promises. It's worth separating what's backed by evidence from what's speculation.
Areas of legitimate research interest (not yet proven therapies)
- Certain neurological conditions. Beyond epilepsy, researchers are studying ketogenic diets in conditions such as migraine and some neurodegenerative diseases. This work is early and investigational — interesting, but not established treatment.
- Cancer (as an add-on, under study). Some laboratory and small clinical studies are exploring ketogenic diets alongside standard cancer treatment. To be clear: this is experimental and unproven. A ketogenic diet is not an established cancer therapy; the studies under way test it alongside standard cancer treatment, not in place of it.
Popular claims that are largely unproven
- Claims that keto reliably boosts energy, sharpens thinking for everyone, slows aging, or improves general health in healthy people are not well supported by strong human evidence.
- Individual people sometimes feel better, but personal stories are not the same as proof, and the early transition often makes people feel worse, not better.
In short: keto is a real medical tool for specific problems, not a cure-all, and claims that sell it as one go beyond the evidence.
What You Eat
A ketogenic diet reshapes the plate around fat and protein while cutting almost all starch and sugar.
Emphasized foods
- Non-starchy vegetables — leafy greens, broccoli, cauliflower, zucchini, peppers, asparagus
- Eggs and fish (including fatty fish like salmon and sardines)
- Meat and poultry
- Nuts and seeds
- Healthy fats — olive oil, avocado and avocado oil
- Some dairy and cheese, in moderation
Foods cut out or strictly limited
- Grains and starches — bread, pasta, rice, cereal, oats
- Sugar and sweets — soda, candy, desserts, most packaged snacks
- Most fruit (small portions of berries are the usual exception)
- Starchy vegetables — potatoes, corn
- Most legumes — beans, lentils, chickpeas
Food quality matters — a lot. "Keto" is not automatically healthy. A diet built on vegetables, fish, olive oil, nuts, and avocado is very different from one built on processed meats, bacon, and butter. The first is sometimes called "clean" or whole-food keto; the second can be high in processed meat and saturated fat.
Risks, Side Effects & Who the Research Raises Concerns For
The ketogenic diet is a significant change, and it carries real downsides and risks.
Common side effects
- "Keto flu." In the first days to weeks, many people feel tired, headachy, irritable, foggy, or nauseated as the body adapts. It's usually temporary, and staying hydrated and replacing salt and other electrolytes often helps.
- Constipation and digestive changes, partly from cutting out fiber-rich grains, fruit, and legumes.
- Nutrient gaps. Eliminating whole food groups can shortchange fiber and certain vitamins and minerals.
- Cholesterol changes. Some people see a rise in low-density lipoprotein (LDL) ("bad") cholesterol on keto — meta-analysis data confirm low-density lipoprotein can go up even as some other markers improve. In a 2013 meta-analysis of trials lasting a year or more (Bueno), LDL cholesterol was 0.12 mmol/L higher on a very-low-carbohydrate ketogenic diet than on a low-fat diet. In children on the classic medical ketogenic diet, the 2018 International Ketogenic Diet Study Group recommendations note that in one study 60% had high cholesterol (above 200 mg/dL), and that by 12 months the blood fat values often return to normal.
- Kidney stones. In children on the classic medical ketogenic diet, one study found that giving citrate salts by mouth to every child from the start lowered the rate of kidney stones from 6.7% to 0.9%, according to the 2018 International Ketogenic Diet Study Group recommendations.
- Hard to sustain. The strictness leads many people to quit, and benefits tend to reverse if old eating patterns return.
Who the research and guidelines raise concerns for
- Type 1 diabetes — the risk of ketoacidosis is the main concern.
- Pancreatic, liver, or gallbladder disease — these organs are central to handling fat.
- Certain inherited metabolic disorders of fat transport and fat burning — keto can be dangerous. The 2018 International Ketogenic Diet Study Group recommendations list these as absolute contraindications (conditions in which the diet is not used at all): primary carnitine deficiency; carnitine palmitoyltransferase I or II deficiency; carnitine translocase deficiency; beta-oxidation (fat-burning) defects such as medium-chain, long-chain and short-chain acyl-CoA dehydrogenase deficiency and long-chain and medium-chain 3-hydroxyacyl-CoA dehydrogenase deficiency; pyruvate carboxylase deficiency; and porphyria.
- Pregnancy and breastfeeding. On pregnancy, the 2018 International Ketogenic Diet Study Group recommendations state that further studies are required before the diet can be called safe and effective; the report they cite is a case series of 2 women, in which one baby had an ear deformity.
- A history of eating disorders — the rigid rules can be harmful.
The bottom-line caution: the largest risks described here concern people who take medication or have a chronic condition — above all diabetes and blood-pressure drugs, where doses often need adjusting as blood sugar and blood pressure fall, and SGLT2-inhibitor diabetes drugs, whose label lists the ketogenic diet as a trigger of ketoacidosis.
The Bottom Line
The ketogenic diet is two things at once. It is a legitimate, well-proven medical therapy for drug-resistant epilepsy, especially in children — used under specialist care. And it is a promising tool that can help certain people with type 2 diabetes lower blood sugar, lose weight in the short term, and reduce medications — in the studies, under medical supervision — with honest expectations that long-term adherence is hard and the advantage over other diets tends to shrink.
What it is not is a magic diet or a proven cure for everything. Claims about energy, longevity, and general wellness are largely unproven, and "keto" done with lots of processed meat is not a health food. What matters most, on the evidence above, is the quality of the food, whether the approach can be kept up, and — for people with a medical condition or on medication — the drug effects described under Risks.
Key Research Papers
- Neal EG, Chaffe H, Schwartz RH, et al. The ketogenic diet for the treatment of childhood epilepsy: a randomised controlled trial. Lancet Neurology, 2008;7(6):500-506. — The pivotal randomized trial: after 3 months, mean seizures were 62.0% of baseline on the diet vs 136.9% in controls (reported as a 75% decrease); 38% of children on the diet had a more than 50% seizure reduction vs 6% of controls. — doi:10.1016/S1474-4422(08)70092-9
- Martin-McGill KJ, Bresnahan R, Levy RG, Cooper PN. Ketogenic diets for drug-resistant epilepsy. Cochrane Database of Systematic Reviews, 2020;(6):CD001903. — A systematic review (13 studies, 932 participants) concluding ketogenic diets could be effective in children with drug-resistant epilepsy, with the evidence in adults uncertain; all evidence rated low to very low certainty. — doi:10.1002/14651858.CD001903.pub5
- Goldenberg JZ, Day A, Brinkworth GD, et al. Efficacy and safety of low and very low carbohydrate diets for type 2 diabetes remission: systematic review and meta-analysis of published and unpublished randomized trial data. BMJ, 2021;372:m4743. — At 6 months, 57% on low-carb diets vs 31% on control diets reached remission (HbA1c below 6.5% with or without medication); smaller, non-significant effects when remission meant no medication; sparse remission data at 12 months. — doi:10.1136/bmj.m4743
- Athinarayanan SJ, Adams RN, Hallberg SJ, et al. Long-term effects of a novel continuous remote care intervention including nutritional ketosis for the management of type 2 diabetes: a 2-year non-randomized clinical trial. Frontiers in Endocrinology, 2019;10:348. — A supervised 2-year ketogenic program lowered HbA1c and medication use; note it was non-randomized and paired with intensive coaching. — doi:10.3389/fendo.2019.00348
- Bueno NB, de Melo ISV, de Oliveira SL, da Rocha Ataide T. Very-low-carbohydrate ketogenic diet v. low-fat diet for long-term weight loss: a meta-analysis of randomised controlled trials. British Journal of Nutrition, 2013;110(7):1178-1187. — Keto produced slightly more long-term weight loss (about 0.9 kg) but also raised LDL cholesterol; the practical difference was modest. — doi:10.1017/S0007114513000548
- Tobias DK, Chen M, Manson JE, Ludwig DS, Willett W, Hu FB. Effect of low-fat diet interventions versus other diet interventions on long-term weight change in adults: a systematic review and meta-analysis. Lancet Diabetes & Endocrinology, 2015;3(12):968-979. — Across many trials, differences in long-term weight loss between diet types were small, reinforcing that sustainability matters most. — doi:10.1016/S2213-8587(15)00367-8