Herring Vitamin D and B12 — A Dual Micronutrient Vehicle
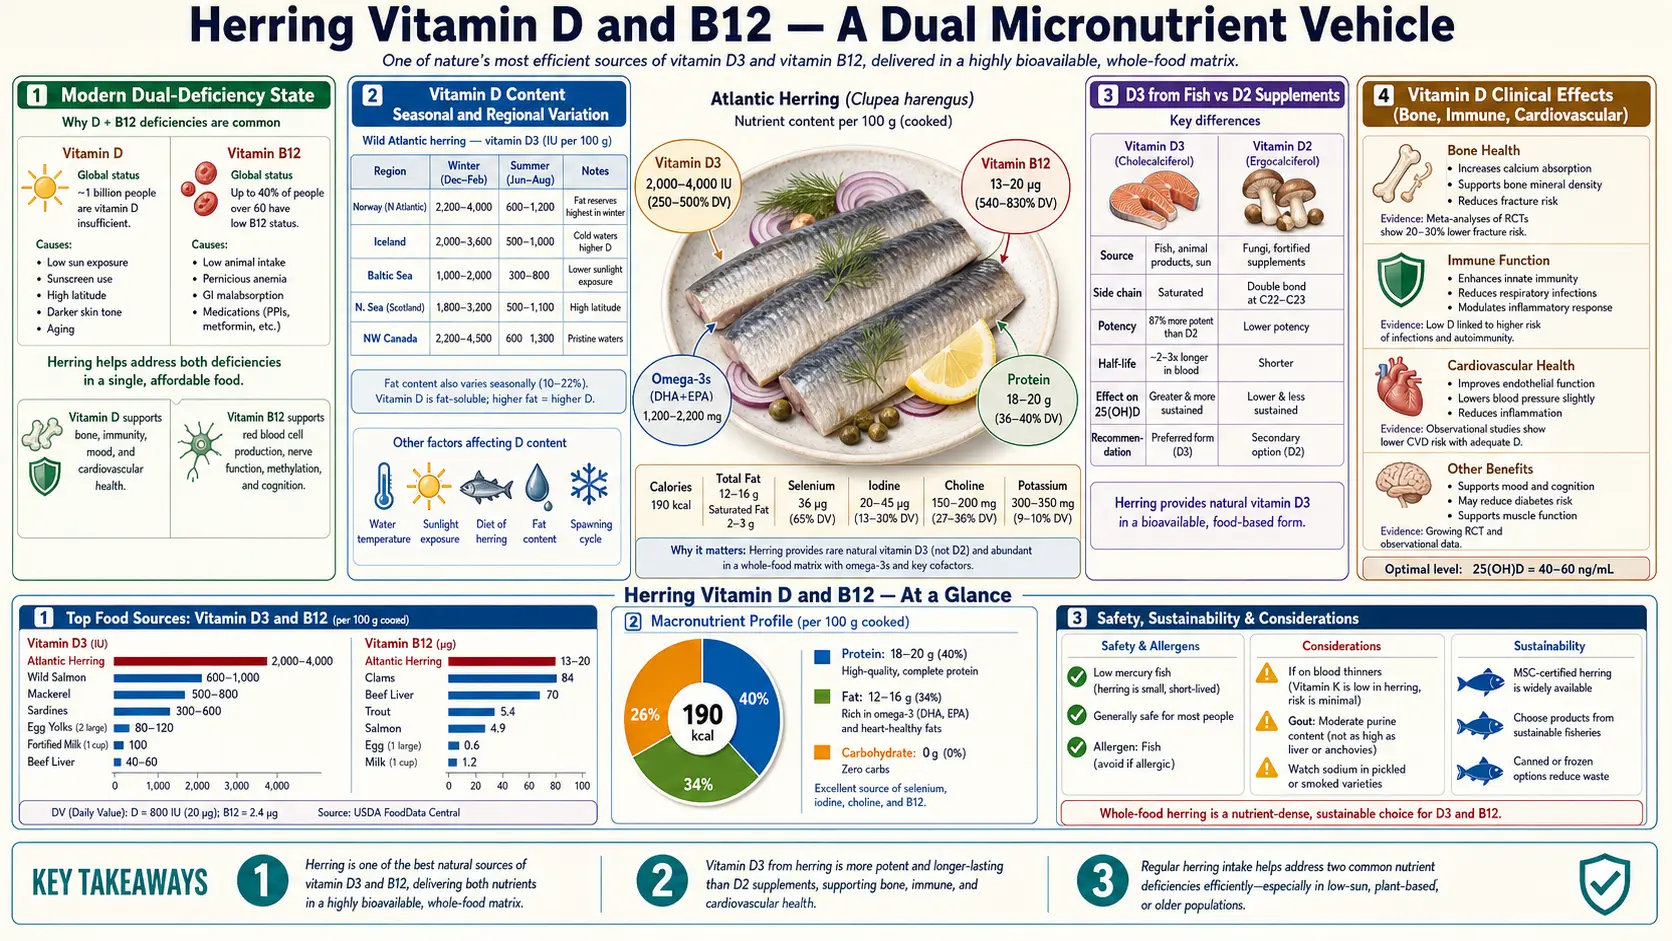
Vitamin D and Vitamin B12 are two of the most prevalent micronutrient deficiencies in industrialized populations — an estimated 40% of US adults have serum 25-hydroxyvitamin D (25(OH)D) below 20 ng/mL, and in large United States and United Kingdom surveys about 6% of people aged 60 and over are vitamin B12 deficient by blood level, with closer to 20% marginal in later life. Herring is one of a small number of natural foods that supplies both in a single serving: USDA's food table lists 167 international units (IU), or 4.2 µg, of vitamin D and 13.7 mcg of Vitamin B12 (570% of the adult Recommended Dietary Allowance, RDA) per 100 g of raw Atlantic herring.
Table of Contents
- The Modern Dual-Deficiency State
- Vitamin D Content: Seasonal and Regional Variation
- D3 (Cholecalciferol) from Fish vs D2 (Ergocalciferol) from Supplements
- Vitamin D Clinical Effects (Bone, Immune, Cardiovascular)
- B12 Content and Bioavailability
- The Four B12 Forms: Cyano, Methyl, Adeno, Hydroxo
- Methylmalonic Acid as the Functional B12 Marker
- B12 Depletion by Metformin and Proton Pump Inhibitors
- Population Targets and Intake Figures
- Key Research Papers
- Connections
- Featured Videos
The Modern Dual-Deficiency State
Vitamin D and B12 are nutritionally unrelated but epidemiologically converge in modern populations because both rely on access patterns that have eroded over the last century. Vitamin D was historically synthesized in skin from ultraviolet B (UVB) exposure to 7-dehydrocholesterol — indoor lifestyles, sunscreen use, latitude, and skin pigmentation have collectively reduced cutaneous synthesis to a fraction of pre-industrial levels. B12 is synthesized only by bacteria and archaea, and the human diet has historically obtained it primarily through animal foods (meat, eggs, dairy, fish) — vegetarian and vegan diets, age-related atrophic gastritis (which impairs intrinsic factor secretion), and long-term acid suppression have collectively reduced B12 absorption and intake.
The result is a substantial overlap deficiency: National Health and Nutrition Examination Survey (NHANES) data show that 41% of US adults have 25(OH)D <20 ng/mL, and a 2009 review of large United States and United Kingdom surveys found that about 6% of people aged 60 and over are vitamin B12 deficient (plasma vitamin B12 below 148 pmol/L), with the share rising with age, and that closer to 20% have marginal status (plasma vitamin B12 148–221 pmol/L) in later life. Functional dual deficiency — both nutrients suboptimal in the same individual — is increasingly common in older adults and explains a meaningful share of the fatigue, cognitive complaints, peripheral neuropathy, and bone fragility seen in primary care.
Herring intervenes on both axes simultaneously through the food matrix, without supplementation, and without the conversion uncertainties associated with sun exposure or vegan dietary patterns.
Vitamin D Content: Seasonal and Regional Variation
Fish Vitamin D content varies substantially with species, fat content, harvest season, and harvest location. A 2007 analysis of several fish species (Lu et al., J Steroid Biochem Mol Biol) found that the vitamin D content of fish “varied widely even within species”, that farmed salmon had about 25% of the vitamin D of wild salmon, and that the food tables listing vitamin D content are out of date and need to be re-evaluated. For Atlantic herring, the USDA food table (FoodData Central, SR Legacy) lists, per 100 g:
- Fresh Atlantic herring, raw — 167 international units (4.2 µg) per 100 g (USDA FoodData Central 175116)
- Pickled herring — 113 international units (2.8 µg) per 100 g (USDA FoodData Central 175118)
- Kippered herring — 86 international units (2.2 µg) per 100 g (USDA FoodData Central 173668)
- Fresh Pacific herring — USDA's table lists no vitamin D value for raw Pacific herring (USDA FoodData Central 173669)
For perspective, the same serving size of comparator fish:
- Wild Atlantic salmon: ~360 international units per 100 g
- Farmed Atlantic salmon: ~250 international units per 100 g (substantially lower than wild)
- Canned sardines in oil: ~270 international units per 100 g
- Canned albacore tuna: ~270 international units per 100 g
- Cod liver oil: 10,000 international units per 100 g (USDA FoodData Central 173577; a category outlier)
- Beef liver: ~50 international units per 100 g
- Egg yolk: ~40 international units per yolk
Seasonal variation is real: late-summer Atlantic herring harvested in waters with peak plankton blooms (the herring's ultraviolet B-exposed prey base) contains markedly more Vitamin D than winter-harvested fish.
D3 (Cholecalciferol) from Fish vs D2 (Ergocalciferol) from Supplements
Vitamin D exists in two principal forms in the human diet:
- Vitamin D3 (cholecalciferol) — synthesized in the skin of vertebrates from 7-dehydrocholesterol on ultraviolet B exposure. The only form found in fish, animal liver, and egg yolk.
- Vitamin D2 (ergocalciferol) — synthesized in fungi and some plants from ergosterol on ultraviolet (UV) exposure. The form found in mushrooms exposed to ultraviolet light and in some pharmaceutical and supplement preparations.
The Tripkovic 2012 meta-analysis (Am J Clin Nutr) pooled randomized trials that directly compared D2 and D3 in adults. Overall, D3 raised serum 25(OH)D more than D2 (P = 0.001). Split by how often the dose was given, D3 had the clear advantage when it was given as one large (bolus) dose (P = 0.0002), but that advantage was lost with daily supplementation. The authors called for more research on how the effects differ across age, sex and ethnicity.
Herring provides vitamin D3, the form that raised blood levels more in the pooled trials overall — a particularly relevant distinction for individuals with VDR (Vitamin D receptor) polymorphisms or CYP2R1 (the principal hepatic 25-hydroxylase) variants that further reduce D2 utilization.
Vitamin D Clinical Effects (Bone, Immune, Cardiovascular)
The clinical effects of adequate Vitamin D status span multiple organ systems:
- Bone — adequate 25(OH)D (the 2024 Endocrine Society guideline found no clear evidence defining the optimal target level for disease prevention) is required for normal intestinal calcium absorption (~30% absorption efficiency vs ~15% in deficiency) and for the suppression of secondary hyperparathyroidism that accelerates cortical bone loss. The Chapuy 1992 NEJM trial showed that 800 international units Vitamin D3 + 1,200 mg calcium was followed by 43% fewer hip fractures among the elderly French women (3,270 healthy ambulatory women, mean age 84) who completed the 18-month trial.
- Immune — Vitamin D receptors are expressed on most immune cell types; 1,25(OH)2D modulates T-cell differentiation, induces cathelicidin antimicrobial peptide production in macrophages, and is associated with reduced respiratory infection incidence (Martineau 2017 BMJ meta-analysis of 25 randomized controlled trials (RCTs), 11,321 participants).
- Cardiovascular — observational data consistently associate low 25(OH)D with hypertension, myocardial infarction (MI), and cardiovascular mortality. Interventional trials (VITAL, D-Health, ViDA) have been largely null for primary cardiovascular endpoints, suggesting the observational association is partly confounded.
- Diabetes risk — the D2d trial (2019 NEJM) showed no overall reduction in progression to type 2 diabetes from 4,000 international units/day D3 in prediabetic adults, but a subgroup analysis suggested benefit in participants with baseline 25(OH)D <20 ng/mL.
- Mortality — meta-analyses of supplementation trials suggest a modest (3–6%) reduction in all-cause mortality, driven primarily by reductions in cancer mortality at longer follow-up.
B12 Content and Bioavailability
Vitamin B12 is among the most concentrated micronutrients in animal foods, and herring is in the top tier of food sources:
- Beef liver — 70.6 mcg per 100 g (2,943% Recommended Dietary Allowance)
- Clams — 98.9 mcg per 100 g (4,121% Recommended Dietary Allowance)
- Atlantic herring — 13.7 mcg per 100 g (571% Recommended Dietary Allowance)
- Sardines — 8.9 mcg per 100 g (371% Recommended Dietary Allowance)
- Atlantic salmon — 4.8 mcg per 100 g (200% Recommended Dietary Allowance)
- Tuna — 2.5 mcg per 100 g (104% Recommended Dietary Allowance)
- Beef — 2.5 mcg per 100 g (104% Recommended Dietary Allowance)
- Whole milk — 0.4 mcg per 100 g (17% Recommended Dietary Allowance)
Absorption is the rate-limiting step. B12 in food is bound to protein, released by gastric acid and pepsin, transferred to haptocorrin in the stomach, freed by pancreatic proteases in the duodenum, and finally bound to intrinsic factor for receptor-mediated uptake in the terminal ileum. Absorption efficiency from a single dose is approximately 50% up to ~1.5 mcg, falling sharply at higher single doses due to saturation of the intrinsic factor pathway. The 13.7 mcg in a 100 g herring serving therefore delivers approximately 1.5 mcg of absorbed B12 from intrinsic-factor-dependent uptake, plus an additional ~1% from non-receptor-mediated diffusion.
As an intake figure, the 13.7 mcg in a 100 g serving is well above the 2.4 mcg/day adult Recommended Dietary Allowance, which is also an intake figure.
The Four B12 Forms: Cyano, Methyl, Adeno, Hydroxo
B12 exists in four principal chemical forms, distinguished by the upper axial ligand on the cobalt center:
- Cyanocobalamin — the synthetic form used in most supplements and food fortification. Stable, inexpensive, but requires intracellular conversion (and small cyanide release) to active coenzymes.
- Methylcobalamin — the coenzyme form used by methionine synthase in the methylation cycle. Required for conversion of homocysteine to methionine and indirectly for S-adenosylmethionine (SAMe) synthesis.
- Adenosylcobalamin — the mitochondrial coenzyme form used by methylmalonyl-CoA mutase. Required for propionate metabolism (branched-chain amino acids, odd-chain fatty acids, cholesterol side chain).
- Hydroxocobalamin — the form synthesized by gut bacteria and present in food. Long half-life; used as an injectable form for B12 deficiency treatment in Europe.
Food-source B12 (from herring and other animal foods) is predominantly hydroxocobalamin and the two coenzyme forms (methyl and adeno). This is a meaningful difference from cyanocobalamin supplements for individuals with MTRR (methionine synthase reductase) polymorphisms that impair the intracellular conversion of cyanocobalamin to methylcobalamin, and for individuals with rare cobalamin metabolism disorders (CblC, CblG) where the upstream conversion is impaired.
Methylmalonic Acid as the Functional B12 Marker
Serum B12 (cobalamin) is a poor marker of functional B12 status. Approximately 70% of circulating B12 is bound to haptocorrin (not biologically available); only the 20–30% bound to transcobalamin (holoTC) is delivered to peripheral tissues. Total serum B12 within the "normal" range (200–900 pg/mL) does not exclude functional deficiency.
The gold-standard functional markers are:
- Methylmalonic acid (MMA) — elevated when adenosylcobalamin is inadequate to support methylmalonyl-CoA mutase function. Specific for B12 deficiency (not confounded by folate). Reference range typically <0.4 µmol/L.
- Homocysteine — elevated in both B12 deficiency (methionine synthase impairment) and folate deficiency. Less specific than methylmalonic acid, but useful in combination.
- Holotranscobalamin (holoTC, active B12) — the fraction of serum B12 actually deliverable to tissues. More sensitive than total B12, particularly in early deficiency.
A "normal" total B12 result therefore does not by itself exclude deficiency. In people with peripheral neuropathy, fatigue, glossitis, or cognitive complaints, methylmalonic acid or holoTC is the test used to confirm it — a question that arises most often in adults over 60, long-term metformin users, proton pump inhibitor (PPI) users, vegans, and patients with history of gastric surgery or atrophic gastritis.
B12 Depletion by Metformin and Proton Pump Inhibitors
Two of the most commonly prescribed long-term medications in modern primary care meaningfully reduce B12 absorption:
- Metformin — the Diabetes Prevention Program Outcomes Study (DPPOS) found low B12 (≤203 pg/mL) in 4.3% of the metformin group vs 2.3% of the placebo group at 5 years, and in 7.4% vs 5.4% at 13 years (a difference that was not statistically significant at 13 years). Low or borderline-low B12 (≤298 pg/mL) was 19.1% vs 9.5% at 5 years and 20.3% vs 15.6% at 13 years. Years of metformin use were linked to higher odds of B12 deficiency (odds ratio 1.13 per year of use), and nerve damage (neuropathy) was more common in metformin users with low B12. Mechanism: metformin disrupts calcium-dependent ileal absorption of the intrinsic factor–B12 complex. Oral calcium (1,200 mg/day) has been reported to partly reverse this; B12 from supplements or from foods such as herring adds to intake directly.
- Proton pump inhibitors (PPIs) — suppress gastric acid required to liberate B12 from dietary protein. Long-term proton pump inhibitor use (>2 years) is associated with a 65% increased risk of B12 deficiency (Lam 2013 JAMA, case-control of 25,956 cases). Doses of more than 1.5 PPI pills a day were more strongly associated with B12 deficiency (odds ratio 1.95) than doses of less than 0.75 pills a day (odds ratio 1.63).
- Histamine-2 (H2) receptor blockers — smaller effect than proton pump inhibitors but same mechanism. A 2-year or longer supply of H2 blockers is associated with a 25% increased risk of B12 deficiency.
- Nitrous oxide — irreversibly oxidizes the cobalt center of B12, inactivating methionine synthase. Single-exposure for general anesthesia is generally tolerated; recreational use or prolonged anesthetic exposure can precipitate acute B12 deficiency neuropathy.
For people on long-term metformin or proton pump inhibitor therapy, B12-dense fish such as herring, sardines, salmon and mackerel are food sources of the vitamin. The DPPOS authors concluded: “Routine testing of vitamin B12 levels in metformin-treated patients should be considered.”
Population Targets and Intake Figures
For a 65-kg adult, the intake figures compare as follows:
- Vitamin D — the 2024 Endocrine Society guideline found no clear evidence defining the optimal 25(OH)D level required for disease prevention, and it suggests against routine 25(OH)D blood testing in the populations it considered. It suggests vitamin D above the standard intake (without testing) for children and adolescents aged 1 to 18, adults over 75, pregnancy and high-risk prediabetes, and suggests against vitamin D above the current Dietary Reference Intakes in healthy adults younger than 75. The panel noted the scarcity of natural food sources rich in vitamin D. USDA lists 167 international units of vitamin D per 100 g of raw Atlantic herring.
- B12 target — Recommended Dietary Allowance 2.4 mcg/day; functional adequacy typically requires 4–6 mcg/day of intake. Two weekly 100 g servings of herring supply approximately 4 mcg/day equivalent — sufficient for most adults without absorption impairment.
- Pregnancy and lactation — Vitamin D Recommended Dietary Allowance 600 international units/day, B12 Recommended Dietary Allowance 2.6 mcg/day. Two weekly servings of herring contribute meaningfully to both, while delivering the eicosapentaenoic acid (EPA) + docosahexaenoic acid (DHA) required for fetal neural development.
- Vegan transition — fatty fish such as herring supply B12, Vitamin D, omega-3 fats and iodine together, the nutrients the page describes as running low on a long-term vegan pattern.
- Older adults — the population at highest risk of dual deficiency. Herring supplies both nutrients in one food, rather than as separate D3 and B12 supplements.
Key Research Papers
- Lu Z et al., an evaluation of the vitamin D3 content in fish (J Steroid Biochem Mol Biol 2007) — PubMed PMID: 17267210
- Holick MF, vitamin D deficiency review (NEJM 2007) — PubMed PMID: 17634462
- Tripkovic L et al., D2 vs D3 supplementation meta-analysis (Am J Clin Nutr 2012) — PubMed PMID: 22552031
- Chapuy MC et al., vitamin D3 and calcium to prevent hip fractures in elderly women (NEJM 1992) — PubMed PMID: 1331788
- Martineau AR et al., vitamin D supplementation to prevent acute respiratory tract infections meta-analysis (BMJ 2017) — PubMed PMID: 28202713
- Manson JE et al., VITAL vitamin D and cardiovascular disease and cancer prevention (NEJM 2019) — PubMed PMID: 30415629
- Stabler SP, vitamin B12 deficiency clinical practice review (NEJM 2013) — PubMed PMID: 23301732
- Aroda VR et al., long-term metformin use and vitamin B12 deficiency in DPPOS (J Clin Endocrinol Metab 2016) — PubMed PMID: 26900641
- Lam JR et al., proton pump inhibitors and H2 blockers and risk of B12 deficiency (JAMA 2013) — PubMed PMID: 24327038
- Allen LH, how common is vitamin B-12 deficiency? (Am J Clin Nutr 2009) — PubMed PMID: 19116323
- Carmel R, biomarkers of cobalamin (vitamin B-12) status in the epidemiologic setting (Am J Clin Nutr 2011) — PubMed PMID: 21593511
- Pittas AG et al., D2d vitamin D supplementation and prevention of type 2 diabetes (NEJM 2019) — PubMed PMID: 31173679
- Demay MB et al., vitamin D for the prevention of disease: an Endocrine Society clinical practice guideline (J Clin Endocrinol Metab 2024) — PubMed PMID: 38828931