Melioidosis
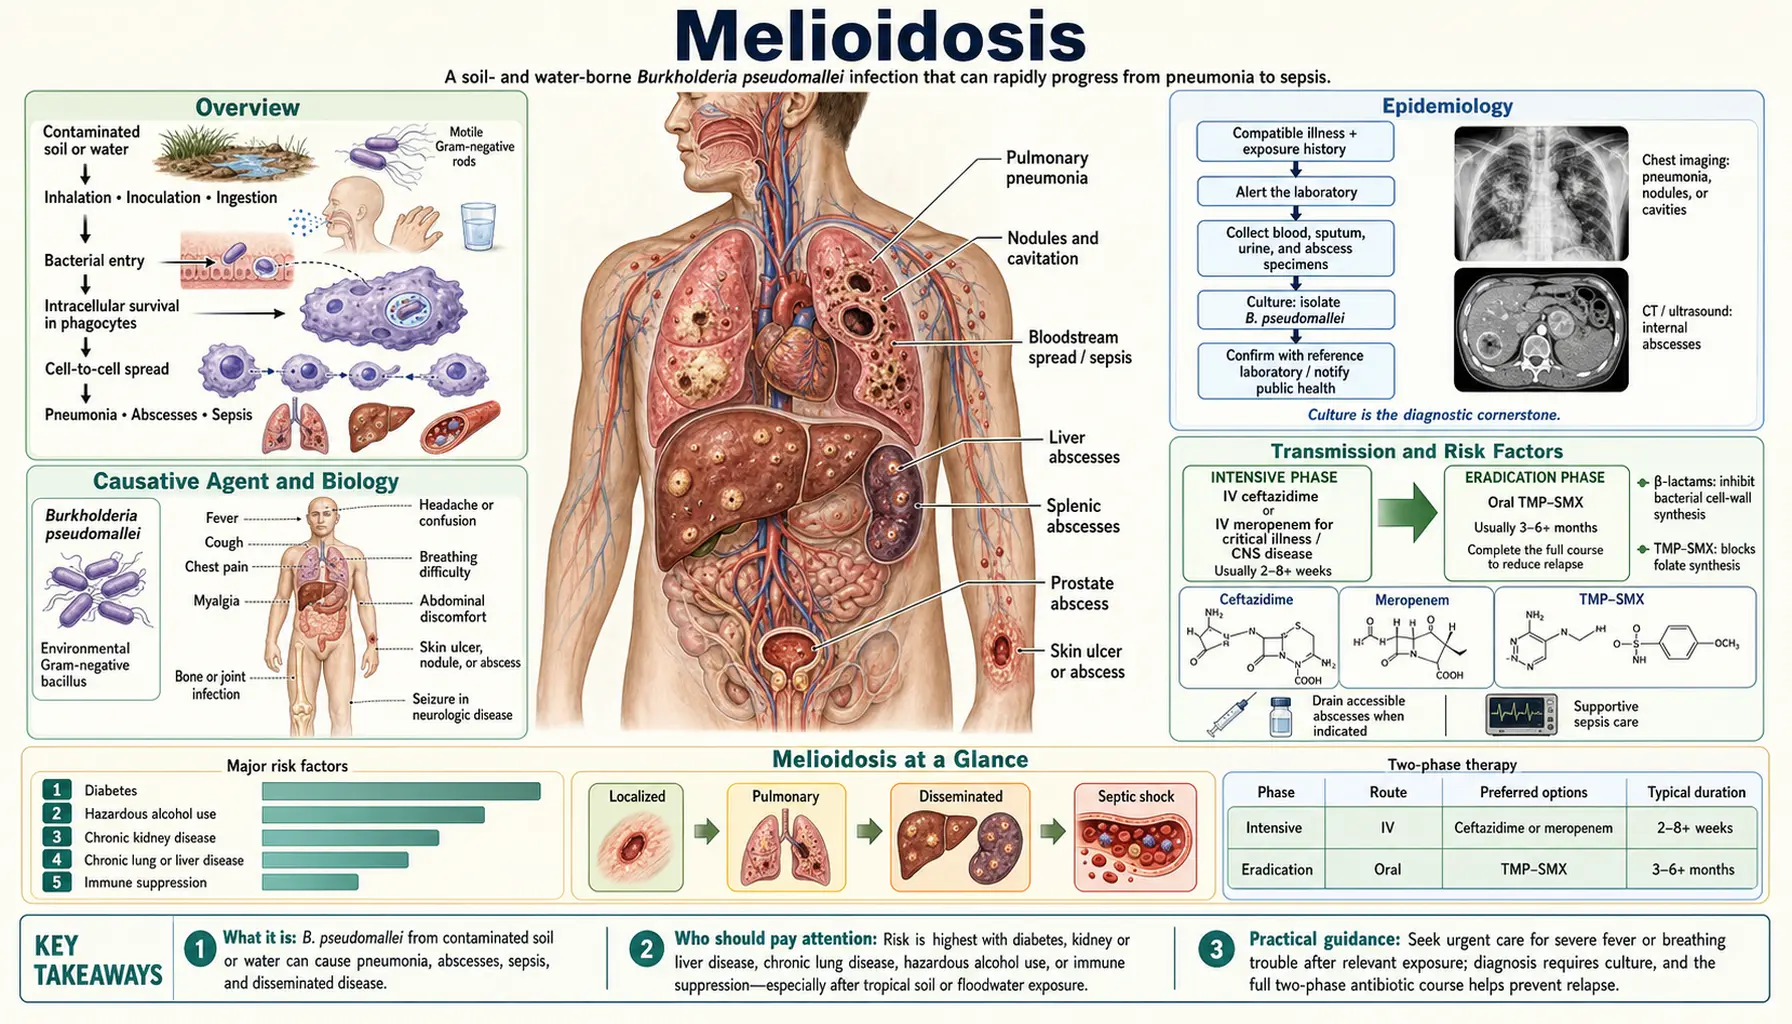
Table of Contents
Overview
Melioidosis is a serious bacterial infection caused by Burkholderia pseudomallei, a gram-negative bacillus that lives in soil and water in tropical and subtropical regions. It is sometimes called "the great mimicker" because its clinical presentations range from a localized skin ulcer to overwhelming septicemia, and it can look like tuberculosis, typhoid fever, or pneumonia on first presentation.
Global mortality is approximately 89,000 deaths per year — comparable to measles — yet the disease remains largely unknown outside endemic regions because it is chronically underreported and misdiagnosed. Diagnostic cultures and clinical awareness are lacking across most of the high-burden settings in South and Southeast Asia, meaning many cases are recorded as "culture-negative sepsis" and never confirmed.
The name comes from the Greek words for "resembling glanders" — glanders being another bacterial disease historically associated with horses and mules. B. pseudomallei and glanders (B. mallei) are closely related, though melioidosis is primarily a soil-borne environmental infection rather than an animal-contact disease.
Causative Agent and Biology
Burkholderia pseudomallei is a motile, aerobic, gram-negative rod. It is an environmental saprophyte naturally found in moist soil and stagnant surface water in endemic regions, particularly at depths of 10–30 cm in rice paddies and agricultural soils. It thrives in the wet season and can survive in soil for months to years under the right conditions.
One of the most clinically important characteristics of B. pseudomallei is its intrinsic resistance to many commonly used antibiotics. It is naturally resistant to:
- Penicillin G and ampicillin
- First and second generation cephalosporins (cephalexin, cefazolin, cefuroxime)
- Macrolides (azithromycin, clarithromycin)
- Aminoglycosides (gentamicin, tobramycin)
- Colistin
This resistance is chromosomally encoded via efflux pumps and beta-lactamases and cannot be overcome by combination or dose escalation. Empirical antibiotic regimens that cover most gram-negative sepsis will fail against melioidosis — which is a major reason why unrecognized melioidosis in endemic regions carries such high mortality.
Because of its high virulence, environmental stability, and aerosol infectivity, B. pseudomallei is listed by the U.S. Federal Select Agent Program as a Tier 1 select agent, that program's highest-concern category; separately, the U.S. Centers for Disease Control and Prevention (CDC) lists it as a Category B bioterrorism agent. Laboratories handle it under Biosafety Level 3 (BSL-3) conditions. Laboratory-acquired melioidosis has been documented in laboratories that were not warned a sample might contain it, which is why hospitals notify the microbiology laboratory before sending specimens when melioidosis is suspected.
Epidemiology
Melioidosis is endemic across a wide tropical belt. The regions with the highest recognized burden include:
- Northern Australia — particularly the Top End of the Northern Territory and the Darwin region. Approximately 50 cases per year occur in a relatively small population, with a high case-fatality rate even with access to intensive care.
- Southeast Asia — Thailand (northeastern Thailand has the highest prevalence in the country), Malaysia, Vietnam, Singapore, Cambodia, Laos, and Myanmar are all endemic. Thailand's Khon Kaen region has among the highest documented incidence globally.
- South Asia — India is increasingly recognized as carrying a very large burden, particularly in Odisha/Orissa state and Tamil Nadu. A 2016 modelling study estimated that India alone accounts for nearly 45% of the global disease burden — a figure that was shocking to the international infectious disease community and reflects decades of underdiagnosis.
- Sub-Saharan Africa — cases are being recognized with increasing frequency. Many past cases were likely recorded as culture-negative sepsis due to absence of adequate laboratory infrastructure.
- The Americas — Brazil, Ecuador, Mexico, and parts of the Caribbean have documented endemic transmission, historically considered non-endemic but now clearly established.
- The continental United States — three people living in the same Mississippi Gulf Coast county developed melioidosis within a 3-year period (2020–2023), all infected by the same Western Hemisphere strain, which was also found in three environmental samples taken from one patient's property. Before that investigation the bacterium had never been isolated from the environment in the continental United States, and the authors concluded the infections were acquired locally (Petras et al., 2023).
A striking seasonal pattern exists: cases peak dramatically during the monsoon and wet season. Heavy rainfall disrupts soil, creates aerosols carrying bacteria, floods rice paddies, and brings agricultural workers into closer contact with contaminated soil and standing water.
The global burden has been systematically underestimated. A landmark 2016 modelling study published in Nature Microbiology estimated 165,000 cases and 89,000 deaths per year worldwide — placing melioidosis in the same mortality league as measles, yet with a fraction of the public health attention or research funding.
Transmission and Risk Factors
Melioidosis is not transmitted from person to person. All infections originate from environmental exposure. Three main routes have been established:
- Inhalation of aerosols from contaminated soil and water. This is especially common during heavy monsoon rainstorms, typhoon or cyclone events, and agricultural activities generating dust from contaminated soil. This route tends to cause primary pneumonia and is the most common route in Australia.
- Skin inoculation through cuts, abrasions, or skin trauma during contact with contaminated soil or water. This is the most common route in rice paddy workers and other agricultural laborers who work barefoot or with exposed skin.
- Ingestion of contaminated water or food. Less common but documented, particularly in outbreak settings associated with contaminated water supplies.
An imported product has also carried the bacterium. A 2022 report described four people in Georgia, Kansas, Minnesota and Texas who developed melioidosis without having travelled; all four were infected by the same strain, which was linked to an aromatherapy room spray imported from a region where melioidosis is endemic (Gee et al., 2022).
The most important risk factors — in rough order of clinical impact:
- Diabetes mellitus — the single most powerful risk factor, present in 40–60% of all melioidosis cases. Diabetes impairs neutrophil chemotaxis, phagocytic killing, and oxidative burst, allowing B. pseudomallei to evade immune clearance. Diabetic patients who acquire melioidosis have markedly higher mortality than non-diabetic patients.
- Chronic kidney disease — impairs immune response and commonly co-exists with diabetes in endemic populations.
- Alcoholism — causes immune suppression, nutritional deficiencies, and increases aspiration risk (relevant for pulmonary melioidosis).
- Thalassemia — very common in Southeast Asia; the mechanism appears to involve altered macrophage function and iron dysregulation.
- Immunosuppression — corticosteroids, tumor necrosis factor-alpha inhibitors (used for rheumatoid arthritis, inflammatory bowel disease), advanced human immunodeficiency virus (HIV), and solid organ transplant recipients are all at elevated risk.
- Occupational exposure — farmers, rice paddy workers, and military personnel training in endemic areas are disproportionately affected.
Healthy, immunocompetent individuals can also be infected, particularly through intense aerosol exposure such as typhoons or military helicopter operations over contaminated terrain. However, severe disease is far more common in people with the risk factors listed above.
Clinical Manifestations
Melioidosis earns the title "the great mimicker" because no single presentation is pathognomonic. The disease can affect virtually any organ system, and its presentation overlaps with tuberculosis, typhoid fever, staphylococcal septicemia, and many other conditions.
Pulmonary Melioidosis
The most common form, accounting for 50–60% of cases. Severity ranges from mild pneumonia to life-threatening acute respiratory distress syndrome (ARDS). Upper lobe involvement with cavitation is characteristic and strongly mimics pulmonary tuberculosis — including on chest X-ray and computed tomography (CT) scan, where consolidation, cavitation, and nodules are indistinguishable from tuberculosis (TB). A patient from an endemic region with "tuberculosis-like" pneumonia that does not respond to standard antibiotics, or whose tuberculosis cultures are negative, is the classic situation in which melioidosis is considered.
Septicemia
Bacteremia with metastatic seeding to multiple organs. Without appropriate antibiotic therapy, septicemic melioidosis is nearly universally fatal. Even with treatment, mortality in resource-limited settings can exceed 50%. Features include high fever, rigors, and rapid clinical deterioration to septic shock and multi-organ failure.
Localized Infection
Skin and soft tissue infection presents as ulcers, cellulitis, or abscesses — often minimally tender or painless, which can mislead clinicians. Regional lymphadenopathy is common. A particularly characteristic presentation is parotid gland abscess in children in northeastern Thailand, where melioidosis is the most common cause of this finding.
Neurological Melioidosis
Brain abscess and, uniquely, a flaccid paraplegia or limb weakness caused by brainstem and spinal cord involvement. This predilection for the brainstem and spinal cord is unusual among bacterial pathogens and, when present, is highly suggestive of melioidosis in an endemic setting. Neurological melioidosis carries high mortality and significant long-term neurological disability in survivors.
Genitourinary Involvement
Prostatic abscess occurred in 20% of men in the 20-year Darwin study in Australia (76 of 372 male patients) and is often the presenting manifestation, causing urinary retention or recurrent urinary tract infections. It is found by digital rectal examination, computed tomography, or magnetic resonance imaging (MRI) and drained surgically or under imaging guidance — antibiotic therapy alone will not cure a walled-off abscess.
Septic Arthritis and Osteomyelitis
Bone and joint infection can occur as a metastatic focus during bacteremia. Long bones and vertebrae may be involved. Treatment requires both prolonged antibiotic therapy and often surgical debridement.
Relapse
Relapse means the infection returns after treatment has finished. Under the standard international approach, reported relapse rates can exceed 5%. In a Darwin study of 215 patients who received a longer intravenous phase (median 26 days), one patient (0.5%) relapsed over 28 months of follow-up and 11 (5.1%) had the infection flare during the tablet phase — even though only 108 patients (50.2%) completed that tablet phase and 58 (27.0%) took none of it (Pitman et al., 2015; see Treatment section). Relapse may present as a different clinical form from the original infection — a patient whose primary illness was pneumonia may relapse with skin abscess or septicemia.
Incubation and Latency
The typical incubation period after exposure is 2 to 28 days, though most symptomatic cases present within 1–3 weeks. However, one of the most remarkable and clinically important features of melioidosis is its capacity for prolonged latency.
Burkholderia pseudomallei can remain dormant in host tissue — particularly the lungs and lymph nodes — for months to decades. The best-documented examples come from military veterans: US, UK, and Australian soldiers who served in Southeast Asia during the Vietnam War era (1960s–1980s) developed reactivation melioidosis up to 40 years after leaving endemic regions. Reactivation is typically triggered by a new immunosuppressive event — the onset of diabetes, initiation of corticosteroid therapy, cancer chemotherapy, or another serious illness.
The practical consequence is that unexplained sepsis, pneumonia or abscess in a person who spent time in an endemic region — even decades ago — can be melioidosis, which is why a travel and military service history going back to childhood is relevant to the diagnosis.
Bioterrorism Potential
Burkholderia pseudomallei is classified as a U.S. Centers for Disease Control and Prevention Category B biological agent, meaning it is considered a credible potential bioterrorism threat. The characteristics that make it a concern include:
- High virulence and a low infectious dose via the aerosol route
- Intrinsic resistance to many common antibiotics, limiting treatment options in a mass-casualty scenario
- Aerosol dispersal could cause an outbreak of severe pneumonia in a non-immune population with no prior exposure
- No licensed vaccine exists
- Historical evidence of weaponization research by the former Soviet bioweapons program
- Environmental stability — it can survive in soil for extended periods
For this reason melioidosis is one of the causes considered in an unexplained cluster of severe pneumonia in a non-endemic region, particularly after a mass gathering, in a conflict zone, or following a natural disaster or unusual environmental event. A cluster of culture-positive B. pseudomallei outside the recognized endemic belt is reportable to public health authorities.
Diagnosis
Diagnosis requires a high index of suspicion — the first step is simply thinking of melioidosis in the right clinical context. The history that points to it covers residence in or travel to endemic regions, occupational soil or water exposure, and underlying risk factors such as diabetes.
Culture (Gold Standard)
Culture remains the definitive diagnostic method. Collect blood cultures, sputum, urine, and swabs or aspirates from any accessible wound, ulcer, or abscess. B. pseudomallei grows on standard bacteriology media (blood agar, MacConkey agar) within 48–72 hours. Colonial morphology is characteristic: colonies are wrinkled with a metallic sheen, though they may appear smooth initially and develop the wrinkled appearance over 3–4 days of incubation. Ashdown's selective medium (containing gentamicin and crystal violet) improves sensitivity for non-sterile sites such as sputum and wound swabs.
Laboratory safety: B. pseudomallei is a BSL-3 pathogen, and processing it with standard open-bench techniques creates an aerosol hazard for laboratory staff. Laboratory-acquired melioidosis infections have been documented in facilities that were not warned, which is why hospitals tell the microbiology laboratory that melioidosis is suspected before specimens are sent.
Rapid Diagnostics
- Lateral flow assay (LFA): A point-of-care antigen detection test that can be performed at the bedside or in resource-limited settings. Sensitivity is approximately 80% in bacteremic patients. It has been validated in Thailand and is increasingly deployed in endemic regions where culture infrastructure is limited.
- Polymerase chain reaction (PCR): Highly sensitive in blood during active septicemia. Increasingly available in reference laboratories and hospital systems in high-income countries. Particularly useful for rapid confirmation when the LFA is positive or when clinical suspicion is very high.
Serology
The indirect hemagglutination (IHA) antibody test is widely used, particularly in Thailand. However, its utility is limited by high background seropositivity in endemic populations — up to 30–40% of healthy adults in northeastern Thailand have detectable antibodies from subclinical past exposure. A single high titer or a fourfold rise in paired samples is more informative. Serology is most useful in travelers and immigrants from non-endemic regions presenting with unexplained illness, where background seropositivity is zero.
Imaging
- Chest X-ray and computed tomography: Look for upper lobe cavitation, nodules, and consolidation — patterns that mimic tuberculosis.
- Computed tomography of the abdomen and pelvis: Essential to detect splenic microabscesses, prostatic abscess, hepatic abscesses, and lymphadenopathy — findings that guide drainage decisions.
- Magnetic resonance imaging of the brain and spine: Required when neurological signs or symptoms suggest central nervous system (CNS) involvement. Characteristically shows brainstem and spinal cord lesions in neurological melioidosis.
Treatment
Treatment of melioidosis is divided into two phases: an intravenous (intensive) phase, then months of tablets (the eradication phase). International guidelines set the minimum intravenous phase at 10–14 days followed by 3–6 months of oral therapy; with that approach, reported rates of the infection returning after treatment can exceed 5%. Where the intravenous phase was extended according to clinical progress (median 26 days in the Darwin series of 215 patients), relapse was 0.5% at 28 months even though half the patients did not finish the tablet phase, and the only risk factors found for the infection flaring during treatment were leaving hospital against advice during the intravenous phase (odds ratio 6.2) and septic shock (odds ratio 5.3).
Phase 1: Intensive (Intravenous) Phase
Duration: minimum 10–14 days for uncomplicated pulmonary disease; extended to 4–8 weeks for central nervous system infection, osteomyelitis, prostatic abscess, or deeply seated infection.
- Ceftazidime 2g intravenous (IV) every 6–8 hours — first-line agent. A third-generation cephalosporin with reliable activity against B. pseudomallei. In the 1989 Lancet trial (White et al.), ceftazidime was compared with the four-drug "conventional therapy" of the time — chloramphenicol, doxycycline, trimethoprim and sulphamethoxazole. Of 161 patients entered, 65 had bacteriologically confirmed melioidosis, and mortality was 37% with ceftazidime against 74% with the conventional regimen (p = 0.009) — a halving of deaths, and one of the most consequential trials in tropical infectious disease.
- Meropenem 1g intravenous every 8 hours — preferred over ceftazidime for central nervous system melioidosis (better blood-brain barrier penetration), critically ill patients in septic shock, and confirmed ceftazidime treatment failure. Imipenem is an alternative carbapenem but inferior to meropenem for central nervous system penetration.
Phase 2: Eradication (Oral) Phase
This is the phase most commonly abbreviated or abandoned. Oral therapy runs for 3 months in uncomplicated disease, or 6 months when bone, the central nervous system or the prostate is involved; Australian practice uses 12 weeks and Thai practice 20 weeks.
- Trimethoprim-sulfamethoxazole (TMP-SMX / co-trimoxazole): 8/40 mg/kg/day in two divided doses. Standard adult dosing is two double-strength tablets (each 800mg/160mg) twice daily. TMP-SMX can cause rash, bone marrow suppression (a drop in blood counts) and a rise in blood potassium (hyperkalemia), especially in people with existing kidney disease, so monthly blood counts and electrolytes are the usual monitoring during this phase.
- Amoxicillin-clavulanate 875/125mg twice daily can be added alongside TMP-SMX. This combination is particularly important in pregnancy, where TMP-SMX is contraindicated in the first trimester and near term due to teratogenicity and neonatal risks.
Two Thai randomized trials have tested how long and how intensive this phase needs to be. In a 658-patient trial, people who had already taken 12 weeks of trimethoprim-sulfamethoxazole either stopped or continued for another 8 weeks: culture-confirmed recurrence within a year was 5 patients (2%) after 12 weeks versus 2 (1%) after 20 weeks, so the trial's non-inferiority criterion for recurrence was not met, but deaths from any cause were lower with the shorter course (1 patient, 0.3%, versus 11, 3%), and on that basis the authors favoured the 12-week regimen (Anunnatsiri et al., 2021). In the earlier MERTH trial of 626 patients, adding doxycycline to trimethoprim-sulfamethoxazole did not reduce recurrence (16 patients, 5%, versus 21, 7%) and caused more adverse drug reactions (53% versus 39%), so the single drug was judged preferable on tolerability (Chetchotisakd et al., 2014).
Antibiotics That Do Not Work Against It
The following antibiotics are ineffective against B. pseudomallei because of its built-in resistance, and are not used as primary therapy:
- Penicillin G, ampicillin, amoxicillin alone
- First and second generation cephalosporins: cephalexin, cefazolin, cefuroxime
- Macrolides: azithromycin, clarithromycin
- Aminoglycosides: gentamicin, tobramycin
- Colistin
This is why unrecognized melioidosis so often leads to death in endemic regions — patients present with sepsis or pneumonia and are treated with penicillin-based or macrolide-based empirical regimens that are standard for bacterial pneumonia and sepsis worldwide but completely inactive against this pathogen.
Surgical Management
Accessible abscesses are drained: prostatic, parotid, splenic and hepatic abscesses are treated with image-guided or surgical drainage, because antibiotic therapy alone will not sterilize a walled-off abscess. Bone and joint infection (osteomyelitis, septic arthritis) often needs surgical debridement alongside prolonged antibiotics.
Prevention and Prognosis
Prevention
- No licensed vaccine is available. Vaccine development is an active research priority given the global burden and bioterrorism classification, but no candidate has completed phase 3 trials.
- Personal protective equipment: footwear and protective gloves are the measures described for agricultural and soil work in endemic regions, particularly during the wet season; barefoot work in rice paddies is the main route of skin inoculation.
- Diabetes: diabetes is the strongest risk factor for melioidosis and for dying of it, so blood glucose control is part of the risk picture for people living in or travelling to endemic regions.
- Chemoprophylaxis: there is no routine preventive antibiotic for travellers. Doxycycline prophylaxis has been discussed for military personnel with extreme exposure, but it is not standard practice and the evidence for it is limited.
- Water: untreated surface water in endemic areas is one documented source of infection by the swallowing route.
Prognosis
Outcomes depend heavily on healthcare setting, speed of diagnosis, and underlying risk factors:
- Australia (optimized intensive care unit (ICU) care, rapid diagnosis): Overall case fatality rate of 10–20%.
- Thailand and most developing-world settings: Case fatality rate of 40–75%, primarily due to diagnostic delay, empirical antibiotics that are ineffective, and limited intensive care capacity.
- Septicemic melioidosis without intensive care unit-level supportive care: Mortality exceeds 90%.
- Central nervous system melioidosis: High mortality and significant permanent neurological disability in survivors even with appropriate therapy.
- Relapse: with the standard international regimen, reported relapse rates can exceed 5%; in the Darwin series where the intravenous phase was extended, relapse was 0.5% at 28 months despite half the patients not finishing the tablet phase (Pitman et al., 2015). Relapse is treatable — a full second course of intensive followed by eradication therapy is effective — but each episode of severe disease carries its own mortality risk, particularly in patients with diabetes or other comorbidities.
The 20-year Darwin prospective study of 540 cases (Currie et al., 2010) shows how much the setting and the person's health matter. Overall 77 people died (14%), but the death rate fell from 30% in the first five years to 9% in the last five. Of those 77, 75 had at least one risk factor — diabetes in 39% of all cases, hazardous alcohol use in 39%, chronic lung disease in 26% and chronic kidney disease in 12% — and the two who did not were elderly. Pneumonia was the presenting form in 278 people (51%), 298 (55%) had the bacterium in their blood and 116 (21%) went into septic shock. 436 cases (81%) presented during the monsoonal wet season. The authors' conclusion was that melioidosis behaves as an opportunistic infection that is unlikely to kill a healthy person when it is diagnosed early and the right antibiotics and critical care are available.
The most important prognostic factor is early recognition: melioidosis diagnosed and treated promptly with appropriate intravenous antibiotics has far better outcomes than cases treated initially with ineffective agents and corrected only after culture results return days later.
Key Research Papers
- Limmathurotsakul D, et al. Predicted global distribution of Burkholderia pseudomallei and burden of melioidosis. Nat Microbiol. 2016;1:15008. — PubMed PMID: 27571754
- Wiersinga WJ, Virk HS, Torres AG, Currie BJ, Peacock SJ, Dance DAB, Limmathurotsakul D. Melioidosis. Nat Rev Dis Primers. 2018;4:17107. — PubMed PMID: 29388572
- Dance D. Treatment and prophylaxis of melioidosis. Int J Antimicrob Agents. 2014;43(4):310–8. — PubMed PMID: 24613038
- Pitman MC, Luck T, Marshall CS, Anstey NM, Ward L, Currie BJ. Intravenous therapy duration and outcomes in melioidosis: a new treatment paradigm. PLoS Negl Trop Dis. 2015;9(3):e0003586. — PubMed PMID: 25811783
- Anunnatsiri S, Chaowagul W, Teparrukkul P, et al. A comparison between 12 versus 20 weeks of trimethoprim-sulfamethoxazole as oral eradication treatment for melioidosis: an open-label, pragmatic, multicenter, non-inferiority, randomized controlled trial. Clin Infect Dis. 2021;73(11):e3627–e3633. — PubMed PMID: 32725199
- Chetchotisakd P, Chierakul W, Chaowagul W, et al. Trimethoprim-sulfamethoxazole versus trimethoprim-sulfamethoxazole plus doxycycline as oral eradicative treatment for melioidosis (MERTH): a multicentre, double-blind, non-inferiority, randomised controlled trial. Lancet. 2014;383(9919):807–14. — PubMed PMID: 24284287
- White NJ, et al. Halving of mortality of severe melioidosis by ceftazidime. Lancet. 1989;2(8665):697–701. — PubMed PMID: 2570956
- Cheng AC, Currie BJ. Melioidosis: epidemiology, pathophysiology, and management. Clin Microbiol Rev. 2005;18(2):383–416. — PubMed PMID: 15831829
- Currie BJ, et al. The epidemiology and clinical spectrum of melioidosis: 540 cases from the 20 year Darwin prospective study. PLoS Negl Trop Dis. 2010;4(11):e900. — PubMed PMID: 21152057
- Lipsitz R, Garges S, Aurigemma R, et al. Workshop on treatment of and postexposure prophylaxis for Burkholderia pseudomallei and B. mallei infection, 2010. Emerg Infect Dis. 2012;18(12):e2. — PubMed PMID: 23171644
- Petras JK, Elrod MG, Ty MC, et al. Locally acquired melioidosis linked to environment — Mississippi, 2020-2023. N Engl J Med. 2023;389(25):2355–2362. — PubMed PMID: 38118023
- Gee JE, Bower WA, Kunkel A, et al. Multistate outbreak of melioidosis associated with imported aromatherapy spray. N Engl J Med. 2022;386(9):861–868. — PubMed PMID: 35235727
- Schweizer HP. Mechanisms of antibiotic resistance in Burkholderia pseudomallei: implications for treatment of melioidosis. Future Microbiol. 2012;7(12):1389–99. — PubMed PMID: 23231488
- Chierakul W, Winothai W, Wattanawaitunechai C, et al. Melioidosis in 6 tsunami survivors in southern Thailand. Clin Infect Dis. 2005;41(7):982–90. — PubMed PMID: 16142663
- Currie BJ, Fisher DA, Howard DM, Burrow JN. Neurological melioidosis. Acta Trop. 2000;74(2–3):145–51. — PubMed PMID: 10674643
- Peacock SJ. Melioidosis. Curr Opin Infect Dis. 2006;19(5):421–8. — PubMed PMID: 16940864