Laryngeal Cancer
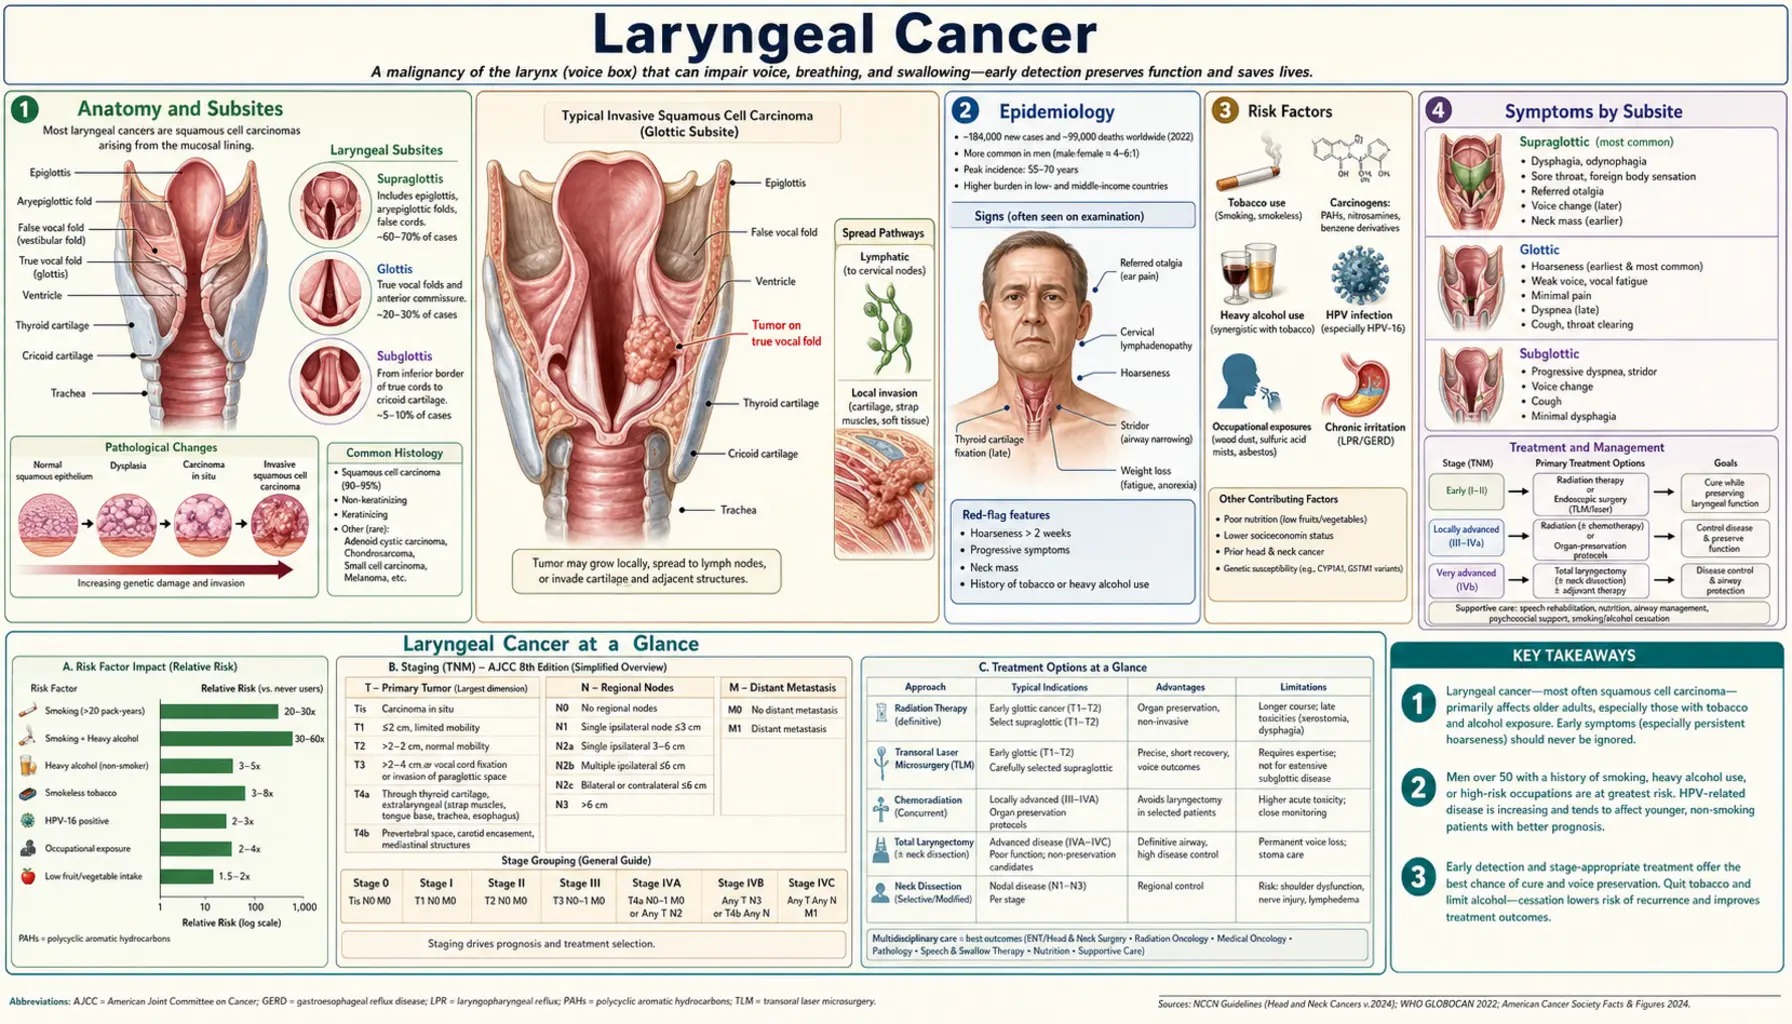
Laryngeal cancer is a malignancy of the larynx — the voice box — situated at the junction of the upper and lower respiratory tracts. Approximately 95% are squamous cell carcinomas (SCC) arising from the mucosal lining. It is the second most common head and neck cancer and a disease strongly linked to tobacco smoking and alcohol use. Unlike oropharyngeal cancer, laryngeal SCC is human papillomavirus-negative in the overwhelming majority of cases. Persistent hoarseness in a current or former smoker is a recognised warning sign: the 2018 American Academy of Otolaryngology–Head and Neck Surgery Foundation (AAO-HNSF) hoarseness guideline calls for a look at the voice box (laryngoscopy) when hoarseness has not cleared or improved within 4 weeks, and sooner when a serious cause is suspected — with a history of tobacco use listed among the reasons to look sooner.
Table of Contents
- Anatomy and Subsites
- Epidemiology
- Risk Factors
- Symptoms by Subsite
- Diagnosis and Workup
- Staging
- Early Glottic Cancer (T1–T2)
- Advanced Disease and Organ Preservation
- The RTOG 91-11 Landmark Trial
- Total Laryngectomy and Voice Rehabilitation
- Supraglottic and Subglottic Cancers
- Treatment of Recurrent and Metastatic Disease
- Key Research Papers
- Featured Videos
Anatomy and Subsites
The larynx is divided into three anatomical subsites, each with distinct lymphatic drainage, clinical behavior, and prognosis:
Glottis
The glottis comprises the true vocal cords (vocal folds) and the anterior and posterior commissures. It is the most common subsite for laryngeal cancer (approximately 60–65% of cases). The vocal cords are unique in having an extremely sparse lymphatic supply, which means that early-stage glottic cancers have a very low rate of lymph node metastasis and can be cured with high rates of success. Any lesion of the vocal cord produces hoarseness at an early stage — a biological advantage because it drives early presentation.
Supraglottis
The supraglottis includes the epiglottis, aryepiglottic folds, arytenoids, and false vocal cords. It accounts for approximately 30–35% of laryngeal cancers. In stark contrast to the glottis, the supraglottis has a rich bilateral lymphatic drainage. Supraglottic cancers therefore tend to present late — often with bulky nodal disease — because they produce no early functional symptom (hoarseness is a late sign when the tumor has extended to the true cords). Patients may first notice dysphagia, odynophagia, a referred otalgia, or a neck mass.
Subglottis
The subglottis is the least common site (<5% of cases), extending from below the true cords to the inferior margin of the cricoid cartilage. Subglottic cancers are rare, spread early to paratracheal and lower jugular lymph nodes, and carry a poorer prognosis because they are often not detected until they obstruct the airway or extend into the trachea.
Epidemiology
In the United States, laryngeal cancer makes up 0.6% of all new cancer cases: the National Cancer Institute’s SEER program estimates 12,290 new cases and 3,960 deaths in 2026, a median age at diagnosis of 67, and a 5-year relative survival of 62.5% (2016–2022). The incidence has declined significantly over the past three decades, largely reflecting reductions in tobacco smoking rates. The male-to-female ratio is approximately 4:1, though the gap is narrowing as smoking rates equalize between genders.
Squamous cell carcinoma accounts for 95–98% of laryngeal malignancies. Rare histologies include adenocarcinoma, neuroendocrine carcinoma (including small cell variants), chondrosarcoma, and lymphoma. Verrucous carcinoma — a well-differentiated, locally invasive variant of SCC — has a distinct biology: it rarely metastasizes but may undergo anaplastic transformation after radiation therapy.
Survival has not improved steadily. A review of 158,426 US laryngeal cancers in the National Cancer Data Base (1985–2001) found that survival fell from the mid-1980s to the mid-1990s, the same period in which treatment shifted from surgery toward chemoradiation (Hoffman and colleagues, 2006). For T3N0M0 tumours treated in 1994–1996, 5-year relative survival was 59.2% after chemoradiation and 42.7% after radiation alone, against 65.2% after surgery with radiation and 63.3% after surgery alone; for the glottic T3N0M0 subset, chemoradiation and surgery with radiation both gave 65.6%. The authors wrote that the fall in survival may be related to the change in treatment patterns and called for further study.
Risk Factors
Tobacco Smoking
Tobacco is the overwhelmingly dominant risk factor, present in approximately 85–90% of patients with laryngeal cancer. Both cigarettes and cigars confer risk proportional to pack-year history. The relative risk of laryngeal cancer in heavy smokers is 10–30 times that of non-smokers. Even light smoking doubles the baseline risk.
Alcohol
Alcohol is an independent risk factor and acts synergistically with tobacco. Heavy alcohol consumption alone (3–4+ drinks per day) increases laryngeal cancer risk approximately 2–3 fold. The combination of heavy smoking and heavy drinking produces a multiplicative risk — estimated at 100-fold relative to non-using controls in some studies — through mechanisms including local acetaldehyde carcinogenesis, impaired folate metabolism, and reduced detoxification of tobacco carcinogens.
Gastroesophageal Reflux Disease (GERD)
Chronic acid and peptic reflux causes laryngopharyngeal irritation and may contribute to malignant transformation, particularly at the posterior commissure and subglottis. The association between laryngopharyngeal reflux and laryngeal cancer risk is supported by epidemiological studies and mechanistic data showing acid-induced upregulation of oncogenic pathways.
Radiation Exposure
Prior therapeutic radiation to the head and neck increases the risk of second primary laryngeal cancers. The latency period is typically 5–20 years after exposure.
Plummer-Vinson Syndrome
This syndrome (iron deficiency anemia, esophageal webs, dysphagia) is associated with increased risk of upper aerodigestive tract squamous cell carcinomas, including larynx and hypopharynx. The mechanism involves mucosal atrophy from nutritional deficiency.
Human Papillomavirus Status
In contrast to oropharyngeal SCC, where human papillomavirus (HPV) (particularly HPV-16) drives a distinct biological subset with favorable prognosis, laryngeal SCC is human papillomavirus-positive in only approximately 5% of cases. Human papillomavirus does not play a significant etiological role in laryngeal cancer, and the dramatic rise in human papillomavirus-positive oropharyngeal cancer seen over the past two decades has not been mirrored in the larynx.
Symptoms by Subsite
Glottic Cancer
Hoarseness is the cardinal and earliest symptom, arising because even small tumors on the vibratory margin of the vocal cord disrupt normal phonation. The 2018 AAO-HNSF hoarseness guideline calls for laryngoscopy when hoarseness fails to clear or improve within 4 weeks, or at any time if a serious cause is suspected; a history of tobacco use is one of the reasons it lists for an earlier look. Early examination matters because glottic cancers detected at T1 stage have cure rates exceeding 90%, while cure rates fall substantially for T3–T4 disease. Late symptoms of glottic cancer include stridor (airway narrowing), dysphagia (deep invasion), and, rarely, a palpable neck mass (late nodal involvement).
Supraglottic Cancer
Supraglottic cancers are silent until large. Early symptoms are non-specific: a persistent sore throat, odynophagia, or dysphagia. Referred otalgia (ear pain from the auricular branch of the vagus nerve, cranial nerve X (CN X), Arnold's nerve) is a classic but often overlooked symptom. A painless neck mass may be the first sign of nodal disease. Hoarseness appears late when the tumor extends down to the cords. Voice change + dysphagia + one-sided ear pain (unilateral otalgia) is a triad that head and neck surgeons treat as a sign for prompt investigation.
Subglottic Cancer
Subglottic cancers are typically asymptomatic until they produce stridor or airway compromise from tracheal encroachment. Hoarseness occurs late when the tumor extends superiorly to involve the cords. Subglottic tumors may present with stridor that mimics asthma, leading to diagnostic delay.
Diagnosis and Workup
Laryngoscopy and Biopsy
Office-based flexible laryngoscopy (using a thin fiberoptic or digital chip endoscope passed through the nostril) provides immediate visualization of the entire larynx and piriform sinuses. Suspicious lesions appear as white (leukoplakia), red (erythroplakia), or exophytic mucosal abnormalities. Definitive diagnosis requires tissue biopsy under general anesthesia via direct laryngoscopy (microlaryngoscopy), which also permits precise mapping of tumor extent.
Stroboscopy
Stroboscopic examination assesses the mucosal wave of the vocal cords. Loss of the mucosal wave over a suspicious lesion suggests subepithelial invasion, which carries higher T-stage implications even when the lesion appears superficially limited.
Computed Tomography Neck and Chest
Contrast-enhanced computed tomography (CT) of the neck defines tumor extent, cartilage invasion (critical for staging), and cervical lymph node involvement. Computed tomography chest is essential to exclude pulmonary metastases and synchronous primary lung cancer — a clinical scenario occurring in approximately 3–5% of patients with laryngeal SCC given the shared tobacco carcinogen exposure.
PET-CT
FDG-PET (fluorodeoxyglucose positron emission tomography)/computed tomography is recommended for staging of locoregionally advanced laryngeal cancer (T3–T4 or N+) to detect occult distant metastases (lung, liver, bone) and identify synchronous primary tumors. PET-CT detects distant metastases in approximately 10–15% of patients with advanced head and neck cancer, influencing treatment intent (curative vs. palliative).
Magnetic Resonance Imaging
Magnetic resonance imaging (MRI) provides superior soft-tissue contrast for assessing pre-epiglottic space invasion, paraglottic space involvement, and cartilage marrow invasion — factors that upstage disease and influence surgical eligibility. It complements computed tomography rather than replacing it.
Staging
Laryngeal cancer is staged by the American Joint Committee on Cancer / Union for International Cancer Control (AJCC/UICC) TNM system (8th edition). Key staging determinants differ by subsite:
- Glottic T1: limited to vocal cord(s) with normal mobility; T1a = one cord, T1b = both cords
- Glottic T2: extension to supra- or subglottis, or impaired cord mobility
- Glottic T3: vocal cord fixation and/or invasion of paraglottic space, minor thyroid cartilage erosion
- Glottic T4a: invasion through thyroid cartilage or extension beyond larynx (trachea, esophagus, strap muscles); T4b = prevertebral space or encases carotid artery
- Supraglottic T1: limited to one subsite with normal mobility
- Supraglottic T2: extends to adjacent supraglottic subsite(s) or glottis or outside supraglottis
Regional lymph node involvement is the single most important prognostic factor, halving 5-year survival in most series. The cervical lymph nodes are classified by level (I–VI), with glottic cancers primarily draining to levels II–IV and supraglottic cancers draining bilaterally.
Early Glottic Cancer (T1–T2)
Early-stage glottic cancer is one of the most curable solid tumors. Two treatment modalities offer equivalent oncological control with different trade-offs:
Radiation Therapy (Definitive)
External beam radiation therapy (RT) delivers approximately 63–70 Gy (gray, the unit of radiation dose) in 30–35 fractions to the larynx over 6–7 weeks. Local control rates for T1 glottic cancer are 85–94% with RT alone. In a Dutch population-based series of 316 consecutive patients irradiated for T1 glottic cancer (Sjögren and colleagues, 2009), local control was 86% at 5 years and 84% at 10 years, and disease-specific survival was 97% at both 5 and 10 years; pre-existing hypertrophic laryngitis (long-standing thickening of the vocal-cord lining) was the only factor that predicted local failure, tripling its risk (relative risk 3.0). The key advantage is voice preservation with normal vocal cord anatomy — many patients retain near-normal voice quality. The larynx is irradiated as the primary organ, and radiation reactions (edema, mucositis) are manageable. Late complications include laryngeal fibrosis (<5%), hypothyroidism (from incidental thyroid irradiation), and a low risk of carotid stenosis and secondary malignancy over decades.
Transoral Laser Microsurgery (TLM)
CO2 laser resection of vocal cord tumors through a microlaryngoscope provides excellent local control (85–95% for T1 lesions) with minimal morbidity, same-day or overnight hospital stay, and rapid recovery. Voice quality after TLM depends on the depth of resection: superficial lesions can be resected with excellent voice outcomes, while deep resection involving the vocal ligament produces a hoarse or rough voice.
The choice between RT and TLM for early glottic cancer is made in multidisciplinary tumor board discussion, weighing the patient's baseline voice quality, tumor location (anterior commissure involvement is a risk factor for worse outcomes with both modalities), need for preservation of surgical options, and patient preference. Both options offer high cure rates exceeding 90% for T1N0 disease.
Advanced Disease and Organ Preservation
Locally advanced laryngeal cancer (T3–T4a, or any T with node-positive disease) historically required total laryngectomy. The pivotal VA Laryngeal Cancer Study Group trial (1991) and subsequent studies established that organ-preservation strategies using chemoradiation can achieve equivalent survival. In the VA trial, 332 patients were randomly assigned to induction chemotherapy (cisplatin and fluorouracil) followed by radiation, or to laryngectomy followed by radiation. Estimated 2-year survival was 68% in both groups; 36% of the chemotherapy group eventually needed a total laryngectomy, and the larynx was preserved in 64% of patients. The chemotherapy group had more local recurrences but fewer distant metastases.
Current standard of care for T3–T4a laryngeal cancer without frank cartilage destruction or airway compromise is organ-preservation chemoradiation, with total laryngectomy reserved as salvage for treatment failure or for patients with disease not amenable to organ preservation (e.g., extensive cartilage invasion, poor baseline laryngeal function).
For tumours treated with surgery first, a newer approach adds immunotherapy. The KEYNOTE-689 trial (2025) randomly assigned 714 people with locally advanced head and neck squamous-cell cancer, the cancer type that includes laryngeal SCC, to standard care (surgery, then radiation with or without cisplatin) with or without the immune-checkpoint drug pembrolizumab given before and after surgery. Event-free survival at 36 months was 57.6% vs 46.4% in all participants, and 59.8% vs 45.9% in those whose tumours had a high level of the PD-L1 marker (combined positive score 10 or more). About 88% of each group completed surgery, so the drug given beforehand did not stop operations going ahead; severe (grade 3 or higher) immune-related side effects occurred in 10.0% of the pembrolizumab group.
The RTOG 91-11 Landmark Trial
The RTOG 91-11 trial, run by the Radiation Therapy Oncology Group (RTOG), is the most influential randomized controlled trial in laryngeal cancer management. It enrolled 547 patients with stage III–IV resectable laryngeal cancer and compared three arms:
- Induction chemotherapy (cisplatin + fluorouracil, 5-FU) followed by RT (sequential)
- Concurrent chemoradiation (cisplatin 100 mg/m² every 3 weeks during RT)
- Radiation therapy alone
Key results from the 2003 report (Forastiere and colleagues, median follow-up 3.8 years):
- Larynx preservation at 2 years: concurrent chemoRT 88% vs sequential 75% (P=0.005) vs RT alone 70% (P<0.001)
- Locoregional control was significantly superior with concurrent chemoRT (78% vs 61% sequential and 56% RT alone)
- Overall survival was similar across all three arms — the trial was not powered to detect survival differences
- Toxicity was highest in the concurrent arm, including mucositis and dysphagia
RTOG 91-11 established concurrent cisplatin-based chemoradiation as the standard of care for larynx-preserving treatment of locoregionally advanced resectable laryngeal cancer. The induction chemotherapy arm (sequential) remained an acceptable alternative, particularly in patients where downstaging before RT is desired.
The long-term report of RTOG 91-11 (Forastiere and colleagues, 2013; 520 patients analysed, median follow-up 10.8 years) found that both chemotherapy arms improved laryngectomy-free survival compared with RT alone, and concurrent chemoRT still gave the best larynx preservation. Overall survival did not differ significantly, though it leaned worse with concurrent than with induction chemotherapy (hazard ratio 1.25, P=0.08). The trial found no difference in recorded late effects, but deaths not attributed to larynx cancer or its treatment were higher with concurrent chemotherapy (30.8%, vs 20.8% with induction chemotherapy and 16.9% with RT alone). The cause of this excess was not established; late swallowing and airway problems are one proposed explanation. This has tempered enthusiasm for concurrent chemoRT in elderly patients or those with pre-existing dysphagia, and reinforced the need for careful patient selection and long-term functional monitoring.
Total Laryngectomy and Voice Rehabilitation
Total laryngectomy (TL) removes the entire larynx — including the epiglottis, thyroid cartilage, cricoid, and several tracheal rings — and creates a permanent tracheostoma in the neck. The pharynx is reconstructed primarily or with a free flap. TL permanently separates the respiratory and digestive tracts; the patient breathes through the stoma and has no risk of aspiration.
Despite the functional implications, total laryngectomy provides excellent locoregional control (90%+ for appropriately selected disease) and is the option head and neck surgeons generally describe for:
- T4a tumors with frank cartilage destruction through the outer cortex
- Tumors invading the thyroid gland or cricoid cartilage
- Patients with pre-treatment aspiration or poor laryngeal function
- Salvage after failed chemoradiation (post-radiation TL carries a 20–30% pharyngocutaneous fistula rate)
Voice Rehabilitation After Total Laryngectomy
Loss of the larynx eliminates phonation. Three main voice rehabilitation options exist:
- Tracheoesophageal prosthesis (TEP/voice prosthesis): a one-way silicone valve inserted in a surgically created tracheoesophageal puncture (TEP), placed at the time of laryngectomy or as a secondary procedure. The patient occludes the stoma and diverts pulmonary air through the prosthesis into the esophagus, generating a pseudo-voice. This produces the best voice quality (conversational-level volume, natural inflection) and is the preferred method when feasible. Prosthesis maintenance (cleaning, replacement every 3–6 months) requires ongoing commitment.
- Electrolarynx: a battery-powered device held against the neck or cheek that vibrates the pharyngeal soft tissues. Produces a robotic, monotone quality but is easy to use immediately post-operatively. Valuable as a backup or primary option in patients unable to use TEP.
- Esophageal speech: the patient learns to inject air into the esophagus and expel it in a controlled belch, vibrating the pharyngoesophageal (PE) segment. The best-quality hands-free voice, but very difficult to learn and achieved by only 20–30% of patients.
Supraglottic and Subglottic Cancers
Supraglottic Cancer Management
For early supraglottic cancer (T1–T2, N0), both supraglottic laryngectomy (partial laryngectomy preserving the true cords) and radiation therapy offer comparable local control. Supraglottic laryngectomy requires a functioning larynx and an ability to tolerate aspiration during swallowing rehabilitation; it is contraindicated in patients with poor pulmonary reserve. Elective bilateral neck treatment (irradiation or selective neck dissection of levels II–IV) is standard given the bilateral lymphatic drainage.
For advanced supraglottic cancer (T3–T4), concurrent chemoradiation (following RTOG 91-11 principles) or total laryngectomy with neck dissection and adjuvant (chemo)radiation are the primary options.
Subglottic Cancer Management
Subglottic cancers are rare and carry a poor prognosis due to late presentation and early paratracheal nodal spread. Treatment typically requires total laryngectomy with paratracheal and superior mediastinal lymph node dissection, followed by adjuvant radiation. The role of concurrent chemoradiation alone is less well-defined due to small patient numbers.
Treatment of Recurrent and Metastatic Disease
When head and neck squamous-cell cancer, the group to which laryngeal SCC belongs, comes back or spreads after platinum chemotherapy, the outlook is poor and options are limited. The CheckMate 141 trial (Ferris and colleagues, 2016) enrolled 361 people whose cancer had progressed within 6 months of platinum-based chemotherapy and compared the immune-checkpoint drug nivolumab with a standard single drug (methotrexate, docetaxel or cetuximab). Median survival was 7.5 months with nivolumab vs 5.1 months with standard therapy, and 1-year survival was 36.0% vs 16.6%. Severe (grade 3 or 4) treatment-related side effects occurred in 13.1% of the nivolumab group vs 35.1% of the standard-therapy group, and physical, role and social functioning stayed stable on nivolumab while it worsened on standard therapy.
Key Research Papers
- The Department of Veterans Affairs Laryngeal Cancer Study Group. Induction chemotherapy plus radiation compared with surgery plus radiation in patients with advanced laryngeal cancer. N Engl J Med. 1991;324(24):1685–1690. — PubMed PMID: 2034244
- Forastiere AA, Zhang Q, Weber RS, et al. Long-term results of RTOG 91-11: a comparison of three nonsurgical treatment strategies to preserve the larynx in patients with locally advanced larynx cancer. J Clin Oncol. 2013;31(7):845–852. — PubMed PMID: 23182993
- Mendenhall WM, Werning JW, Hinerman RW, Amdur RJ, Villaret DB. Management of T1-T2 glottic carcinomas. Cancer. 2004;100(9):1786–1792. — PubMed PMID: 15112257
- Steiner W, Ambrosch P, Rödel RM, Kron M. Impact of anterior commissure involvement on local control of early glottic carcinoma treated by laser microresection. Laryngoscope. 2004;114(8):1485–1491. — PubMed PMID: 15280731
- Bussu F, Paludetti G, Almadori G, et al. Comparison of total laryngectomy with surgical (cricohyoidopexy) and nonsurgical organ-preservation modalities in advanced laryngeal squamous cell carcinomas: a multicenter retrospective analysis. Head Neck. 2013;35(4):554–561. — PubMed PMID: 22495830
- Sjögren EV, Wiggenraad RG, Le Cessie S, Snijder S, Pomp J, Baatenburg de Jong RJ. Outcome of radiotherapy in T1 glottic carcinoma: a population-based study. Eur Arch Otorhinolaryngol. 2009;266(5):735–744. — PubMed PMID: 18839197
- Hoffman HT, Porter K, Karnell LH, et al. Laryngeal cancer in the United States: changes in demographics, patterns of care, and survival. Laryngoscope. 2006;116(9 Pt 2 Suppl 111):1–13. — PubMed PMID: 16946667
- Ang KK, Harris J, Wheeler R, et al. Human papillomavirus and survival of patients with oropharyngeal cancer. N Engl J Med. 2010;363(1):24–35. — PubMed PMID: 20530316
- Ferris RL, Blumenschein G Jr, Fayette J, et al. Nivolumab for recurrent squamous-cell carcinoma of the head and neck. N Engl J Med. 2016;375(19):1856–1867. — PubMed PMID: 27718784
- Pfister DG, Spencer S, Adelstein D, et al. Head and neck cancers, version 2.2020, NCCN Clinical Practice Guidelines in Oncology. J Natl Compr Canc Netw. 2020;18(7):873–898. — PubMed PMID: 32634781
- Forastiere AA, Goepfert H, Maor M, et al. Concurrent chemotherapy and radiotherapy for organ preservation in advanced laryngeal cancer. N Engl J Med. 2003;349(22):2091–2098. — PubMed PMID: 14645636
- Stachler RJ, Francis DO, Schwartz SR, et al. Clinical Practice Guideline: Hoarseness (Dysphonia) (Update) Executive Summary. Otolaryngol Head Neck Surg. 2018;158(3):409–426. — PubMed PMID: 29494316
- Uppaluri R, Haddad RI, Tao Y, et al. Neoadjuvant and adjuvant pembrolizumab in locally advanced head and neck cancer. N Engl J Med. 2025;393(1):37–50. — PubMed PMID: 40532178
PubMed Topic Searches
The following PubMed topic searches retrieve current peer-reviewed literature on Laryngeal Cancer.
- PubMed: Laryngeal cancer treatment outcomes
- PubMed: Laryngeal organ preservation chemoradiation
- PubMed: Glottic cancer radiation vs laser
- PubMed: Total laryngectomy voice prosthesis
- PubMed: RTOG 91-11 larynx cisplatin trial
- PubMed: Supraglottic cancer surgery radiation
- PubMed: Laryngeal cancer tobacco alcohol risk
- PubMed: Laryngeal cancer staging cartilage invasion