SAM-e (S-Adenosylmethionine)
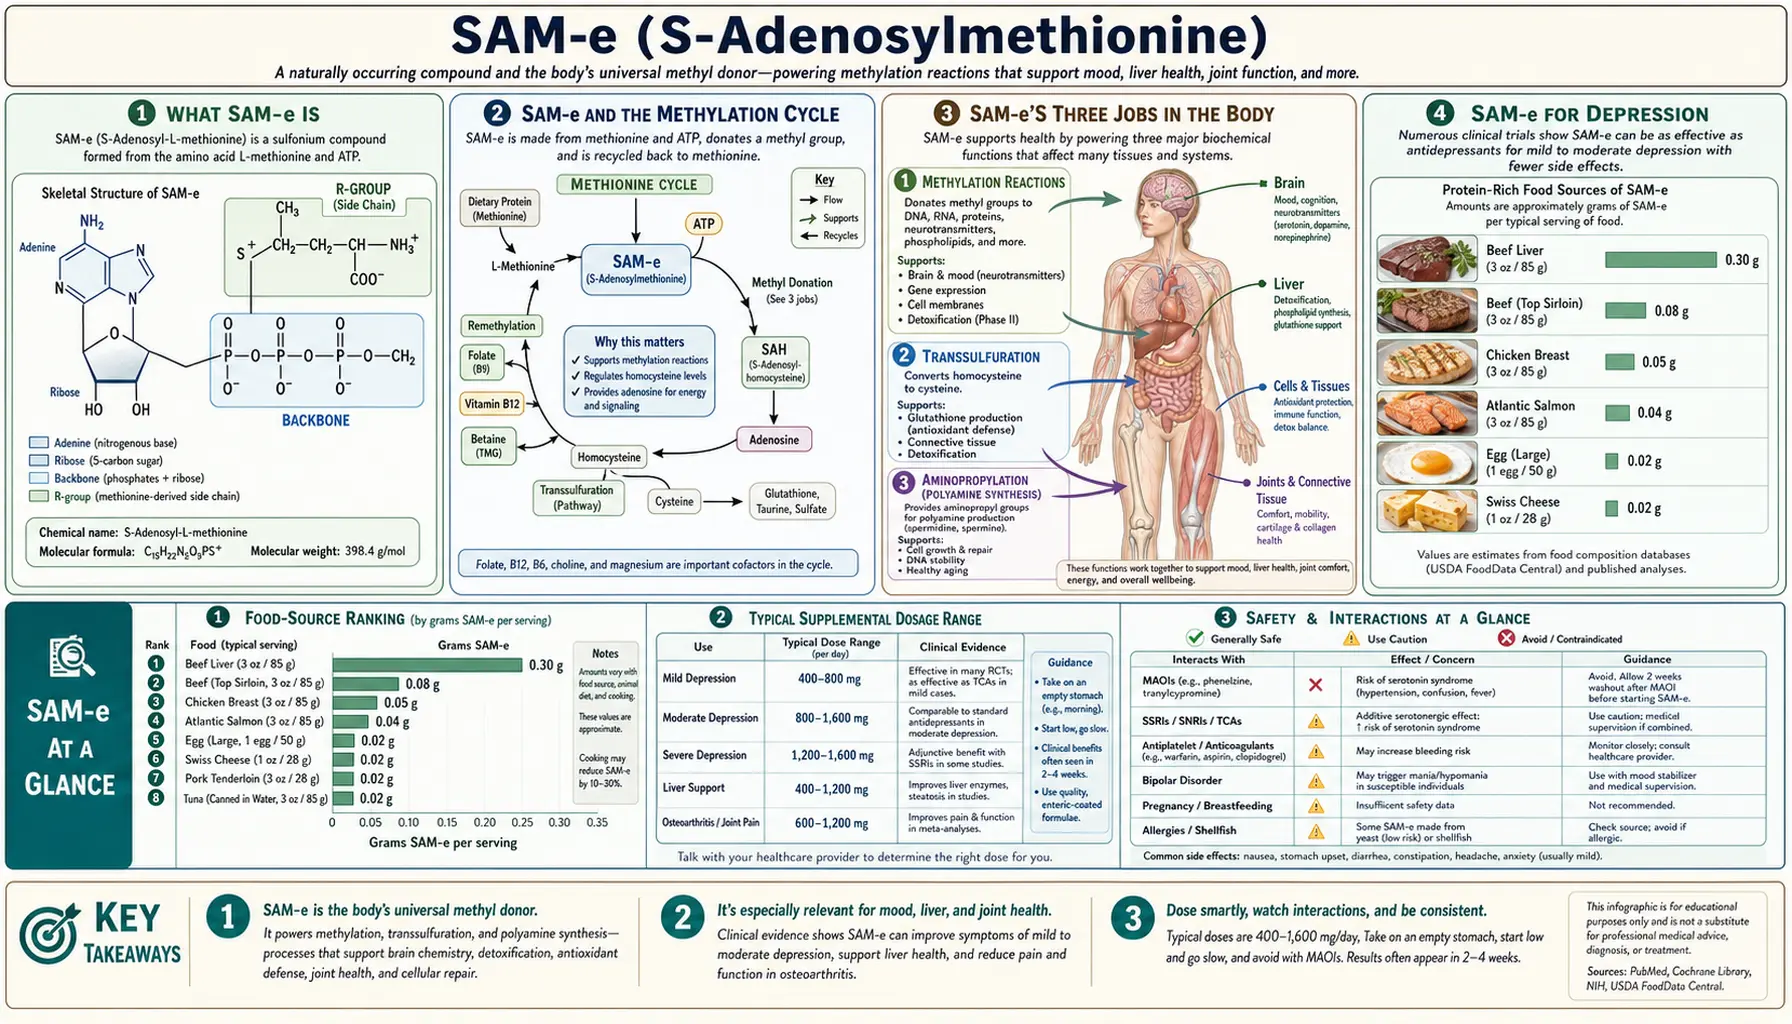
SAM-e (pronounced "sammy," short for S-adenosylmethionine) is a molecule your body makes on its own, around the clock, from the amino acid methionine and the cellular energy carrier adenosine triphosphate (ATP). It is not something you eat directly in any meaningful amount — it is manufactured inside your cells and used almost immediately. Its role is unusually central: SAM-e is the body's universal methyl donor, the chemical that hands off a small carbon group needed to build brain chemicals, protect cell membranes, regulate genes, and keep cartilage and the liver healthy. Because it sits at such a busy crossroads, SAM-e became one of the more heavily tested supplements, with clinical trials in depression, osteoarthritis, and certain liver conditions. It also carries a few real cautions that matter, especially for anyone with bipolar disorder or taking antidepressants. This page explains what SAM-e actually is, the biochemistry in plain language, what the research honestly shows, and how it is used.
Table of Contents
What SAM-e Is
SAM-e is a naturally occurring compound found in every living cell. Chemically, it is methionine — one of the essential amino acids from the protein you eat — joined to adenosine, a piece borrowed from adenosine triphosphate, the molecule cells use to carry energy. That combination is made by an enzyme called methionine adenosyltransferase (MAT). The reaction is expensive: to build one molecule of SAM-e, a cell spends a whole molecule of adenosine triphosphate, which is unusual and tells you how important the product is.
The critical thing to understand is that SAM-e is essentially an internal molecule. Unlike a vitamin or a mineral, you do not get useful amounts of SAM-e from food — it is too unstable to survive digestion in quantity. Your body instead synthesizes all the SAM-e it needs, and it makes a great deal of it: an adult produces and uses several grams of SAM-e every single day, recycling the same building blocks over and over. The liver is the busiest producer, accounting for a large share of the body's total.
What makes SAM-e special is the chemical group it carries: a methyl group — a single carbon atom with three hydrogens attached (–CH₃). SAM-e holds this methyl group in a "high-energy" state, loosely enough that it can be handed off to hundreds of different molecules. Chemists call SAM-e the principal biological methyl donor. When you hear the word "methylation" in nutrition or genetics, SAM-e is almost always the molecule doing the donating. That single job — giving away methyl groups — ripples outward into mood, joint health, liver function, and the switching on and off of genes.
Because the supply of SAM-e depends on the supply of methionine (from dietary protein) and on the B-vitamins that keep the surrounding chemistry running, SAM-e sits at the center of a small, elegant loop that is worth understanding.
SAM-e and the Methylation Cycle
SAM-e is one station on a continuous chemical loop that biochemists call the methylation cycle (or the methionine cycle). Following it once explains most of what SAM-e does and, importantly, why your B-vitamin status matters so much.
The loop runs in four steps:
- Methionine → SAM-e. The amino acid methionine combines with adenosine triphosphate to become SAM-e. SAM-e is now "loaded," carrying its transferable methyl group.
- SAM-e → SAH. SAM-e donates that methyl group to some target molecule — a neurotransmitter, a stretch of DNA, a membrane fat, and so on. Having given away its methyl group, SAM-e becomes S-adenosylhomocysteine, or SAH.
- SAH → homocysteine. SAH is quickly broken down, releasing homocysteine — the same homocysteine measured on some lab panels as a marker of cardiovascular and metabolic health.
- Homocysteine → back to methionine (or onward). Homocysteine can be re-methylated back into methionine, closing the loop so the whole cycle can run again.
That last step is where the B-vitamins come in, and it is the reason a page about an amino-acid-derived molecule keeps mentioning vitamins. To turn homocysteine back into methionine, the body needs a fresh methyl group, which it gets from folate (vitamin B9, in its active 5-methyl-tetrahydrofolate form) using vitamin B12 as an essential helper for the enzyme that does the transfer. A second, backup route uses betaine, a substance the body makes from choline. If folate or B12 run short, homocysteine cannot be efficiently recycled: it builds up, methionine regeneration slows, and the cell's ability to keep making SAM-e can falter.
This interlock is why low B12 or low folate can look, chemically, like a SAM-e problem — and why depression linked to B-vitamin deficiency, high homocysteine, and low SAM-e tend to cluster together in the research. It is also why some clinicians who use SAM-e recommend making sure folate, B12, and vitamin B6 are adequate first, so the cycle has what it needs to keep turning. If you are curious about your own numbers, the homocysteine blood test is the standard window into how well this cycle is running.
SAM-e's Three Jobs in the Body
SAM-e branches into three distinct chemical pathways. Each one is the reason for a specific supplement use, so it is worth taking them one at a time.
1. Methylation — building brain chemicals and membranes
This is SAM-e's headline role and the one behind its use for mood. As the universal methyl donor, SAM-e supplies the methyl group for a long list of reactions, including:
- Neurotransmitters. The making and breaking-down of dopamine, norepinephrine, and serotonin all involve methylation steps that draw on SAM-e. Melatonin, the sleep hormone, is also produced through a SAM-e-dependent methylation. This chemistry is the plausible basis for SAM-e's antidepressant effects.
- Cell membranes. SAM-e helps convert one membrane fat (phosphatidylethanolamine) into another (phosphatidylcholine), which keeps cell membranes fluid and healthy — a process especially important in the liver and in nerve cells.
- Genes (DNA and histones). Adding methyl groups to DNA is one of the main ways the body switches genes on and off without changing the underlying code — the field known as epigenetics. SAM-e is the methyl source for this, linking nutrition to gene regulation.
- Creatine. A large share of the body's daily methylation is spent making creatine for muscle energy, again with SAM-e as the donor.
2. Transsulfuration — making glutathione (antioxidant defense)
The homocysteine produced downstream of SAM-e does not have to loop back to methionine. It can instead be pushed forward down a route called transsulfuration, which converts it (via cystathionine) into the amino acid cysteine. Cysteine is the rate-limiting ingredient for glutathione, the body's master antioxidant and the liver's main tool for neutralizing toxins. This branch requires vitamin B6 as a cofactor. It explains a good part of SAM-e's interest in liver disease: healthy SAM-e levels support glutathione production, and glutathione protects liver cells from oxidative damage.
3. Aminopropylation — polyamines, cartilage, and cell growth
SAM-e has a third, less-famous trick. After being decarboxylated, it can donate a different chemical group (an aminopropyl group) to build molecules called polyamines (spermidine and spermine), which cells need for growth, repair, and DNA stabilization. This pathway is invoked to explain SAM-e's effect on joint cartilage: SAM-e appears to support the cartilage cells (chondrocytes) that manufacture the proteoglycan cushioning of a joint, which is the rationale behind its use in osteoarthritis.
Three jobs, three supplement stories: methylation drives the depression research, transsulfuration underlies the liver work, and aminopropylation supports the osteoarthritis use. All three trace back to the same molecule.
SAM-e for Depression
Depression is SAM-e's most-studied use, and the evidence is genuinely more substantial than for the vast majority of supplements — though it is not without gaps, and honesty requires laying out both sides.
The case in favor. SAM-e has been tested against depression since the 1970s, first in Europe (where an injectable form was used in hospitals) and later as an oral supplement. A 2016 Cochrane review gathered eight of these trials (934 adults): SAM-e performed similarly to the older tricyclic antidepressant imipramine, and as an add-on to a prescription antidepressant it did better than placebo in one trial. Two findings are especially interesting to patients:
- As an add-on to standard antidepressants. A well-designed 2010 randomized trial found that adding SAM-e (800 mg twice daily) to a selective serotonin reuptake inhibitor in people who had not responded to the selective serotonin reuptake inhibitor (SSRI) alone produced meaningfully higher response and remission rates than adding a placebo. This "augmentation" use — SAM-e alongside a prescription antidepressant, as in that trial — is one of its most practical and best-supported applications.
- As a stand-alone option. Some head-to-head trials have compared SAM-e directly with prescription antidepressants such as escitalopram, generally finding it in the same ballpark, which is why clinician-oriented reviews list it as a reasonable option for people who cannot tolerate conventional drugs.
The honest caveats. The 2016 Cochrane systematic review — the most rigorous kind — found that, used on its own, SAM-e showed no strong evidence of a difference from placebo (two trials, very low-quality evidence), while it performed similarly to the antidepressants imipramine and escitalopram (low-quality evidence); only the single add-on trial favoured SAM-e over placebo. The reviewers found no high-quality evidence, could not draw firm conclusions, and called for large, well-designed trials. The trials recorded two reports of mania or hypomania among 441 people taking SAM-e. In other words: plausible and backed by real biochemistry, but the trial evidence is still low in quality and is not the replicated evidence a prescription drug must clear. SAM-e also acts as an activating antidepressant, which is central to its most important safety warning (see Safety).
In short: the strongest trial result for SAM-e in depression is as an add-on to an SSRI antidepressant (one trial of 73 people), and the Cochrane reviewers rated the evidence overall as low to very low in quality.
SAM-e for Osteoarthritis (Joint Pain)
The second well-studied use is osteoarthritis, the common "wear-and-tear" arthritis in which the cartilage cushioning a joint gradually breaks down, causing pain and stiffness in knees, hips, and hands.
The case in favor. Beginning in the 1980s, a series of clinical trials compared SAM-e head-to-head with anti-inflammatory painkillers such as ibuprofen, naproxen, and celecoxib. The recurring result was striking: SAM-e produced pain relief and functional improvement comparable to the nonsteroidal anti-inflammatory drugs (NSAIDs), but with noticeably fewer side effects — particularly fewer of the stomach and gut problems that limit long-term nonsteroidal anti-inflammatory drug (NSAID) use. A 2004 double-blind trial comparing SAM-e (1,200 mg/day) with celecoxib captured the trade-off nicely: celecoxib relieved pain faster in the first month, but by the second month SAM-e had caught up and the two were equally effective. That points to SAM-e's main practical drawback for joints: a slower onset. It is not a fast painkiller — benefits typically build over several weeks — so it suits chronic, ongoing joint pain rather than acute flare-ups.
The mechanism fits: through its aminopropylation pathway, SAM-e appears to support the cartilage-making chondrocytes and may have mild anti-inflammatory effects of its own.
The honest caveats. A 2009 Cochrane review looked critically at the trials that compared SAM-e with placebo in knee or hip osteoarthritis. It found four trials (656 patients), all of poor methodological quality. The difference in pain between SAM-e and placebo was small and not statistically significant — about 0.4 cm on a 10 cm pain scale. The reviewers judged the evidence inconclusive, called for adequately sized trials, and concluded that in the meantime "routine use of SAMe should not be advised." So the picture is mixed: the head-to-head trials against anti-inflammatory painkillers were encouraging and showed fewer stomach side effects, while the placebo-controlled trials were few, small, and poor in quality. Where a benefit was found, it built slowly, over weeks rather than days.
SAM-e for Liver Conditions
SAM-e's third evidence area is the liver — fitting, because the liver is where the body makes most of its SAM-e in the first place. In several chronic liver diseases, the enzyme that produces SAM-e works poorly, so liver SAM-e levels drop, which in turn starves the liver of the glutathione it needs to protect itself. Restoring SAM-e is therefore a logical therapy, and in a number of countries (notably in parts of Europe and Asia) prescription SAM-e — sometimes given by injection — is used clinically for liver problems.
The clearest use is intrahepatic cholestasis, a condition in which bile flow within the liver slows or stalls, causing bile components to back up into the bloodstream (bringing itching, jaundice, and abnormal liver tests). This includes intrahepatic cholestasis of pregnancy (ICP), a distressing late-pregnancy condition of intense itching and elevated bile acids. SAM-e has been used, often alongside the better-established drug ursodeoxycholic acid, to try to improve bile flow and relieve symptoms. Reviews and meta-analyses suggest SAM-e can improve some biochemical markers (such as bilirubin and liver enzymes) in cholestatic liver disease.
The honest caveats. Two limits are important. First, a 2015 meta-analysis of 12 randomized trials (705 patients) in chronic liver disease found differences in total bilirubin and in the liver enzyme AST, but no trial found a difference in the liver enzyme ALT; ursodeoxycholic acid and another drug (stronger neo-minophagen C) were more effective than SAM-e in certain chronic liver diseases, and the authors wrote that SAM-e "demonstrated limited clinical value" in some of them. A 2012 clinical review reached a similar "biologically plausible, some benefit, but robust randomized evidence still limited" conclusion. Second, for cholestasis of pregnancy specifically, a 2013 Cochrane review found that ursodeoxycholic acid relieved itching better than SAM-e, that SAM-e combined with ursodeoxycholic acid did no better than ursodeoxycholic acid alone (one trial), and that there is insufficient evidence that SAM-e is effective for this condition. The bottom line: SAM-e is a prescription liver therapy in some countries, with a sound rationale but limited trial support. Cholestasis of pregnancy has been linked to harm to both mother and baby, and yellowing of the skin or eyes (jaundice) is a sign of liver trouble that hospitals treat as urgent.
Safety and Warnings
SAM-e is generally well tolerated by most people, and it has a long track record. Most side effects are mild and dose-related. But it carries two warnings that are genuinely important, and those deserve top billing.
The bipolar warning (most important)
Because SAM-e acts as an activating antidepressant, it can push mood upward — and in a person with bipolar disorder, that upward push can tip into mania or hypomania (a dangerous, over-elevated, agitated, sleepless, impulsive state). There are documented reports of exactly this: the 2016 Cochrane review recorded two reports of mania or hypomania among 441 people taking SAM-e in depression trials. For people with bipolar disorder, or a strong family history of it, this is the single most important safety fact about SAM-e.
Serotonin syndrome (with antidepressants)
Because SAM-e influences serotonin-related chemistry, combining it with medications that also raise serotonin — selective serotonin reuptake inhibitors (SSRIs), serotonin-norepinephrine reuptake inhibitors (SNRIs), monoamine oxidase inhibitors (MAOIs), tramadol, triptan migraine drugs, or St. John's Wort — raises a concern about serotonin syndrome, a potentially serious reaction of agitation, rapid heartbeat, high temperature, tremor, and confusion. A 1993 published case report described a toxic interaction between SAM-e and the antidepressant clomipramine. In the 2010 add-on trial, 73 people took SAM-e or placebo for six weeks alongside the serotonin reuptake inhibitor antidepressant they were already taking, and drop-outs due to side effects did not differ significantly (5.1% with SAM-e versus 8.8% with placebo).
Common side effects and other cautions
- Digestive upset — nausea, gas, diarrhea, or an upset stomach, especially when starting or at higher doses.
- Insomnia, restlessness, anxiety, or headache — a consequence of SAM-e being activating; this is why it is usually taken in the morning rather than the evening.
- Homocysteine. SAM-e metabolism generates homocysteine as a by-product. Recycling it efficiently depends on adequate folate, B12, and B6; some clinicians pair SAM-e with a B-complex for this reason.
- Parkinson's disease. In theory, SAM-e's methylation activity could interfere with levodopa, the main Parkinson's medicine.
- Pregnancy and breastfeeding. Prescription SAM-e is used for cholestasis of pregnancy in some countries as part of hospital care. The research described on this page does not cover everyday over-the-counter use during pregnancy or breastfeeding.
- Surgery. Because SAM-e acts on the nervous system, a commonly listed precaution is stopping it a couple of weeks before scheduled surgery and telling the anesthesiologist about it.
None of this makes SAM-e a dangerous molecule — for a healthy person without bipolar disorder and not on serotonergic drugs, it is one of the better-tolerated supplements. But the bipolar and antidepressant-interaction points are real, not boilerplate, and they are the two safety facts that matter most with SAM-e.
Using SAM-e: Forms, Dosing & Practical Tips
SAM-e has a few real-world quirks that separate a good product and routine from a wasted one.
Stability and enteric coating
SAM-e is a chemically unstable molecule — it degrades with exposure to heat, moisture, and air, and it breaks down in stomach acid. Two practical consequences follow. First, SAM-e tablets are usually enteric-coated (coated to survive the stomach and dissolve in the intestine, where SAM-e is absorbed); loose powder or uncoated tablets can lose much of their SAM-e before it is absorbed. Second, freshness and packaging matter: SAM-e is commonly sold in individually sealed blister packs rather than a big open bottle, and it keeps best somewhere cool and dry. The more stable salt forms (SAM-e is usually sold as the "butanedisulfonate" or "tosylate" salt) hold up better. This instability is also part of why SAM-e is relatively expensive compared with everyday supplements — a genuine downside worth budgeting for, since effective doses are not small.
Taking it on an empty stomach
SAM-e is absorbed best on an empty stomach — typically 30–60 minutes before a meal. Taking it with food can blunt absorption. The trade-off is that an empty stomach can worsen nausea in sensitive people; a slow build-up of the dose (see below) is the usual way around this.
Typical dosing ranges
Doses in the research vary by use. These are the general ranges reported in studies, not a personal prescription; the safety facts above apply to all of them:
- Depression: commonly 800–1,600 mg per day, usually split into two doses (for example, the 800 mg-twice-daily regimen used in the selective serotonin reuptake inhibitor-augmentation trial).
- Osteoarthritis: commonly 600–1,200 mg per day, with benefits building over several weeks rather than days.
- Liver conditions: higher doses are used in hospital and clinic care, sometimes by drip into a vein (intravenous).
Starting low and building up. A widely used approach is to begin at the lower end (or even 200–400 mg) for the first several days and increase gradually. This "titration" reduces the nausea, anxiety, and jitteriness that a full dose can cause out of the gate, and it shows the lowest amount that works. Because SAM-e is activating, the day's dose — or the larger share of a split dose — is usually taken in the morning to protect sleep. People usually allow a couple of weeks for mood and several weeks for joints before judging whether it is helping.
Key Research Papers
- Lu SC. S-Adenosylmethionine. The International Journal of Biochemistry & Cell Biology. 2000;32(4):391–395. — A concise overview of SAM-e as the body's principal methyl donor and its central place in methylation, transsulfuration, and aminopropylation. — doi:10.1016/S1357-2725(99)00139-9
- Bottiglieri T. S-Adenosyl-L-methionine (SAMe): from the bench to the bedside — molecular basis of a pleiotropic molecule. The American Journal of Clinical Nutrition. 2002;76(5):1151S–1157S. — A foundational review connecting SAM-e biochemistry to its clinical uses in mood, liver, and joints. — doi:10.1093/ajcn/76.5.1151S
- Selhub J. Homocysteine metabolism. Annual Review of Nutrition. 1999;19(1):217–246. — The classic account of the methionine/homocysteine cycle, explaining why folate, B12, and B6 status governs SAM-e regeneration. — doi:10.1146/annurev.nutr.19.1.217
- Papakostas GI, Mischoulon D, Shyu I, Alpert JE, Fava M. S-adenosyl methionine (SAMe) augmentation of serotonin reuptake inhibitors for antidepressant nonresponders with major depressive disorder: a double-blind, randomized clinical trial. American Journal of Psychiatry. 2010;167(8):942–948. — The key trial showing SAM-e added to an SSRI improved response and remission in people who had not responded to the SSRI alone. — doi:10.1176/appi.ajp.2009.09081198
- Sarris J, Papakostas GI, Vitolo O, Fava M, Mischoulon D. S-adenosyl methionine (SAMe) versus escitalopram and placebo in major depression RCT: efficacy and effects of histamine and carnitine as moderators of response. Journal of Affective Disorders. 2014;164:76–81. — A head-to-head randomized comparison of SAM-e against a standard antidepressant and placebo. — doi:10.1016/j.jad.2014.03.041
- Galizia I, Oldani L, Macritchie K, et al. S-adenosyl methionine (SAMe) for depression in adults. Cochrane Database of Systematic Reviews. 2016;(10):CD011286. — The rigorous systematic review of eight trials (934 adults): used alone, no strong evidence of a difference from placebo; similar to imipramine and escitalopram; one add-on trial favoured SAM-e; evidence of low to very low quality; two reports of mania or hypomania among 441 people on SAM-e. — doi:10.1002/14651858.CD011286.pub2
- Sharma A, Gerbarg P, Bottiglieri T, et al. S-Adenosylmethionine (SAMe) for neuropsychiatric disorders: a clinician-oriented review of research. The Journal of Clinical Psychiatry. 2017;78(6):e656–e667. — A practical review summarizing the mood evidence and safety considerations for clinicians. — doi:10.4088/JCP.16r11113
- Rutjes AWS, Nüesch E, Reichenbach S, Jüni P. S-Adenosylmethionine for osteoarthritis of the knee or hip. Cochrane Database of Systematic Reviews. 2009;(4):CD007321. — Four placebo-controlled trials (656 patients) of poor quality; a small, non-significant pain difference; judged inconclusive, with routine use not advised meanwhile. — doi:10.1002/14651858.CD007321.pub2
- Najm WI, Reinsch S, Hoehler F, Tobis JS, Harvey PW. S-adenosyl methionine (SAMe) versus celecoxib for the treatment of osteoarthritis symptoms: a double-blind cross-over trial. BMC Musculoskeletal Disorders. 2004;5:6. — The trial showing SAM-e matched celecoxib for joint pain by the second month, with a slower onset. — doi:10.1186/1471-2474-5-6
- Anstee QM, Day CP. S-adenosylmethionine (SAMe) therapy in liver disease: a review of current evidence and clinical utility. Journal of Hepatology. 2012;57(5):1097–1109. — A clinical review of SAM-e in liver disease: plausible mechanism and some benefit, but robust randomized evidence still limited. — doi:10.1016/j.jhep.2012.04.041
- Guo T, Chang L, Xiao Y, Liu Q. S-adenosyl-L-methionine for the treatment of chronic liver disease: a systematic review and meta-analysis. PLOS ONE. 2015;10(3):e0122124. — A meta-analysis of 12 randomized trials (705 patients): differences in bilirubin and AST but not ALT; ursodeoxycholic acid and stronger neo-minophagen C more effective than SAM-e in certain liver diseases. — doi:10.1371/journal.pone.0122124
- Gurung V, Middleton P, Milan SJ, Hague W, Thornton JG. Interventions for treating cholestasis in pregnancy. Cochrane Database of Systematic Reviews. 2013;(6):CD000493. — The systematic review of treatments for intrahepatic cholestasis of pregnancy: ursodeoxycholic acid relieved itching better than SAM-e, SAM-e added to ursodeoxycholic acid did no better than ursodeoxycholic acid alone, and the evidence was insufficient to show that SAM-e is effective. — doi:10.1002/14651858.CD000493.pub2
- Iruela LM, Minguez L, Merino J, Monedero G. Toxic interaction of S-adenosylmethionine and clomipramine. The American Journal of Psychiatry. 1993;150(3):522. — A published case report (letter) of a toxic interaction between SAM-e and the antidepressant clomipramine. — PubMed PMID: 8434674